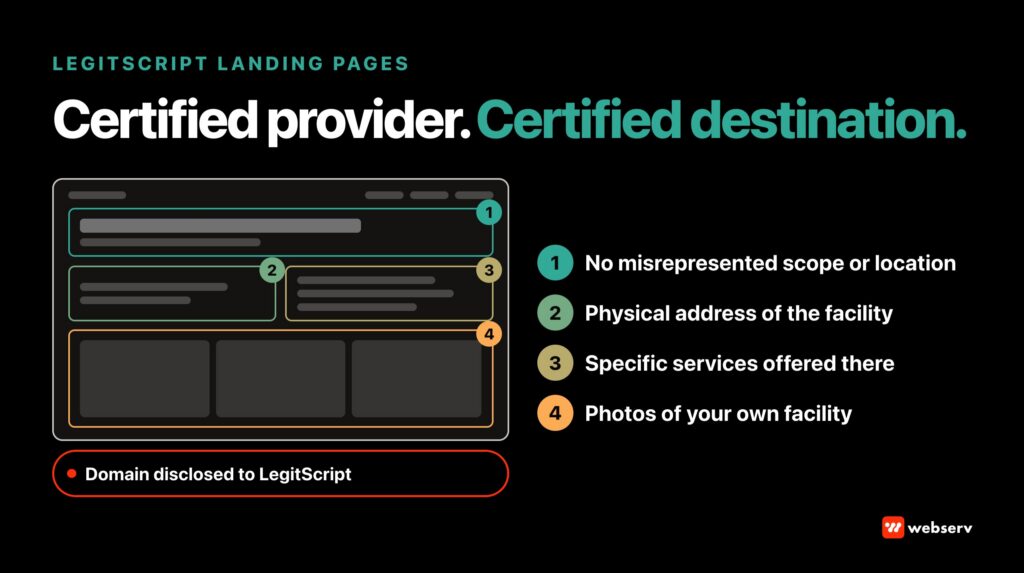
Paid social for behavioral health treatment centers has crossed a threshold in 2026. Meta restricted lower-funnel optimization for many health advertisers, the updated 42 CFR Part 2 rule reached its compliance date, and platform-level audience targeting has narrowed simultaneously. A 2022 paid social playbook applied to a 2026 account produces predictable failure.
The operators winning paid social in this category are running an integrated channel mix, a HIPAA-safe tracking stack, and a creative framework built around family-member voice and platform-specific compliance. Each of those layers connects to the others; an account missing any one of them does not reach scale.
This guide walks through the 2026 landscape, the six platforms in the mix, the family-versus-patient targeting decision, the HIPAA-safe tracking architecture, the common mistakes that get accounts banned, and how to evaluate or audit a paid social agency for behavioral health.
Key Takeaways
- Paid social is still a viable admissions channel for behavioral health, but only with LegitScript certification, Meta addiction treatment certification, and a HIPAA-aware tracking infrastructure built around the Conversions API instead of the Meta pixel.
- The 2026 platform restrictions are stricter than any prior cycle. Starting in January 2025, Meta restricted many health and wellness advertisers from optimizing on lower-funnel conversion events. The compliance date for the updated 42 CFR Part 2 rule was February 16, 2026.
- Family-first targeting outperforms patient-first targeting for residential and PHP admissions. The buyer is rarely the patient. The audience signal layer, household-income tiers, and life-event signals identify family decision-makers better than any zip-list approach.
- Creative compliance is non-negotiable. Before-and-after imagery, exaggerated outcome claims, and emotional manipulation language get accounts disabled in the current enforcement environment. The compliant creative bar is educational, family-focused, and outcome-realistic.
- Budget allocation should weight Meta heavily (60-75% of social spend for most BH operators), with TikTok and Snap as supplements for specific patient demographics, and Reddit and YouTube as long-tail authority surfaces rather than direct-response channels.
A 42-bed residential treatment center came to us in January after Meta disabled their ad account for the third time in 18 months. The first disable was a creative policy violation. The second was an unverified payment source.
The third was the lookalike audience they had built from their Meta pixel, which Meta’s compliance system flagged as PHI exposure under the new healthcare advertising restrictions that started rolling out in 2025.
The facility had spent six months and roughly $180,000 with three different agencies, none of which had explained why the disables kept happening, and all of which had assumed the next one would be the last.
The fix took 60 days. We removed the Meta pixel entirely, rebuilt tracking on the Conversions API with server-side identity matching, restructured creative around compliant family-first messaging, and submitted a new LegitScript-tied addiction treatment certification through Meta’s approval flow.
The account has been live and stable for the 11 months since, running $58,000 a month in social spend at a cost per admission roughly half of what the prior agencies had achieved before the disables started.
That story is the right opener for this guide because it captures the actual problem with paid social for behavioral health in 2026. The platforms are still high-volume admission channels for the operators who run them correctly. They are also a regulatory minefield that gets worse every quarter as Meta, TikTok, and the rest of the stack tighten their healthcare advertising posture.
This paid social guide covers what the 2026 environment actually looks like, what the compliant playbook is across each platform, and how to build the tracking and creative infrastructure that survives the next round of restrictions.
The 2026 paid social landscape for treatment centers
The starting point is that 2026 paid social for behavioral health is harder than it was in 2022, and the trend is toward more restriction, not less. Three structural forces are reshaping what works.
The first is platform compliance tightening. Starting in January 2025, Meta restricted many health and wellness advertisers from sharing and optimizing on lower-funnel conversion events such as purchases, pushing campaigns toward upper-funnel signals. TikTok and Snap have both narrowed addiction treatment ad eligibility, requiring educational framing rather than direct admission acquisition messaging.
The second is HIPAA enforcement intensification. OCR closed 21 HIPAA settlements and civil money penalties in 2025, its second-highest annual total, per HIPAA Journal’s enforcement tracking. The updated 42 CFR Part 2 rule reached its compliance date in February 2026, which means mishandling of substance use disorder records now carries civil money penalties aligned with HIPAA’s tiered structure. OCR’s online tracking guidance keeps tracking technologies on pages that collect PHI in scope.
The third is the broader privacy infrastructure shift. iOS 14.5 in 2021, browser tracking-prevention changes, and Apple’s continued attribution-window tightening have made the pre-2021 paid social tracking model unworkable. The operators still running on legacy pixel-only setups are getting worse data every quarter and do not realize it.
The combined effect is that paid social for behavioral health requires a higher operational bar than it used to. Treatment centers running paid social in 2026 need compliance infrastructure, a server-side tracking layer, a family-first creative strategy, and a budget posture that survives platform volatility. Operators who try to run the 2020 playbook in 2026 lose ad accounts, miss admissions, and pay agencies to learn what was already published in platform documentation.
HIPAA and platform compliance in 2026
Compliance is the spine of paid social in this category. Two compliance surfaces drive most of the operational reality.
HHS-OCR and HIPAA tracking technologies
The HHS-OCR guidance on online tracking technologies classifies the data flowing through pixels, SDKs, and analytics tools as PHI when the user is engaging with health-related content. A Meta pixel on a page about IOP services that fires on form submission is sending PHI to Meta unless a Business Associate Agreement is in place, which Meta does not sign. The legal exposure for treatment centers running standard pixel setups is real and increasing.
The implication is that the Meta pixel as historically deployed is a HIPAA risk on most treatment center sites.
The compliant replacement is the Meta Conversions API deployed with server-side identity hashing, no PHI in the URL path or event parameters, and an opt-in disclosure on the page that informs users about data collection. The headline is that the pixel-only approach common in 2020 will not survive a 2026 OCR audit.
The February 2026 Part 2 compliance date puts substance use disorder records under HIPAA-style enforcement, which means the SUD content category carries its own layer of exposure on top of general healthcare. Treatment centers should plan as if an audit is possible, and the tracking layer should be built accordingly.
Meta’s addiction treatment policy and LegitScript
The Meta addiction treatment ad policy requires advertisers running addiction treatment ads in the United States to be LegitScript-certified and to apply separately to Meta for permission to advertise in this category. The certification process is the gate for serving ads at all; the permission flow on top of it is what distinguishes addiction treatment from general healthcare advertising on the platform.
Treatment centers without active LegitScript certification cannot run compliant paid social on Meta. The certification process is also the prerequisite for Google Ads and the rest of the major ad ecosystem, so the work is not Meta-specific. The certification review timeline should be built into any paid social planning that does not already have the credential.
The practical effect of Meta’s health and wellness restrictions is reduced access to lower-funnel optimization events like Purchase and Lead, plus tighter audience targeting. The optimization workarounds discussed later in this guide, and in our Meta ads tactics for treatment centers, are how operators actually run effective campaigns despite the restrictions.
Other compliance surfaces
LegitScript and Meta are the two big ones. The remaining surfaces are platform-specific:
- Google Ads requires LegitScript and applies its own healthcare advertising policies and compliance mistakes framework, including healthcare advertising compliance constraints that apply across surfaces
- TikTok treats addiction treatment as a restricted category, with educational framing requirements and limited targeting
- Snapchat age-restricts addiction-related ads to users 18+ and requires educational rather than promotional messaging
- Reddit is the least restrictive but still requires honest claims and prohibits exploitative framing
- LinkedIn is generally usable for B2B treatment marketing (referral source acquisition, employee recruitment) without addiction-specific restrictions
The compliance posture across these surfaces is what determines which platforms a treatment center can run on, in what creative shape, and at what budget level.
Beyond platform policies, the FTC’s 2024 Health Products Compliance Guidance and its March 2026 enforcement letters to substance use disorder treatment providers add a federal regulatory layer to the picture. Unsubstantiated outcome claims like “guaranteed recovery” or “85% sobriety rate” without published methodology are actionable at the federal level regardless of which platform they ran on. The compliant default for treatment center paid social is defensible operator-voice claims with documented substantiation behind every quantitative statement.
Platform-by-platform breakdown
Paid social is not one channel. Each platform has its own audience, compliance posture, and economics. The right mix depends on facility, patient demographic, and budget scale.
 Infographic titled ‘Where treatment centers actually advertise in 2026 — and what wins on each platform’.
Meta (Facebook + Instagram)
Meta is still the dominant paid social channel for behavioral health admissions. It carries 60 to 75% of total social spend for most of the operators we work with, for three reasons.
First, the audience signal layer for family-decision-maker targeting is more developed than any other platform. Household income deciles, parental status, life events, and in-market signals combine to identify family members in a way TikTok or Snap cannot match.
Second, Meta’s creative formats (single image, carousel, Reels, Stories) cover the spectrum from educational long-form to fast direct-response. The same campaign can run a 60-second video about treatment options on Reels and a static image testimonial on the Facebook feed.
Third, despite the compliance restrictions, Meta still allows treatment center advertising with the right certification stack. TikTok and Snap operate at the margin of “can we even run here” for some operators. Meta operates at “what optimization events can we use” for the same operators.
The 2026 reality on Meta is that lower-funnel optimization (Purchase, Lead) is restricted for substance use treatment advertisers. The workaround is to optimize on upper-funnel events (ViewContent, Page View, custom engagement events) and use the Meta Conversions API setup to feed Meta the conversion signal it cannot capture through pixel. This setup recovers most of the optimization quality the restrictions removed, but only for operators who invested in the tracking infrastructure.
TikTok
TikTok runs cautious for addiction treatment ads. The platform’s stated approach is educational mental health awareness rather than direct treatment-acquisition advertising. In practice, treatment centers can run on TikTok with creative framed around mental health support, family resources, and educational content, with calls-to-action that route to information pages rather than direct admission flows.
The audience case for TikTok is specific. The platform’s user base skews 16-34, with the 18-24 demographic over-represented. For treatment centers focused on young adult patients (ages 18-29 specifically), TikTok produces admission inquiries from a demographic Meta reaches less efficiently. For centers focused on older patient populations or where the buyer is the parent of an adult child, TikTok is a less effective channel.
Budget allocation for TikTok in BH typically lands at 5 to 15% of total social spend when it makes sense, scaling up only for centers with strong young-adult patient fit.
Snapchat
Snapchat skews young like TikTok but with more aggressive ad restrictions. Addiction treatment ads must be educational, age-gated to 18+, and avoid emotional manipulation framing. The conversion economics on Snap are usually weaker than Meta or TikTok for BH because the user behavior on the platform is fast, light, and not conducive to multi-step admission flows.
Snap fits best as a brand-awareness layer for treatment centers reaching the young adult demographic, with the heavier conversion work happening elsewhere in the funnel. Allocation is typically 0 to 5% of total social spend for most BH operators. The same body-brokering competitive dynamics that distort Meta ad auctions also distort Snap and TikTok auctions in known fraud corridors, which factors into geo allocation.
Reddit is increasingly viable in 2026 for treatment center advertising. The platform’s policy posture is more permissive than Meta or TikTok, and Reddit’s audience includes high-intent communities (r/addiction, r/recovery, r/AlAnon) where treatment-related content has real engagement.
The challenge with Reddit is that the platform’s culture punishes obvious promotional content. Treatment center ads that read as direct-response acquisition fail. Ads that read as informational, with genuine resource value, perform. Reddit also has limited audience signal sophistication relative to Meta, which means the targeting is coarser and the budget efficiency is lower at scale.
Reddit fits best for treatment centers with strong educational content libraries and a willingness to invest in community engagement alongside paid placement. Allocation is typically 3 to 10% of total social spend.
YouTube
YouTube is technically Google’s display network, not paid social, but it functions as a paid social surface for behavioral health. The pre-roll, mid-roll, and in-feed video formats reach a family-decision-maker audience well, especially for residential and high-acuity treatment.
The compliance posture follows Google Ads (LegitScript-gated). The creative requirement is video, which is a higher production bar than static or short-form. For treatment centers with a video creative budget, YouTube is a strong family-targeting channel with stable cost-per-admission economics. The ad group structure principles that govern Google Search campaigns also apply to YouTube video targeting. For centers without video creative capacity, YouTube is premature.
Budget allocation is typically 5 to 15% of total social spend when video creative is available.
LinkedIn is the outlier in the BH paid social stack. The platform is not effective for direct patient acquisition, but it is highly effective for B2B treatment marketing: referral source acquisition (interventionists, therapists, employee assistance programs), employer-EAP partnership development, and clinical recruitment.
For treatment centers with a referral-source or B2B partnership growth objective, LinkedIn carries unique value. For centers focused on direct family acquisition, LinkedIn is a distraction. Allocation depends entirely on the operator’s growth strategy rather than the patient demographic.
Audience strategy: family vs patient targeting
The single most important strategic decision in BH paid social is whether the campaign is targeting the patient or the family member. The economics, creative, and platform fit all change with the answer.
 Infographic titled ‘Family vs patient targeting: when each wins.’
For residential treatment, PHP, and high-acuity outpatient programs, the family member is the buyer 70 to 85% of the time. The patient is in crisis or actively using and is not the decision-maker for admission. The family member is the parent, spouse, or adult child who is researching options, comparing facilities, and writing the check.
Family-first targeting on Meta uses:
- Household income tier signals (top 20 to 30% for OON economics)
- Life event signals (recently divorced, new homeowner, recently moved correlate with elevated decision-bandwidth)
- Parental status (parents of adult children for adult treatment programs)
- In-market for healthcare signals
- Interest layers (mental health, addiction recovery, family support, AA/NA, Al-Anon) layered with healthcare demographic targeting signals
- Geographic targeting that follows the exclude-zip framework rather than narrow zip inclusion
For outpatient programs, MAT, and lower-acuity care, the patient is more often the direct decision-maker. The patient-first creative speaks to the patient’s own readiness and reduces stigma. The audience targeting shifts to the patient’s own demographic and interests rather than the family member’s.
A mixed-acuity facility (offering residential plus outpatient) typically runs two parallel campaign structures: one family-first for the residential pull, one patient-first for the outpatient pull. The bidding, budget, and creative diverge between the two campaigns because the buyer pattern diverges.
The single most common audience mistake in this category is assuming the patient is the buyer for residential. They are not. Building creative and targeting around the patient when the family is the actual decision-maker is the fastest way to spend $50,000 a month with disappointing admission volume.
Mitch Marowitz, Director of Paid Media, Webserv
The three compliance layers
Meta Ads in behavioral health sits inside three overlapping compliance layers that determine what runs and what does not.
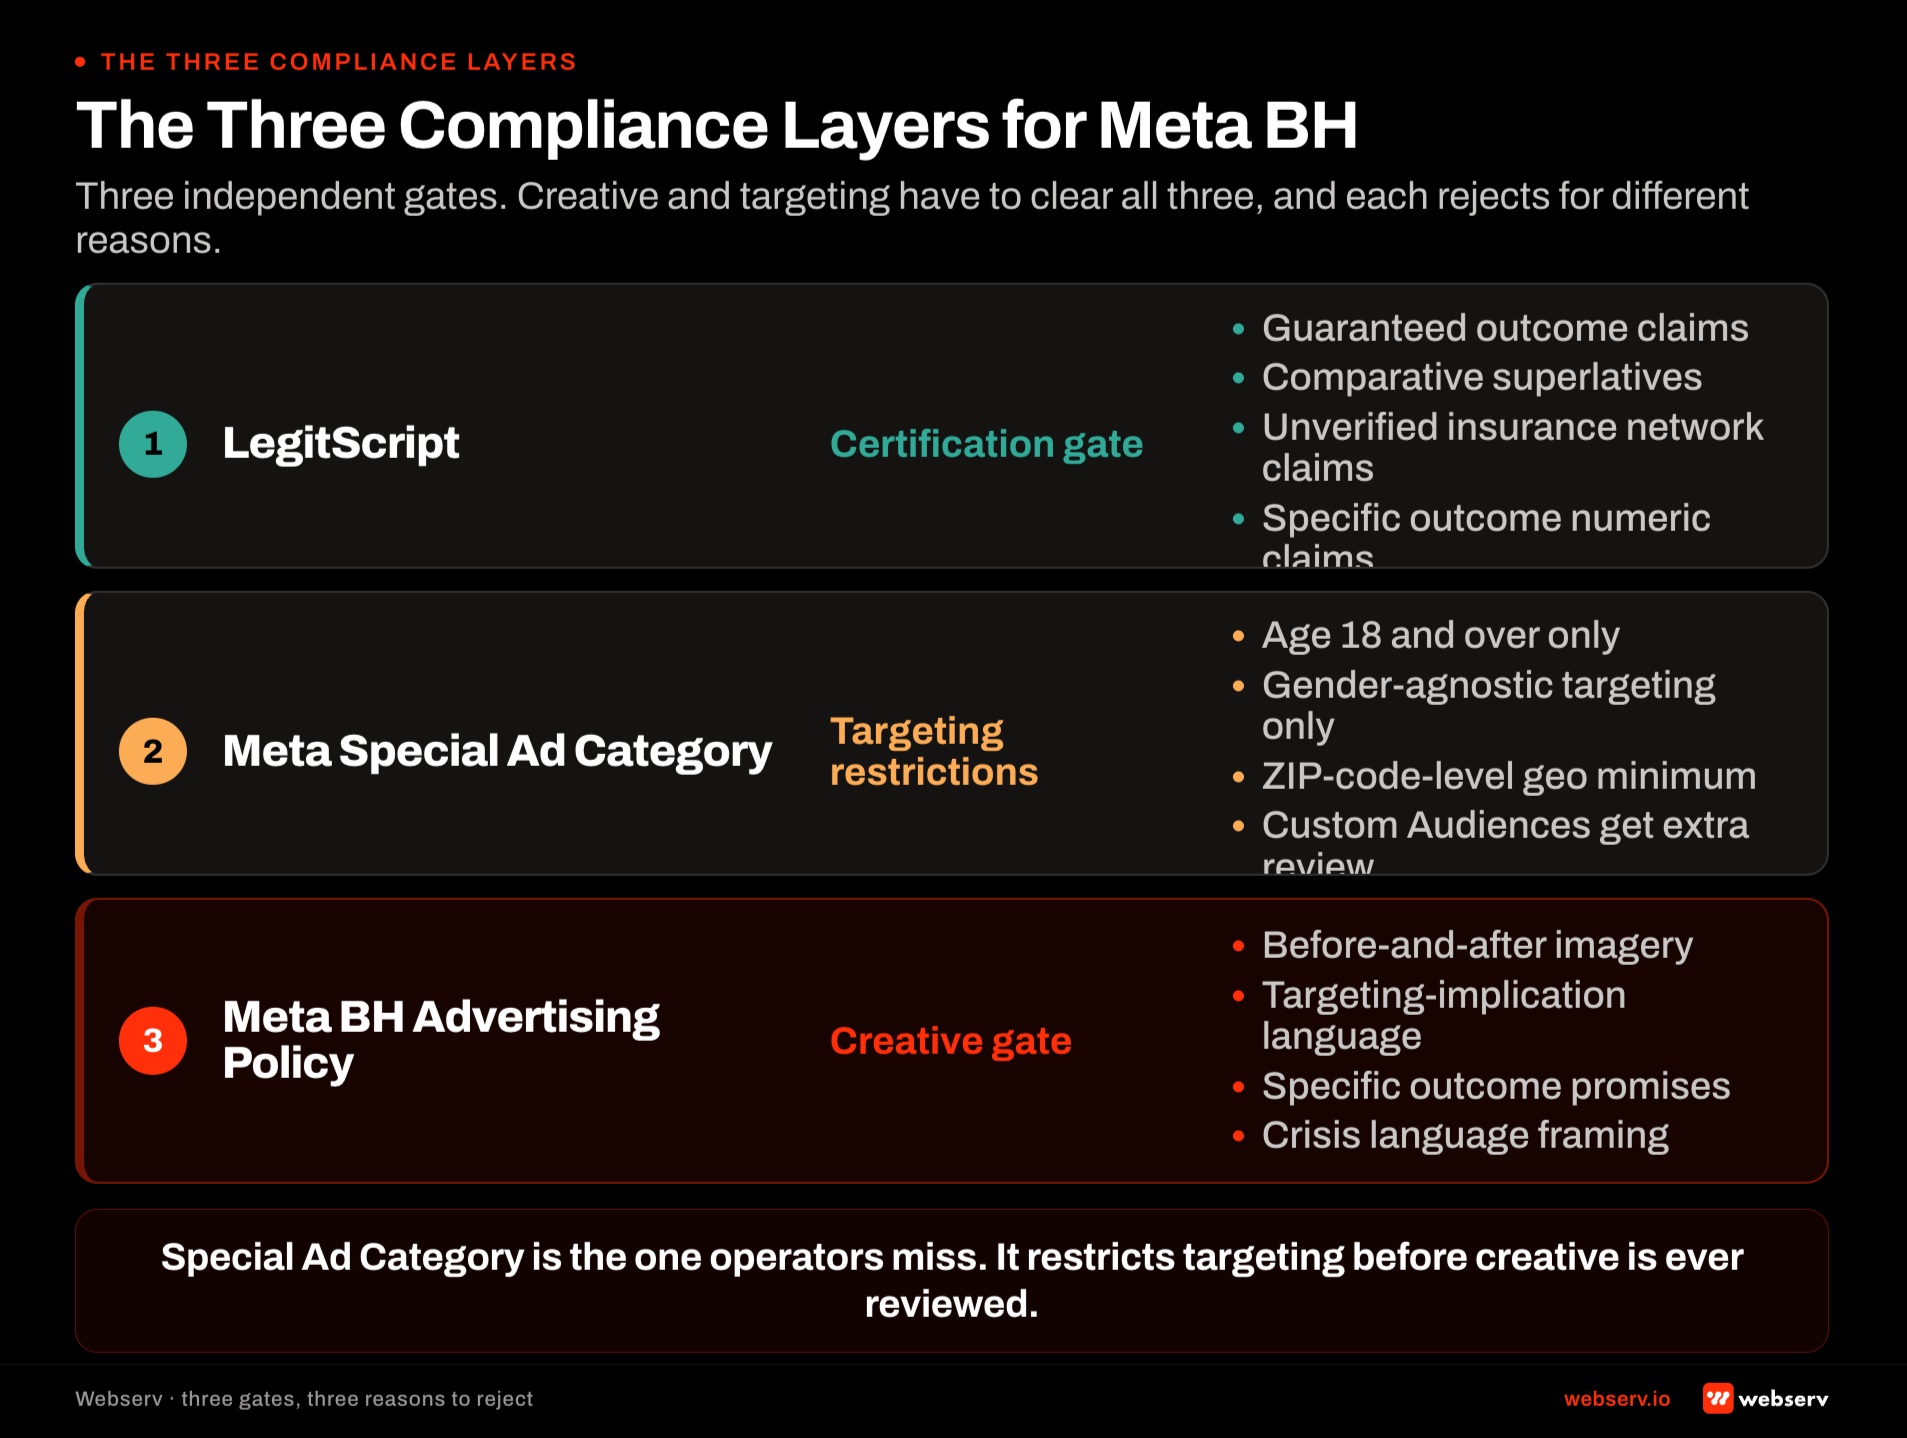
Layer 1: LegitScript certification. Meta requires addiction treatment advertisers targeting the United States to be certified by LegitScript and to apply to Meta for written permission to advertise. LegitScript certifies the provider and its websites, and certification has to stay current for that permission to hold. If certification lapses, BH ads stop being eligible until it is restored.
The claim patterns that put certification and ad approval at risk: guaranteed outcome claims, comparative superlatives without documentation, unverified insurance-network claims, and specific-outcome numeric claims without clinical documentation.
Layer 2: Meta’s restrictions on health data. Meta prohibits sharing health information through its Business Tools, including URL parameters, custom events, custom conversions, and Custom Audiences, and the names of events, conversions, and audiences cannot imply it. Meta’s systems also detect and restrict data from sites it classifies as health-related, which limits lower-funnel optimization for many BH advertisers. Custom Audiences and Lookalikes built from patient, admit, or inquiry lists are off the table.
Plan the account around broad targeting and upper- and mid-funnel optimization signals. Facilities that build around these limits from the start avoid rebuilding campaigns after Meta restricts their data.
Layer 3: Meta advertising policy for BH-related content. The general Meta ad policy that applies to sensitive categories. Restricts before-and-after imagery, targeting-implication language, specific-outcome promises, and crisis-language framing. Applies to every ad regardless of targeting.
The specific fix pattern for all three layers: creative and landing pages designed with the three compliance layers in mind from the start, rather than as post-hoc compliance review after creative is produced.
How Profound Treatment drove 31 admits and a 42% drop in cost per viable in one quarter
Broad match pivot, negative keyword management, and intake-level conversion tracking turned a fragmented paid strategy into a predictable admissions engine.
Read the case study →68 viable VOBs at $4,529 cost per viable
Targeting restrictions for BH advertisers
BH advertisers on Meta work with fewer targeting levers than most categories, and the limits come from Meta’s data rules, not from a special ad category.
Target adults. Treatment decisions are made by adults, so target people 18 and older even when the program serves adolescents. Adolescent programs reach parents through broad adult targeting and creative written for parents.
Condition interests are gone. Meta removed detailed targeting options tied to health causes in January 2022, so you cannot target people by condition or treatment interest. Gender-specific programs (women’s residential, men’s outpatient) can still use Meta’s standard age, gender, and location controls.
Let creative do the qualifying: program-specific messaging sorts the audience better than any interest filter.
Geography is the sharpest lever. Standard location targeting is available, so match it to the facility’s real service area and admissions footprint.
For most facility programs, a metro or regional footprint works because families travel for treatment. Facilities with a tight local service radius benefit less from Meta than facilities with a broader service area.
Custom Audiences and Lookalike Audiences. Do not build them from patient, admit, or inquiry lists. A list of people who contacted or entered a treatment center is health information under Meta’s terms and, for SUD programs, creates HIPAA and 42 CFR Part 2 exposure. Website-visitor audiences are only safer if the pixel sends no health-revealing page or event data, so review them with counsel before use.
The Meta Ads BH program at a glance
3
Compliance layers: LegitScript + Meta permission, health-data rules, ad standards
3-5
Campaigns per facility organized by intent tier, not audience variant
Fund to learn
Budget high enough to exit the learning phase, not a fixed number
Cohort view
Measure cost-per-admit on inquiry cohorts, not sessions
Audience strategy (tactics 4 through 7)
Retargeting does not exist for SUD on Meta. The audience play is broad prospecting with structural filters layered on. The four tactics below are how that works.
Tactic 4. Default to broad prospecting, not interest-stacked audiences
Meta’s Health and Wellness ads policy kills retargeting and limits custom audience-based health targeting. The audience play is broader than most operators expect.
Run broad geo and demographic audiences with strong creative and let Meta’s algorithm do the audience finding. Interest stacks (“substance abuse” + “recovery” + “rehabilitation”) look targeted in the campaign builder and underperform in practice because the algorithm reaches the same converters faster without the constraints.
Tactic 5. Layer income-tier targeting via custom audiences
For out-of-network programs, the audience that converts is the audience with PPO coverage. PPO coverage usually comes through employer plans, so employment and income signals are a reasonable proxy for it.
Meta does not expose income brackets directly, but the same effect can be approximated through ZIP-code custom audiences derived from census data, lookalike audiences seeded on past private-policy converters, and education-level proxies. The income filter does not need to be a Meta input. It needs to be a layered effect.
Tactic 6. Target family members, not patients
The person searching for treatment is usually not the patient. It is the spouse, the parent, the adult child. A family member often makes the first call.
Build audiences broad enough to include the family members who are often researching care, using age and geography rather than health-related interests. The creative has to work for them without implying anything about their household, which Meta’s personal attributes policy prohibits.
Tactic 7. Seed lookalikes from your offline VOB list
Standard lookalikes built from form-fill seed lists carry the same quality issues as form-fill optimization: the algorithm finds more people who look like cheap leads.
The better seed is your verified-VOB list from the CRM. The lookalike built on that seed converges faster on the audience that actually produces admits, because Meta’s algorithm is matching against the policy-verified outcome rather than the form-fill event.
Creative strategy
Creative in BH paid social has to do two things at once. It has to emotionally resonate with the family member’s actual experience (which is grief, fear, exhaustion, and hope). And it has to clear platform compliance, which prohibits emotional manipulation, before-and-after imagery, and outcome claims that cannot be substantiated.
The compliant creative bar has five elements that work.
Family-perspective framing. The hero in the ad is the family member, not the patient. The voiceover or copy speaks from the family member’s perspective. The emotional resonance is the family member’s relief at finding the right program, not the patient’s transformation. This framing is compliance-safe because it does not make claims about treatment outcomes for the patient.
Educational, not promotional. The creative explains something the family member needs to understand (the difference between levels of care, what to look for in a residential program, how insurance verification works) rather than directly pitching the facility. Educational creative passes platform review faster, scales further, and converts better in 2026 than direct-pitch creative does.
Family member featured as a presenter, not as a “success story.” Showing a real family member explaining how they navigated a relative’s treatment is highly effective. Showing a “before” picture of a person in active addiction and an “after” of them sober is a creative policy violation on Meta, TikTok, and most other platforms.
Honest framing of treatment realism. Saying “we help families work through the next 90 days” is compliant. Saying “we save lives every day” is not. The closer the language is to the operational reality of what the facility actually does, the safer the creative is to scale.
Native format respect. Reels and TikTok creative should look native to the platform (vertical, 9:16, fast-cut, captioned). Facebook feed creative can be longer-form. LinkedIn creative reads more formal. Reusing the same asset across all formats is a common failure pattern that hurts performance on every platform it runs on.
The compliant ad headlines work we publish on the Google Ads side translates directly to Meta and TikTok creative copy. The principles are the same: no outcome promises, no before-and-after framing, no emotional manipulation, no first-person “I’m a patient” testimonials without consent infrastructure. Within those constraints there is still meaningful creative range.
Creative framework for Meta
The creative templates that work in Meta for BH: the five static ad templates covered in our static ad creative templates guide (clinical authority, family testimonial, condition-specific, verification-focused, geographic), plus video creative that adapts the same template patterns to the specific reels and stories placement contexts.
Static creative for Meta feed. 1080 by 1080 square and 1080 by 1350 vertical. Both formats needed because Meta increasingly favors vertical in feed placement.
Static creative for Meta stories. 1080 by 1920 vertical with the safe zone for platform UI overlays. Static stories underperform video stories but remain useful for tested creative not yet produced as video.
Video creative for Meta reels. 1080 by 1920 vertical, 15 to 30 seconds typical length, hook in the first 3 seconds. BH video creative that works: clinician-narrated program explanations, family testimonial voiceovers, facility walkthroughs with clinical narration.
Video creative for Meta feed. 1080 by 1080 square or 1080 by 1350 vertical, 15 to 60 seconds. Similar content patterns as reels but with the specific engagement patterns feed viewers show (longer initial view time, more consideration).
The specific creative production cadence: 3 to 5 new static units and 1 to 2 new video units per month per facility. Winners scale into new audiences. Fatigued units get retired when their frequency and cost-per-result trend the wrong way.
DO
- Organize the account as 3-5 campaigns by intent tier (acute need, research phase, brand awareness + retargeting) so Meta’s optimization has enough signal to train.
- Route conversions through the Conversions API via a BAA-covered intermediary that strips PHI before anything reaches Meta.
- Send admits as neutral value-tier events through the server-side layer, and reconcile Meta’s counts against CRM admits every month. Never upload admission lists as audiences.
- Renew LegitScript well before certification expires, because a lapse can disable the ad account until remediation clears.
- Report cost-per-admit at cohort level; treat session-level cost-per-inquiry as a diagnostic signal only.
DON’T
- Ship before-and-after imagery or targeting-implication copy , automatic Meta rejection under BH policy every time.
- Sprawl the account into 20+ campaigns by audience or creative variant , fragments the conversion signal beyond what Meta can optimize against.
- Judge Meta in the first couple of weeks, before the inquiry-to-admit signal has arrived and while the read is still misleading.
- Send PHI to Meta through any channel: no condition or level-of-care details, no descriptive event names, no browser-side identifiers, and no admission lists as audiences.
- Rely on Meta as the sole paid channel, because health-data restrictions or a LegitScript lapse can cut delivery quickly.
Creative volume (tactics 11 through 13)
Meta’s 2026 algorithm needs more creative than most operators understand. The three tactics below are the volume discipline. The full creative-investment thesis is in our guide to under-investment in rehab Facebook creative.
Tactic 11. Run 20 to 30 active creative variants minimum
Meta doesn’t publish a minimum, but its creative diversification guidance is clear that Advantage+ needs genuinely different ads to choose from. Our working target for most BH operators is 20 to 30 active variants at any given time. Below that, the account is starved.
The variants do not need to be 30 separate productions. Ten distinct concepts each in two to three format variants (vertical video, static, carousel) gets you to 20-30 active assets without exhausting your creative budget.
Tactic 12. Refresh winning concepts every 2 to 4 weeks
Even winning creative fatigues. Operators who let a winning ad run six months are paying creative-fatigue premiums on every impression past week four.
Track frequency by creative. When frequency exceeds 4.0 on a single audience and CPL begins rising in sync, the creative is fatigued. The right response is replacement, not a frequency cap.
Tactic 13. Ship 5 to 10 new variants per week
The continuous pipeline is what separates top-quartile rehab Meta accounts from the rest. Operators who treat creative as a quarterly deliverable are running a 2019 playbook. Operators who ship five to ten new variants weekly are feeding Meta’s algorithm at the cadence it now requires.
The variants do not need to be brand-new productions. Hook swaps, open-shot changes, caption-hierarchy variations, and speaker rotations on talking-head assets all count.
How Profound Treatment drove 31 admits and a 42% drop in cost per viable in one quarter
Broad match pivot, negative keyword management, and intake-level conversion tracking turned a fragmented paid strategy into a predictable admissions engine.
Read the case study →68 viable VOBs at $4,529 cost per viable
Creative direction (tactics 14 through 16)
What the creative actually says matters as much as how much of it you produce. The three direction tactics below have outperformed in our portfolio across budget tiers and program types.
Tactic 14. Lead with the facility, not the viewer’s condition
Meta’s personal attributes policy bars ads that assert or imply the viewer’s condition, or a family member’s. “Are you struggling with addiction?” fails that test. The full headline-language pattern is in our compliant ad headlines guide.
So does the family-member version (“When your son tells you he needs help”). Lead with the facility, the admissions process, or the clinical team instead, which works for patients and families alike.
Tactic 15. Put real clinical leadership on camera
A 30-second vertical talking-head explainer from your named medical director outperforms stock-photo creative consistently. The named credential (Dr., LMFT, PhD), the real face, and the spoken delivery create trust signals Meta’s algorithm and the family-member viewer both reward.
Treatment centers with credentialed clinical leadership willing to appear on camera have a creative advantage other centers cannot replicate. The cost to produce the asset is one afternoon and one editor.
Tactic 16. Use real facility tours, not stock imagery
A 45-second phone-shot vertical tour of your actual facility, with the admissions counselor walking through real rooms, beats studio-grade stock imagery on conversion rate. The authenticity cues (real beds, real kitchen, real outdoor space, real staff) build trust at conversion.
The “diverse hand-holding circle on a beach” stock shot is dead. Every operator is running the same stock library. Real footage of your real facility is a differentiator that compounds over the life of the campaign.
Tracking infrastructure that survives 2026
The tracking layer is what separates BH operators who actually optimize from operators who pretend to optimize. Three pieces matter.
 Infographic titled ‘The HIPAA-safe tracking stack — what 2026 actually requires’.
Server-side conversion API
The Meta Conversions API replaces the browser-side pixel for sending conversion events to Meta. The server-side path has three advantages in 2026: it does not require PHI to flow through the browser, it survives iOS attribution restrictions, and it gives Meta cleaner signal for the optimization layer.
The Conversions API setup for treatment centers covers the implementation in detail. The headline is that without the CAPI infrastructure, paid social in 2026 is running with one hand tied behind its back, and the operators who skipped this work are the operators with disabled ad accounts.
First-party data layer
Treatment centers have rich first-party data: form submissions, phone calls, intake records. Connecting that data to the paid social signal layer (through hashed email and phone matching) recovers most of the conversion attribution that platform restrictions removed.
The pattern is that the intake CRM captures the lead, hashes the contact identifiers, and forwards them to Meta and the other platforms through the CAPI or equivalent. Meta uses the hashed match to attribute the conversion back to the original ad click. The user identity stays on your side. Meta gets the optimization signal it needs without receiving PHI.
This is the same pattern that runs the HIPAA-compliant Facebook ads setup for treatment centers. It is more work than a pixel install, and it is the bar that 2026 compliance and 2026 attribution both require.
Call tracking integrated with the social platforms
Roughly 60 to 75% of behavioral health admission inquiries come in by phone, not by form. A paid social setup that only tracks form fills is missing most of the conversion signal.
The fix is a call tracking platform (CallRail, CallTrackingMetrics, or similar) that assigns dynamic numbers per ad source, captures the call as a conversion event, and feeds the event back to Meta and the other platforms through the same CAPI pipeline.
The conversion tracking work for admission attribution is identical on the paid social side. The single integrated pipeline (CRM + call tracking + CAPI) is what gives Meta and Google enough signal to optimize despite the platform restrictions on healthcare conversion events.
How Profound Treatment drove 31 admits and a 42% drop in cost per viable in one quarter
Broad match pivot, negative keyword management, and intake-level conversion tracking turned a fragmented paid strategy into a predictable admissions engine.
Read the case study →68 viable VOBs at $4,529 cost per viable
Measurement setup that resolves Meta optimization
Meta’s optimization is largely black-box. The specific measurement setup that resolves Meta’s decisions into attribution decisions marketing leadership can act on: neutral value-tier Conversions API events, CRM-reconciled admit attribution, and cohort-based cost-per-admit measurement.

Meta CAPI for server-side conversion tracking. Meta Conversions API sends conversion events server-side rather than browser-side. Resolves iOS Safari cookie limitations and ad-blocker blocking, but server-side delivery alone does not make PHI safe to send.
The compliant implementation routes events through a BAA-covered server-side layer that strips PHI before anything reaches Meta. Our HIPAA-safe conversion tracking stack covers the value-tier architecture, and our HIPAA-compliant Conversions API guide walks through the Meta setup. Events sanitized to remove PHI before forwarding to Meta. Match quality comes from click and browser IDs, event IDs, and, for value-tier events only, hashed email or phone sent through the BAA-covered layer. Send identifiers only with documented consent and counsel sign-off, and never alongside condition or level-of-care data.
The CRM stays the source of truth for admits. Admits reach Meta as individual Tier 1 events from the server-side layer, not as uploaded lists of patients. Keep the event name neutral (tier_1_conversion) and attach no condition, level of care, or admit date.
The workflow: preserve the click ID and campaign source on the inquiry record in your CRM so the server-side event can be matched. Reconcile Meta-reported conversions against CRM admits by campaign every month. Use the reconciled numbers to move budget between campaigns, and let Meta optimize toward the value tiers.
Cohort-based cost-per-admit measurement. Cost-per-inquiry is the session-level metric Meta reports. Cost-per-admit is the metric that matters for marketing decisions.
The measurement pattern: track inquiries in one cohort, follow the cohort through admit conversion, and calculate cost-per-admit from ad spend divided by cohort admits. Facilities that measure cost-per-inquiry alone typically make suboptimal Meta decisions because inquiries and admits do not correlate directly.
Most in-house teams hit a wall not because they lack knowledge, but because they lack bandwidth.
When you are ready to hand it off, Webserv has spent 9 years executing exactly this for treatment centers nationwide.
Budget allocation framework
The right paid social budget depends on facility size, payer mix, geographic scope, and growth objective. The shape of the allocation is more consistent across operators than the dollar amount.
Total social spend as percent of total marketing. Most BH operators land between 25 and 40% of total marketing budget on paid social, with the rest split across paid search, organic, and referral source development. Operators below 25% are usually under-investing in family acquisition. Operators above 40% are usually over-rotated and missing the search and SEO layer.
Platform mix within social. Meta carries 60 to 75%. YouTube and TikTok combined carry 15 to 25%. Snap, Reddit, LinkedIn carry the remainder. Operators who try to spread evenly across all platforms tend to underperform operators who concentrate on Meta with selective supplementation.
Family vs patient split. For mixed-acuity facilities (residential + outpatient), family-first campaigns typically carry 65 to 75% of social spend with patient-first campaigns at 25 to 35%. The exact split should follow the admission mix the facility actually wants.
Testing budget vs scale budget. A healthy account runs 10 to 20% of monthly spend on creative testing (new audiences, new ad copy, new formats) and the rest on the proven combinations. Operators who run 0% testing budget plateau within 6 months. Operators who run 40% testing budget never reach scale efficiency.
Reserve for compliance disruption. The 2026 environment is volatile. Ad accounts get disabled. Audiences get suspended. Optimization events get restricted. A budget allocation that has no flexibility for compliance disruption breaks during the first incident. Most operators should plan to redeploy 10 to 20% of social spend within 30 days if a platform restriction forces a campaign rebuild.
Concentrate on Meta. Skip the multi-platform pitch.
The single biggest small-budget mistake is spreading $14,000 across Meta, TikTok, Snap, Reddit, and LinkedIn because the agency pitched a “diversified channel mix.” For BH operators under $20,000 a month, Meta should carry 80 to 100 percent of social spend. The other platforms become viable as the budget grows past $25,000.
The reasoning is that Meta’s audience signal layer is more developed than any other social platform for the family-member buyer who drives BH admissions. Household income deciles, parental status, life events, and in-market for healthcare combine in a way TikTok and Snap cannot match.
At small budgets, concentrating on Meta gives the algorithm enough conversion volume to optimize at all. Diluted budgets across five platforms give no platform enough to learn from. The Paid Social Ultimate Guide covers the platform decision in more depth.
The exception is treatment centers focused on patients ages 18 to 29, where TikTok and Snap can carry 10 to 20 percent of spend even at smaller budgets. For adult-population facilities, Meta-only is the right starting point.
Lead with Reels at 35 to 50 percent of spend
Reels typically run at a lower CPC than feed placements, and the algorithm rewards Reels with cheaper distribution. For small budgets, this is the single most consequential format allocation decision.
The pattern in our accounts is that Reels carry 35 to 50 percent of Meta spend for BH operators under $20,000 monthly, with the rest split across carousel (20-25%), single-image feed (15-25%), and Stories (10-15%).
The compliant Reels creative pattern for BH is family-perspective: the family member is the narrator, the story is brief and emotionally honest, and the bridge to action is soft. The Meta ad formats framework covers the exact three-frame pattern that works. The fast version is: family-member hook in 0-3 seconds, the story in 3-20 seconds, brand bridge in 20-30 seconds.
Retire Instant Forms (lead forms)
Meta’s healthcare sensitive category in 2026 restricts what the algorithm can optimize on lead-form campaigns for substance use treatment. The forms still capture submissions, but the submissions tend to be low-intent users who tap through reflexively from a passive scroll.
The “form-fills look fine on the dashboard, none of them convert to admissions” pattern is almost always a lead-form problem.
The compliant alternative is click-to-site driving to a real conversion page. The friction of clicking through is a feature, not a bug, because it self-qualifies the user before they reach the call-to-action. Most operators who retire Instant Forms see admission rate per click double within 60 days, even on the same creative and budget.
Run exclude-zip geo, not include-zip
The default agency move is to pick “wealthy zip codes near the facility” and target only those. For residential treatment, this is backward. The family-member buyer is statistically distributed across thousands of zips, not clustered in the obvious wealth markets.
The exclude-zip framework inverts the default: run national or state-wide geography with thoughtful exclusions (low-historical-conversion zips, documented brokering corridors, low-income census tracts).
At small budgets, exclude-zip matters more than at large budgets because every wasted impression compounds against the limited spend. Operators who flip from include-zip to exclude-zip frameworks typically see admission cost drop 30 to 50 percent inside the first 60 days. The remaining 95 percent of US zips that the inclusion list was excluding produce the bulk of the actual admissions.
Build a small batched creative library, not monthly one-offs
The economics of paid social creative at small budgets break if every Reel is treated as a one-off production.
The right model is a single batched 2-day shoot with a family member willing to participate, producing 12 to 18 Reels variants plus 6 to 10 single-image stills plus 4 to 6 carousel concepts. The total production cost lands at $4,000 to $8,000 for the batch, and the variants supply the account for 4 to 6 months.
The monthly one-off model produces 1 to 2 Reels per month at $3,000 to $5,000 each. The math does not work at sub-$20,000 budgets. The batched model produces enough variant volume to keep the Meta algorithm fed and to prevent creative fatigue while keeping production cost manageable.
Deploy server-side Conversions API from day one
The Meta pixel as a primary tracking layer is a HIPAA exposure under HHS-OCR’s 2026 guidance on online tracking technologies, and a degraded signal source under Meta’s healthcare advertising restrictions. The Conversions API setup is the right replacement, with server-side identity hashing and no PHI flowing to Meta through URLs or event parameters.
For small budgets, deploying CAPI on day one matters more than at large budgets because the learning curve cannot afford to start with a degraded signal source.
Operators who wait to add CAPI until “after the campaign proves out” usually never get there because the campaign cannot prove out without the tracking infrastructure that makes optimization work.
 Infographic titled ‘The 4 highest-impact moves for sub-$20K paid social budgets’.
Integrate call tracking into the CAPI feed
Roughly 60 to 75 percent of BH admission inquiries come in by phone, not by form. A paid social setup that only tracks form fills is missing most of the conversion signal.
The fix is a call tracking platform (CallRail, CallTrackingMetrics, or equivalent) integrated into the conversion tracking pipeline that feeds CAPI.
At small budgets, this integration is the difference between Meta seeing 6 conversions a month (form fills only) and 24 conversions a month (form fills plus calls). The 4x signal volume changes what the algorithm can optimize toward, which compounds across the rest of the account. Without the call tracking integration, small budgets are stuck below the conversion threshold that Smart Bidding needs to optimize at all.
Optimize on upper-funnel events, not Purchase or Lead
Meta’s healthcare sensitive category in 2026 restricts lower-funnel optimization events for substance use treatment. Purchase and Lead are blocked or limited.
The workaround is to optimize the campaign on upper-funnel events (ViewContent, Page View, custom engagement events) and feed the actual conversion signal back through CAPI for the algorithm’s longer-term learning.
For small budgets, this restriction is more painful than for large budgets because the upper-funnel optimization produces noisier signal that needs more conversion volume to settle. The mitigation is the call tracking + CAPI integration from strategy 7, which gives the algorithm a richer downstream signal even when the direct optimization event is upper-funnel.
Target family-member audience signals, not patient signals
For residential treatment, the buyer is the family member 70 to 85 percent of the time. The audience signals that find family members are different from the signals that find patients. The right stack for family-buyer targeting on Meta:
- Household income tiers (top 20 to 30 percent for out-of-network economics)
- Life event signals (recently moved, new homeowner, recently divorced)
- Parental status (parents of adult children for adult treatment programs)
- In-market for healthcare signals
- Interest layers (mental health, family support, Al-Anon, addiction recovery)
The healthcare demographic targeting work covers the audience signal layer in more depth. For small budgets, getting this targeting right on day one is more consequential than at large budgets because there is no learning budget to waste on patient-targeting that produces low-converting clicks for residential programs.
Disable Advantage+ Creative on brand-sensitive elements
Meta’s Advantage+ Creative enhancements can be switched on by default when you build new campaigns, so check every toggle. For BH, several of those enhancements break compliance or brand integrity:
- Disable the music enhancement on creative featuring real family members
- Disable the text variation enhancement on creative carrying clinical or insurance claims
- Disable the image cropping enhancement on family-narrator creative where composition matters
Enable only brand-safe enhancements (aspect ratio variations, light retouching, brightness). The manual configuration takes 30 to 60 minutes per campaign and prevents the kind of auto-assembled creative violations that get accounts disabled.
For small budgets, an account disable is a 14 to 30 day recovery during which spend is paused. That outage on a $14,000 monthly budget represents lost momentum that cannot be recovered. The 30 minutes of Advantage+ configuration discipline is the cheapest insurance available, and it sits alongside the broader compliance mistakes that get rehab ad accounts banned as the structural defenses small budgets cannot afford to skip.
Build lookalikes from non-PHI seed audiences
Meta lookalike audiences built from a custom audience of past patients are a HIPAA violation because the seed audience contains protected health information. The compliant lookalike is built from non-PHI seed audiences:
- Newsletter subscribers who opted in for marketing
- Website visitors who consented to tracking on non-PHI pages
- Engagement audiences (people who watched 50 percent or more of brand video, engaged with Reels)
- Email subscribers from the general marketing list (not the patient CRM)
The seed audience is smaller than the patient list would be, which is why most agencies skip this step. For small budgets, the compliance-safe lookalike is the right move because an account disable is worse than a smaller seed audience. The HIPAA-compliant Facebook ads framework covers the consent infrastructure.
Refresh creative every 45 to 60 days
Creative fatigue is invisible to most operators because it compounds slowly across CTR and CPM rather than showing up as a sudden drop.
The right refresh cadence at small budgets is 45 to 60 days for Reels and Stories, 75 to 90 days for carousels, 60 to 120 days for single-image feed.
The refresh signal to watch for is frequency cap above 4 plus a declining CTR trend over 7 to 14 days. When both signals appear together, the creative is fatigued and needs to rotate out.
Operators who let creative run 6 to 12 months (the most common pattern I see) are paying a fatigue penalty without realizing it. The batched-shoot model from strategy 5 produces the variant volume needed to keep the rotation healthy. The same discipline anchors the 18 battle-tested Meta Ads tactics playbook.
Hold 10 to 15 percent of monthly spend in compliance reserve
Account disables happen. Meta tightens policies. Creative gets flagged. Landing pages get re-scanned. The operators who survive these events are the ones who hold 10 to 15 percent of monthly spend in reserve specifically for compliance disruption.
The reserve covers the cost of legal review on new creative, the agency time to rebuild campaigns after a disable, additional creative production to replace flagged variants, and the LegitScript and Meta certification work when policy interpretation changes.
Operators who run with zero reserve usually need to pull from non-paid budgets when the disruption hits, which makes everything else worse simultaneously.
Run Stories only on warm retargeting, not cold acquisition
Stories carry meaningful cost in cold-audience acquisition that small budgets cannot absorb efficiently.
The format works much better as a retargeting and reinforcement layer for warm audiences (people who have engaged with the brand, watched 50+ percent of a Reel, visited the site, or read 75 percent of an educational article).
The right small-budget Stories allocation is 8 to 12 percent of social spend, all targeted at warm audiences, with creative pulled from edited Reels variants to keep production cost low.
Operators who run Stories on cold audiences usually see CPM 30 to 50 percent above their Reels CPM with worse conversion economics. The format earns its keep on warm retargeting. It does not on cold prospecting at small budgets.
“The advantage is in the discipline, not the budget. Operators who apply 10 to 12 of these consistently produce admission volume comparable to operators spending two to three times more.”
Preston Powell, Chief Executive Officer, Webserv
How Profound Treatment drove 31 admits and a 42% drop in cost per viable in one quarter
Broad match pivot, negative keyword management, and intake-level conversion tracking turned a fragmented paid strategy into a predictable admissions engine.
Read the case study →68 viable VOBs at $4,529 cost per viable
What this looks like all together: a sample $14K month
For a treatment center running $14,000 a month on Meta with the full playbook applied, the allocation typically lands at:
 Infographic titled ‘The $14K sample month: allocation by line item’.
- $5,000 to $6,500 on Reels (cold prospecting + warm retargeting)
- $3,000 to $4,000 on educational carousels (consideration-stage family members)
- $2,000 to $3,000 on single-image feed (retargeting + brand reinforcement)
- $1,200 to $1,800 on Stories (warm retargeting only)
- $400 to $700 on testing (new creative variants, new audience signals)
- $1,000 to $2,000 held in compliance reserve
The creative library underneath this allocation runs 12 to 18 Reels variants, 6 to 10 carousels, 12 to 20 single-image variants, refreshed at the 45 to 60 day cadence covered in strategy 12.
The audience targeting follows the family-first signal stack from strategy 9 with the exclude-zip framework from strategy 4. The tracking layer runs server-side CAPI plus call tracking integration.
Operators who run this configuration consistently produce 5 to 10 admission inquiries per month on $14,000 spend, with admission cost in the $700 to $1,400 range depending on market and payer mix.
The economics work because every dollar in the budget is doing work that contributes to admission volume, not work that produces dashboard metrics without admissions underneath.
 Infographic titled ‘The 14 strategies, grouped into four operational categories’.
Common mistakes that get treatment centers banned
Five mistakes account for most of the platform disables we see across BH operators.
ACCOUNT BAN RISK
Running paid social ads without LegitScript certification is the fastest way to get a treatment center’s ad accounts disabled across Meta and TikTok. Platform reviews are getting tighter year over year — a single disable typically takes 30-90 days to resolve, and many never come back. Verify certification status before any new campaign goes live.
 Infographic titled ‘5 ways treatment centers get their paid social accounts banned’.
Running ads without LegitScript certification. This is the single biggest reason accounts get disabled. Meta and Google both require the certification before serving addiction treatment ads. Treatment centers that try to run ads through unverified accounts get caught within 30 to 60 days, and the disable often takes the entire account, not just the specific campaign.
Meta pixel on PHI-exposing pages. The pixel on a page where users enter health information (insurance verification, condition self-assessment, symptom checker) is a HIPAA exposure under the current OCR guidance. The remediation is to remove the pixel from those pages or to deploy server-side tracking that does not transmit PHI to Meta. Pages that are pure informational content (the blog, the homepage) are lower-risk but still benefit from the migration.
Before-and-after creative. Showing a person “in active use” and then “in recovery” violates Meta’s, TikTok’s, and Snap’s healthcare creative policies. Even when the imagery is anonymized or symbolic, the framing trips the policy enforcement. The compliant alternative is family-perspective creative or educational creative built around compliant ad headlines for rehab.
Lookalike audiences built from PHI. Creating a Meta lookalike from a custom audience of past patients is a HIPAA violation, because the seed audience contains PHI. The compliant lookalike is built from non-PHI audiences (website visitors who consented to tracking, newsletter subscribers who opted in for marketing) and is much smaller in seed size but compliance-safe.
Aggressive geo-targeting of “wealthy zips.” Beyond the operational inefficiency of include-zip targeting, micro-targeting wealthy neighborhoods can read as discriminatory targeting under emerging healthcare advertising scrutiny. Broader geography with audience-signal layering is both more effective and lower compliance risk.
The combined cost of these mistakes is roughly equivalent to the value of running the program correctly in the first place. Operators who avoid these five mistakes usually maintain stable accounts. Operators who hit any one of them face account disables, regulatory exposure, or both.
WHAT WORKING REHAB PAID SOCIAL DOES
- Active LegitScript certification verified before any campaign launches
- HIPAA-safe pixel and CAPI deployment with signed BAAs
- Compliance-reviewed ad copy on every creative variant
- Targeting that respects 18+ and no-retargeting health restrictions
- Designated internal owner for platform policy compliance
WHAT BANNED ACCOUNTS DID
- Run paid social through any platform before LegitScript clears
- Standard Meta pixel deployment without HIPAA review
- Outcome claims (“we save lives,” “guaranteed recovery”) in ad copy
- Retargeting audiences built from health-related site visitors
- Compliance treated as an agency-handles-it problem
How to evaluate a paid social agency for behavioral health
If you are hiring or auditing an agency for behavioral health paid social, six questions separate the operators who understand 2026 from the operators who are still running 2020 playbooks.
Operators evaluating agencies should also read our honest review of marketing agencies for rehabs and our Google Ads strategy guide, because most BH treatment center programs cannot run paid social in isolation. The strongest accounts integrate paid social with paid search and organic surfaces. Operators who want to skip the evaluation work can start from our scored ranking of the top paid social ad agencies for rehab marketing, which applies the same six diligence questions to the firms already running 2026 stacks. For how paid social fits the full channel mix, see our complete guide to behavioral health marketing.
- Show me your last LegitScript-certified account onboarding timeline. Real BH paid social agencies onboard certification-aware. Agencies that have not navigated LegitScript should not be running your social.
- Walk me through your Conversions API implementation on a current client. The implementation should be server-side, identity-hashed, and PHI-aware. If the answer involves the Meta pixel as the primary tracking layer, the agency has not updated for 2026.
- Show me a Meta creative that was disabled in the last 90 days and explain why. Agencies that say none of their creative has been disabled either run small enough to fly under enforcement or are not running aggressively enough to scale. The right answer is “here is the one that got flagged, here is what we changed, here is the version that ran.”
- What is your family-vs-patient targeting split for residential programs? Should be 65-75% family-first. Agencies that run patient-first for residential do not understand the buyer.
- How do you handle phone-call conversions for the platforms that do not natively support them? Should involve CallRail or equivalent, server-side CAPI integration, and identity matching. If the answer is “we just use Meta’s lead form,” the attribution layer is incomplete.
- What is your protocol when Meta disables an account? Real agencies have a playbook for this. Most BH accounts get disabled at least once. The agencies that recover accounts inside 14 days are the ones with the relationships, the documentation, and the certification stack already in place.
The agencies that answer all six well are the ones who can actually run BH paid social in 2026. The agencies that fumble even two of the six are usually the ones whose clients are reading this guide because their account just got disabled for the third time.
Frequently asked questions about paid social for treatment centers
Can we still run Meta ads for our treatment center in 2026?
Yes, with the right certification stack. The combination of LegitScript certification, Meta addiction treatment approval, server-side Conversions API tracking, and compliant creative makes BH advertising on Meta both possible and effective. Treatment centers running this stack are scaling on Meta in 2026 at unit economics similar to or better than 2022.
What does not work in 2026 is the pre-2024 setup: pixel-based tracking, direct-pitch creative, narrow lookalike audiences from patient data, and unverified ad account ownership. Operators running that setup get disabled, lose accounts, and pay agencies to rebuild what should have been built right the first time.
The right question is not “can we run Meta ads” but “can we run them with the operational maturity 2026 requires.” If your agency cannot describe the CAPI setup, the LegitScript timeline, and the family-first creative strategy in concrete terms, you are paying for legacy execution at 2026 prices.
How does HIPAA enforcement in 2026 change what we can do on paid social?
The shift is from pixel-based tracking to server-side tracking with strict PHI controls. The Meta pixel and similar browser-side trackers cannot be used on pages that handle protected health information without exposing the operator to HIPAA enforcement risk. OCR’s online tracking guidance still covers pixels on pages that collect PHI, and OCR closed 21 HIPAA settlements and penalties in 2025.
The practical implications: remove the pixel from PHI-exposing pages (insurance verification, condition pages, treatment matching tools). Deploy server-side CAPI for all major paid social platforms. Use hashed identity matching to feed conversions back to the platforms without transmitting PHI. Update Business Associate Agreements with any vendor that touches the tracking layer.
The operators who completed this migration in 2024 are running compliant programs in 2026. The operators who did not are now doing the migration under enforcement pressure, which is more expensive and slower than doing it proactively.
What is the right monthly budget to start with on paid social for a treatment center?
The right answer depends on facility size and admission economics, but the floor is usually $8,000 to $15,000 a month in paid social spend to generate enough data for meaningful optimization. Below $8,000 a month, the platforms cannot serve enough impressions to optimize the campaigns effectively, and the data sparseness mirrors the small-budget Smart Bidding problem in Google Ads max-conversions bidding.
For most residential treatment centers, the working range is $15,000 to $40,000 a month in paid social spend, with 60 to 75% of that on Meta and the rest split across the other platforms. Multi-location operators or higher-volume PHP programs often run $50,000 to $100,000 monthly with stable economics.
The scaling path is to start at the lower end of the range, prove unit economics over 90 days, and increase budget in 25 to 40% monthly increments once the cost per admission is stable. Aggressive scaling without proven economics is the most common way to burn through budget without proportional admission growth.
How do we handle ad accounts that get disabled by Meta?
Plan for it as part of the operational reality. Most BH treatment centers running aggressive paid social on Meta get at least one disable over a 24-month period. The fix has four parts.
First, do not panic. The disable is recoverable for compliant accounts. Pulling spend from the rest of the marketing program in panic mode usually makes things worse. Second, identify the specific policy violation. The Meta notification is sometimes vague. Compare the recently-served creative against the addiction treatment policy and the healthcare advertising policy. Look at the audience configurations. Check whether the LegitScript or Meta certification has lapsed.
Third, submit an appeal with documentation of the certification stack and the policy compliance. The appeal flow is documented but the response times have been slower in 2026 than in prior years. Expect 7 to 21 days for resolution on a clean appeal. Fourth, if the appeal fails, rebuild on a fresh ad account with a different Business Manager structure, with all of the compliance issues from the original account remediated. Most agencies should have a contingency Business Manager already provisioned for clients in this category.
Should we run TikTok and Snap if our patient demographic is older?
Probably not, or only at minimal allocation for brand awareness. TikTok and Snap are most effective for treatment centers focused on 18-29 patient populations. For centers focused on 35+ patients, the audience-fit gap is too large to justify significant spend.
The exception is if the family member is in the younger demographic, which happens for centers treating older patients whose adult children are doing the searching. In that case, TikTok and Snap can have a role at 5 to 10% of social spend, but Meta and YouTube usually still outperform them on family-decision-maker targeting.
Older patient populations (50+) are usually best reached through Meta, YouTube, and selective LinkedIn (for referral sources). The TikTok/Snap allocation should be data-driven from the facility’s actual admission demographics, not from a generic best-practices framework.
What does the compliant content layer look like alongside paid social?
Paid social works better when there is an organic content layer that prospects can land on after the ad click. The landing page is the conversion surface, but the surrounding site content is the trust surface. Operators who try to drive paid social traffic to thin landing pages with no supporting content underneath convert at lower rates than operators with a deep content library.
The implication is to invest in the content layer in parallel with the paid social layer. Service pages, location pages, and a real blog produce the trust signals that make the paid social conversion path work. The commercial layer feeds the conversion, the content layer earns the trust.
For operators with limited content budget, the paid social ROI is much better when even modest content investment runs alongside the ad spend. The two channels are complementary, not competing. If you want a second opinion on whether your paid social setup is configured for 2026 compliance and 2026 optimization, reach out for a social audit and we can walk through your tracking layer, creative library, and platform compliance posture before the next core platform update lands.
The perspective in this article comes from 9 years working exclusively inside behavioral health.
We are a team built by people in recovery who understand that behind every admission is someone asking for help. If that resonates, get to know us.
Mitch Marowitz is the Director of Paid Media at Webserv, a digital marketing agency for treatment centers.