revenue cycle management is the single highest-impact operational layer in a treatment center. Most operators never treat it that way.
Every marketing dollar spent and every admission closed has to move through RCM before it becomes cash. If that pipe is leaking, growth elsewhere won’t fix it.
This guide covers what behavioral health billing looks like when it’s done well. We walk through the six core levers of a functioning RCM operation, the benchmarks worth tracking, and what separates billing teams collecting 90% of possible revenue from those accepting whatever the insurance company pays first.
Key Takeaways
- A 15-point collection rate difference on $9M in expected revenue is $1.35M per year. Same clinical work. Different billing operation.
- Most “uncollectible” AR is actually “nobody made the phone call” AR.
- Paying less for billing often means collecting less. The math rarely works out in your favor.
- In behavioral health, pushing back on denials is not a tactic. It is the operation.
- Slow VOBs hand admissions to competitors. That lost revenue never appears in any report.
- If your UR is mediocre, patients leave earlier than they should. Those unbilled days never existed, so they never show up as a loss. But they are the difference between a center growing and a center stagnating.
Why billing is where treatment center growth actually compounds
I had a conversation last month with a treatment center owner who was proud of the fact he was paying his billing company 5% of collections. A hell of a deal, he told me. Bargain rate.
The problem was his billing company was collecting on 75% of the claims they submitted. I asked him if he’d like to be at 90%. That’s a 15-point lift on top-line revenue. I could charge him twice as much, around 10% of collection, and he’d still walk away with more cash in his pocket every month than he does now.
That conversation is not unusual.
Treatment center operators think about billing the way they think about plumbing: something you hire out and forget about. If the bills go out and some money comes back, the billing company is doing its job.
Low fee = good deal.
That framing quietly bankrupts treatment centers every year.
revenue cycle management is the single highest-impact operational layer in a treatment center. It sits between the clinical work and the money that pays your mortgage. Every marketing dollar you spend, every admission you close, every clinical hour you deliver has to transit through RCM before it turns into cash.
If that pipe is leaking 20, 30, 40% of what it should be moving, you don’t need more marketing. You need a better billing operation. For the broader marketing-to-admissions context, see our admission operations and billing services.
This guide covers what behavioral health RCM actually looks like when it’s done well. We will cover VOBs, utilization reviews, claim submissions, denial managements, collections.
Alongside the fundamentals, we will also go over what separates the billing operations collecting 90% of possible revenue from the ones stopping at whatever the insurance company feels like paying.
Your billing company should not be a yes-man. We’re the ones that interface with the insurance companies. We deal with the audits, the SIU reps, the care managers. Treatment centers telling their billing company what to do have it backwards. The billing company should be telling the treatment center what needs to happen. Our guide to signs it is time to change billing companies covers what to do when it is not.
Kyle McHenry, Founder of Revenue Logic
The three LA facilities I’ll reference throughout this guide came in with about $1.4 million in legacy receivables their prior billing company had abandoned. This was not because the claims were uncollectable, but because closing them required phone calls and pressure.
Two months after we took over, we’d recovered about $700,000 of that.
That’s the gap between what RCM looks like when it’s treated as plumbing versus when it’s treated as the operational center of gravity it actually is.
DEFINITION
Revenue Cycle Management (RCM)
The end-to-end process of capturing revenue for a treatment center, from insurance verification through claim submission, payment posting, denial management, and patient collections. RCM in behavioral health carries category-specific complexity (UR, ROI compliance, OON benefit assignment) that general healthcare RCM frameworks miss.
What makes behavioral health billing different from general healthcare
Every vertical in healthcare has its billing quirks. Behavioral health sits in a particularly hostile corner of the insurance ecosystem, and the hostility isn’t accidental.
Insurance companies make money by not paying claims. The Mental Health Parity and Addiction Equity Act exists to prevent some of this. The Act requires payers to apply the same financial and treatment limits to behavioral health as to medical/surgical care. But enforcement is uneven, and operators have to know the law to use it as a tool in denial appeals. The polite industry framing is “utilization management” or “medical necessity review.” The practical effect on your collections is identical: payers throw up flags to stop the financial bleeding.
I see audit reports constantly where an insurance company has denied the same patient’s claim with three different reasons in three different weeks.
“Lacking authorization.” “Ineligible provider type.” “Incorrect coding.” “Needs itemized bill.”
Prior authorization is one of the most predictable revenue leaks in behavioral health. The workflow is well-documented but rarely executed with consistency, which is why operators who fix prior authorization first typically see the fastest revenue uplift inside RCM.
None of it true.
Sometimes other claims for the same patient in the same month have processed and been paid cleanly. The denial isn’t a real objection. It’s a delay tactic.
In most of healthcare, billing teams push back occasionally. In behavioral health, pushing back is the operation. If your billing team accepts what the insurance company tells them on a denial, you’re leaving half the revenue on the table. Our denial management guide covers the appeal side.
Three specific patterns that don’t exist in other specialties
TRICARE claims take six months to process. Not because the work is complex, because TRICARE is that slow and they will drop a claim if you stop calling on it. You have to pursue those claims aggressively from the day they’re submitted until the day they pay. The minute you let one rest, it dies.
Most general-healthcare billing teams don’t have the tempo for that kind of sustained pursuit.
Out-of-state exchange fraud is a live issue. Blue Cross and Blue Shield of Oklahoma has alleged in court that a handful of California programs took $36 million in wrongful payments from 2021 to 2024, with patients saying brokers falsified Oklahoma addresses to get them onto the plan. When a payer finds that pattern, the treatment centers that admitted on those policies are left holding the claims.
If your operation is accepting those policies in volume, you end up holding the bag when the insurance company decides to clean house. A good billing operation sees this pattern in the VOB and tells the treatment center not to admit those patients.
A lazy operation admits them and then watches the revenue disappear six months later.
Insurance carriers silently update coding requirements. UnitedHealthcare recently changed their accepted code set with no advance notice. They simply started denying claims that met the prior specification. Generalist billing teams didn’t notice the pattern for months.
Specialists caught it in a week because we monitor denial reports daily across multiple clients. When the same denial reason starts showing up on four different facilities’ claims simultaneously, the payer has changed something on their end.
The six levers of a functioning RCM operation
What revenue cycle management actually comprises, end to end. If your billing operation isn’t executing each of these at a serious level, you’re leaving money on the table.
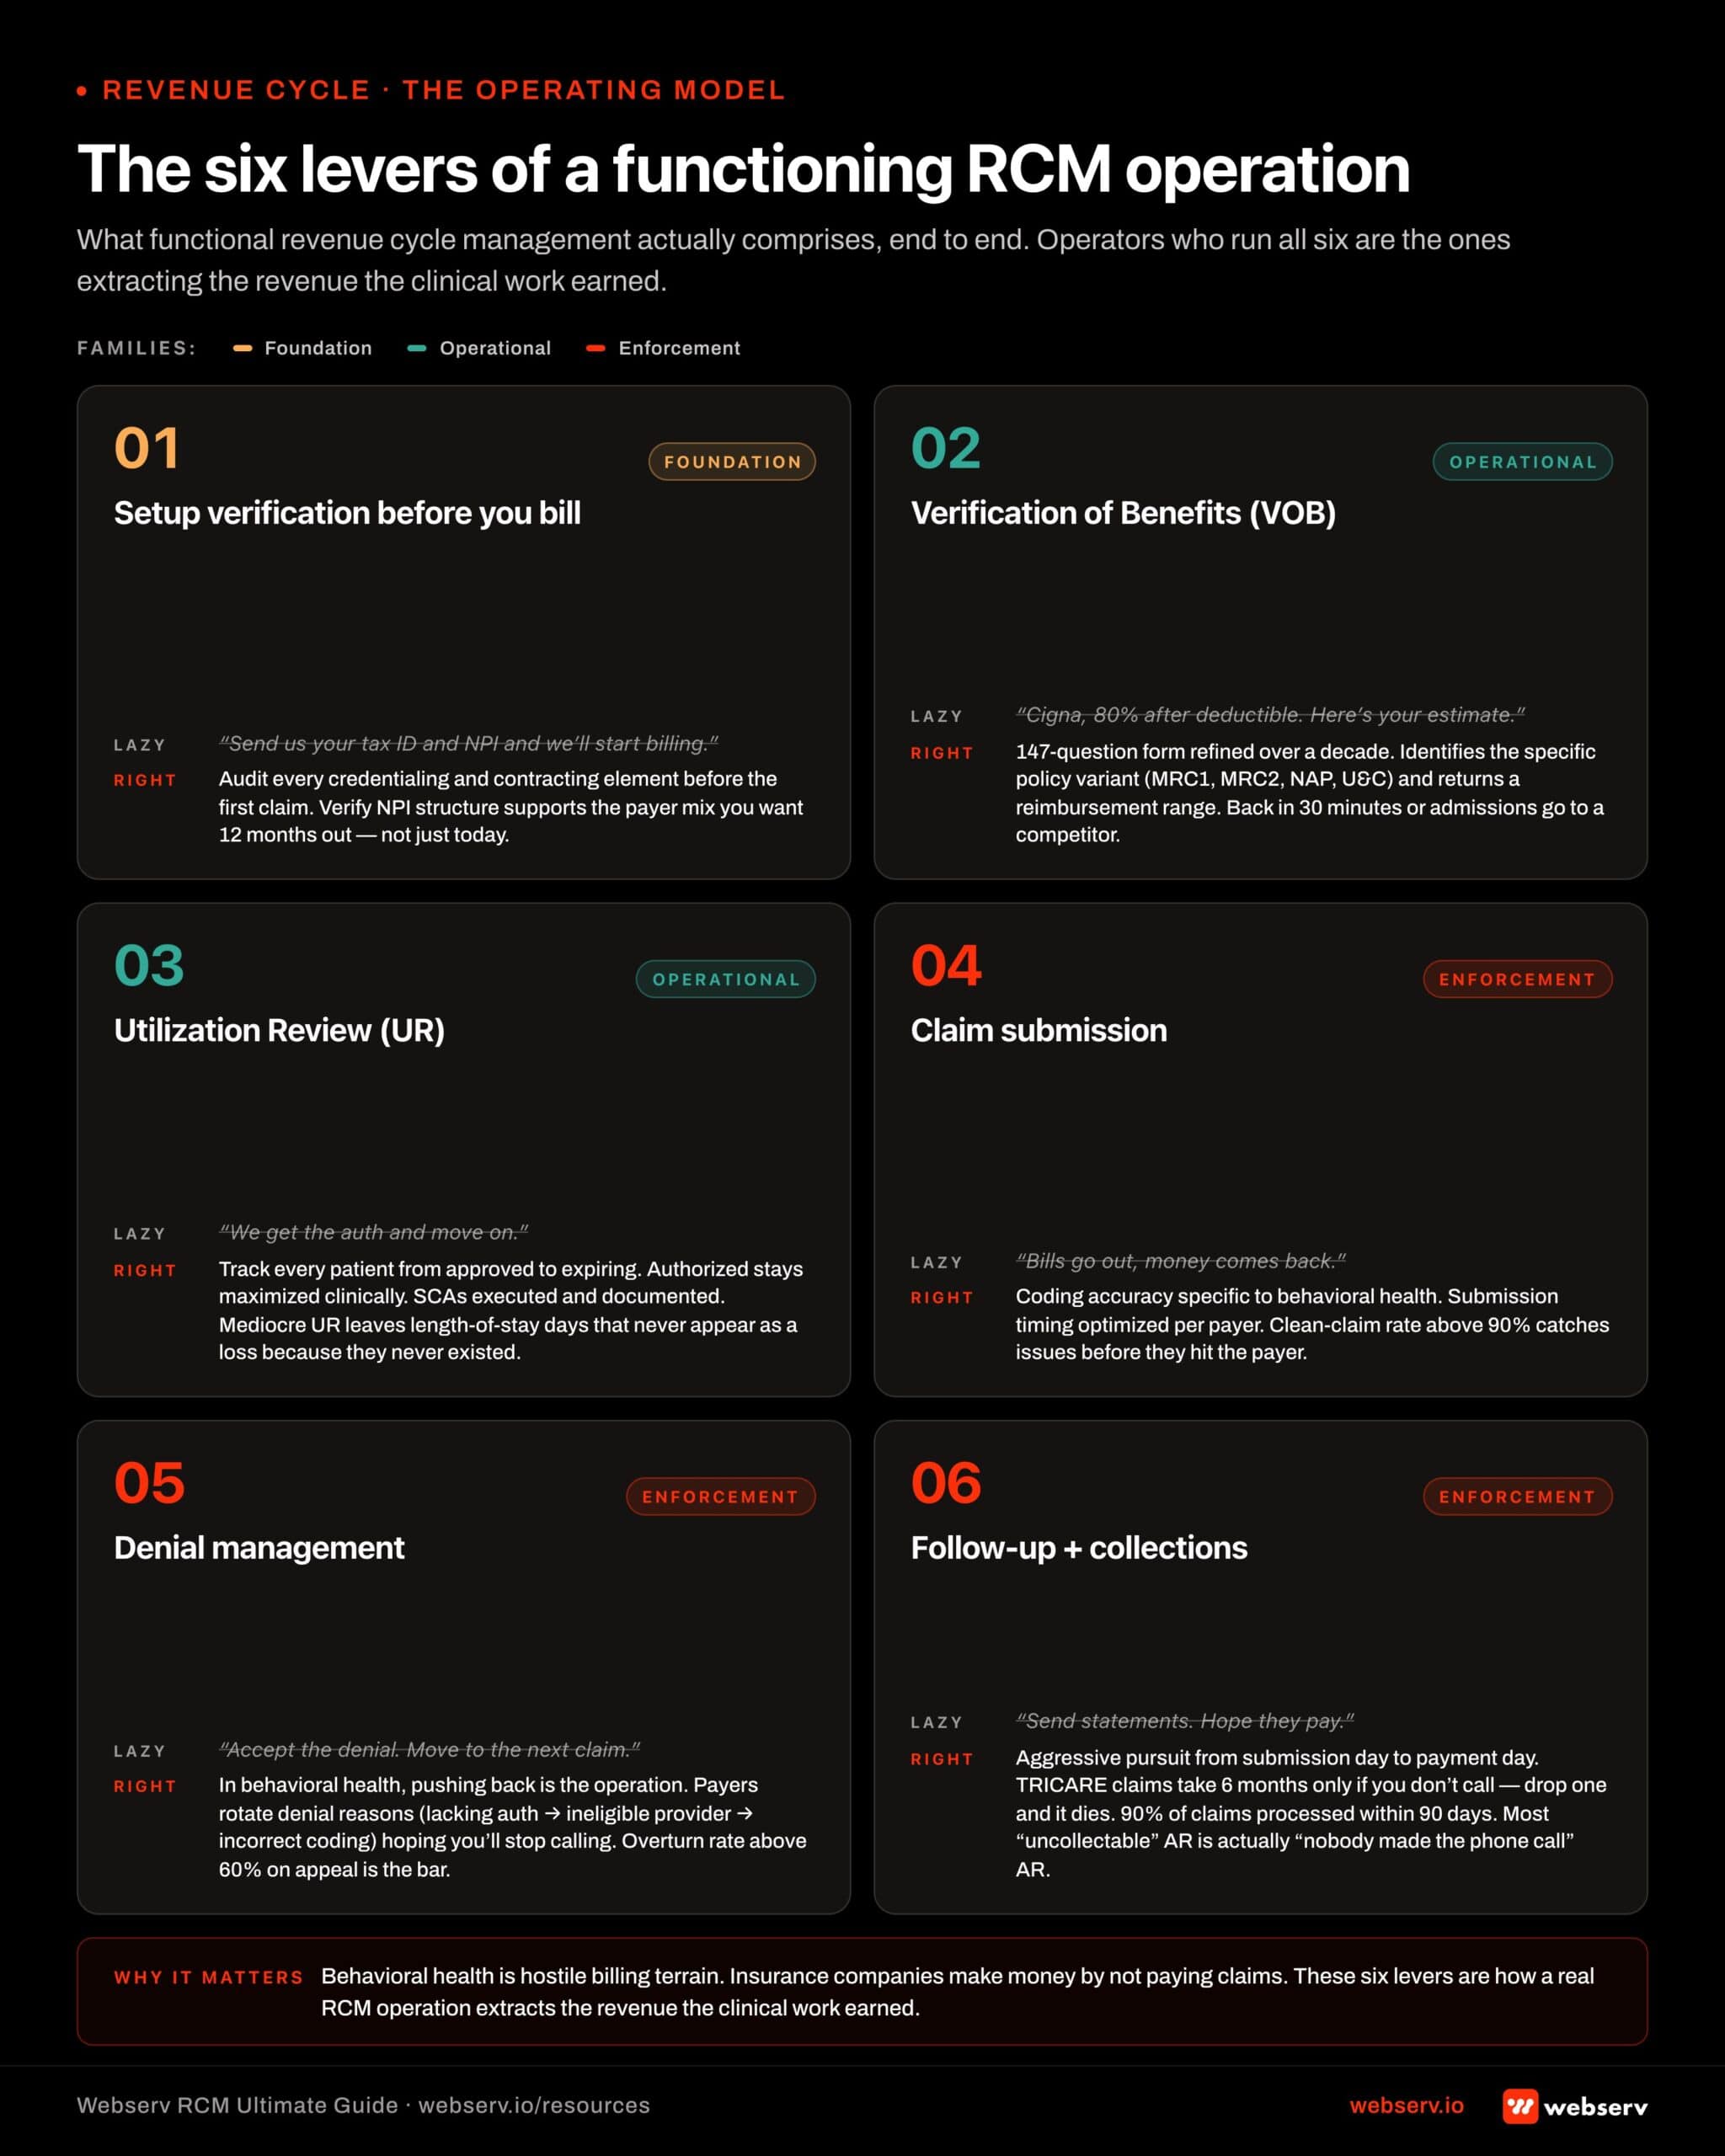 Infographic titled ‘The six levers of a functioning RCM operation.’
Lever 1. Setup verification before you ever bill anything
The first time a new client comes to us, we don’t start billing. We start looking at everything.
State licenses. NPI structures. Joint commission accreditation, including whether the addresses on it are correct. Medical director credentials. How they were set up with EFT. The way the NPIs and EIN are configured together.
Why does this matter?
Because if the setup is wrong, you won’t be able to get in-network contracts later when you want them. Some payers won’t even issue a contract if your NPI structure is misconfigured.
Nobody tells you this going in. A billing company that just asks “do you have a tax ID, do you have an NPI” and starts billing is setting you up for a ceiling on future revenue that you won’t see until you try to scale into network relationships.
What the lazy version looks like: “Send us your tax ID and NPI and we’ll start billing.”
What needs to happen: Audit every credentialing and contracting element before the first claim goes out. Flag anything that’s structured wrong. Fix it before it becomes a ceiling. Verify the provider profile supports the payer mix you want to serve twelve months from now, not just the one you’re serving today.
Lever 2. Verification of Benefits (VOB): speed and depth
VOB is where treatment centers lose the most admissions they could have closed.
If a patient calls and the billing team can get a VOB back in 30 minutes, the treatment center can admit that afternoon. If the VOB takes 24 hours, the patient has already called three competitors and admitted somewhere else.
I’ve heard stories of VOBs taking multiple days. At that point you’re not competing for the patient. The patient is in another building.
Fast is necessary. Accurate is more necessary.
We run every VOB against a 147-question form we’ve refined over ten years. If an issue has ever caused a problem for a treatment center, we ask about it on every VOB from that point forward. If a new issue surfaces, the form goes to 148 questions.
The point isn’t paperwork for its own sake. The point is to catch the things that will turn into denials later, before the patient is admitted.
The lazy VOB: “Cigna, 80% after deductible, here’s your estimate.” Single number.
A real VOB: Identifies the specific Cigna policy type (MRC1, MRC2, nap, usual-and-custom) and returns a reimbursement range based on fresh out-of-network data for that specific variant. Cigna’s different policy types pay materially different amounts on the same services.
Giving a treatment center a single reimbursement number across all Cigna policies is like asking someone what the weather’s like in Chicago without specifying summer or winter.
Why this matters at the bed level. Say you have five residential beds and four are occupied. Two VOBs come back: one for a Cigna MRC1 that will pay around $2,000 a day, one for a marketplace plan that will pay around $900 a day.
Your billing operation either tells you which one to admit, or it doesn’t. If it tells you both are “approved” without the reimbursement comparison, you’ll occasionally fill that last bed with the wrong policy and then have to refuse admissions to patients who could have paid much more.
That’s not the admissions team’s fault. That’s billing failing to do the data work.
For reference, detox typically reimburses around $1,500 a day on a commercial policy. Residential runs you about $45,000 for one month. Full continuum of care through PHP and IOP lands around $60,000 to $70,000 on an average commercial policy. This runs higher on Cigna MRC1s, but lower on some marketplace plans.
Every bed you fill with the wrong policy is a direct hit to top-line revenue. Every VOB delay is a patient walking to a competitor.
Lever 3. Utilization Review
UR is where treatment centers lose the most days they could have billed.
Once a patient is admitted, your billing team’s job is to maximize the clinically appropriate length of stay. That means getting authorization for continued care at each step: residential, PHP, IOP, and making sure the clinical documentation supports the authorization at the depth the insurance company requires. (Our deep dive on the prior authorization workflow in addiction treatment covers what good chart-to-auth alignment looks like step by step.)
Three failure modes I see repeatedly ruin UR outcomes:
The UR team doesn’t know what to prompt from the clinical director. If your UR person isn’t explicitly asking the clinical team to document family dynamic, suicidality markers, treatment history, and which medications have failed.
Before the UR call happens you’re going to lose days. Not because the patient doesn’t meet clinical criteria, but because the call happens without the information that would have gotten the authorization approved.
Billing companies outsourcing UR to foreign countries. This has become more common in the last year and it’s a serious long-term problem. The care managers at insurance companies have a lot of latitude on authorization decisions.
When a UR call happens between someone in India and a ten-year veteran care manager at Cigna, you’re burning the relationship that could have gotten you 14 more days.
The care manager doesn’t know the caller, there’s often a language barrier, and the next month when a different UR rep calls from the same treatment center about a different patient, that care manager remembers. It damages your treatment center’s reputation at the insurance company for years, and you won’t see the damage in a quarterly report.
The prior billing company was fabricating information to get authorizations. This is the ugliest failure mode because the treatment center doesn’t know it’s happening.
We’ll take over a new client, look at their EMR, and find notes that don’t support the authorizations their prior billing company was getting. Sometimes the notes are missing entirely. Sometimes they exist but don’t match what was told to the care manager.
Either way, the treatment center is one audit away from a serious problem; contract network removal, audit findings, SIU scrutiny. We then have to find a tactful way to tell the treatment center that their old billing company was lying on their behalf.
When UR is done well, length-of-stay averages creep up month over month. Not because anyone is gaming the system, but because the documentation is clean, the call goes smoothly, and the care manager on the other end trusts the operation they’re talking to.
Lever 4. Claim submission
Systematize it. Submit weekly without fail. Monitor denial reports daily for patterns that signal a payer has quietly changed something on their end.
This is the most commoditized part of RCM. Almost every billing company does it to some minimum standard. What separates the best operations is how fast they detect pattern changes.
When UnitedHealthcare quietly changed their accepted code set, the specialists caught it within a week because the same denial reason started showing up simultaneously on claims from four different facilities.
That’s the kind of signal you only see when you’re looking at denials daily across a portfolio. If you’re reviewing denials monthly or quarterly, you catch the pattern six months later, after $200,000 of claims have piled up and have to be worked back through.
Lever 5. Denial management
The insurance company denial isn’t the end of the conversation. It’s the opening of a negotiation.
Most denials in behavioral health are strategic. The insurance company is hoping you’ll accept the denial, or at minimum respond in a way that extends the dispute. This might be sending medical records they didn’t actually need, for example, which opens the door to a dozen other questions they can then raise.
When we get a denial that says “lacking authorization,” our response isn’t to send the medical record. Our response is: “We have the auth. Here’s the auth number. Reprocess this claim.” If it’s a real authorization issue, that takes thirty seconds to resolve.
If the denial was fabricated (and most are) the claim reprocesses and pays.
Here’s what the pattern looks like in the aggregate.
Before we got involved with one client, they were being reimbursed on 55–60% of their claims. Not because the claims were unsustainable. The issue was that the billing company was accepting denials it should have been fighting.
Within 90 days of taking over VOBs, UR, submission, follow-up, and denial management, they were at 90%. Same claims. Same patients. Same insurance companies. Different billing operation.
The treatment center never changed a thing about its clinical work. They just stopped having a billing operation that accepted whatever the insurance company said first.
Lever 6. Claims follow-up and collections
The law of diminishing returns says you get 80% of the result from 30% of the effort. Getting the remaining 20% requires cranking on every claim that isn’t paying automatically.
Understaffed billing companies stop at the 80% line. Claims that aren’t paid automatically sit in aging buckets, waiting for someone to make the phone call that would close them. Three months later, six months later, the treatment center writes them off as uncollectible.
The three LA facilities I mentioned earlier came to us with about $1.4 million in legacy receivables their prior billing company had abandoned. Two months later we’d recovered about $700,000 of it.
The claims weren’t hard. They just required phone calls. Nobody had been making the phone calls.
Most “uncollectible” AR in behavioral health is actually “nobody has time to collect this” AR. The distinction matters to your bottom line.
Beyond the manual follow-up work, we’ve built automation that combs through every treatment sheet and flags claims that might be underpaid. Those get sent back to the insurance company for secondary consideration. Underpayment recovery alone often covers our entire fee.
You don’t get that from a billing company focused on low-hanging fruit.
The numbers agencies quote you mean very different things depending on payer mix.
Before you benchmark your performance or compare quotes from other agencies, read this. Real data from real OON treatment center campaigns with no cherry-picked numbers.
Read the report → Free and ungatedA verification of benefits process that takes more than 30 minutes
| What we see: | A facility loses an admit because the VOB took six hours to come back. Sometimes a full day. By the time the rep reaches back out, the patient has already admitted somewhere else. The competing facility had a faster billing partner. That is the entire story |
| Why it matters: | VOB turnaround is the first lever that determines whether you ever see a patient. Marketing spends thousands of dollars to get an inquiry call. The billing process either completes that handoff in under an hour or it forfeits it. |
| The cost: | A $1,500 per day detox stay across a 30-day continuum runs $45,000. Push to PHP and IOP and the lifetime value sits closer to $60,000 to $70,000 per admit, depending on the policy. Each lost admit is a five-figure marketing failure that didn’t happen in marketing. |
| The fix: | Run a 90-day audit on your average VOB turnaround time. Demand 30 minutes plus reasonable hold time as a service standard. If your billing partner cannot tell you what their median turnaround actually is, that is its own answer. |
Filling beds with policies that will never reimburse
ADMITTING WITHOUT A NUMBER
A quieter version of the same mistake: admitting without a rate expectation attached. The VOB confirms coverage. Nobody asks what the payer typically pays for that state, plan, and level of care. PayerLenz exists to close that gap with 500,000+ adjudicated behavioral health claims resolved to alpha prefix and home plan. The point is not to reject patients. It is to admit with your eyes open, and to price the bed correctly against projected AR.
| What we see: | A six-bed facility takes a policy without checking whether the plan type, alpha prefix, or state of issue will actually pay for behavioral health care at the level the patient needs. The bed is occupied. The next call gets refused. The Oklahoma Blue plan is the cautionary example: Blue Cross and Blue Shield of Oklahoma has alleged that California programs took $36 million in wrongful payments using falsified Oklahoma addresses. When a payer unwinds policies like that, the admits built on them go with them. |
| Why it matters: | A bed full of bad coverage is worse than an empty bed. You can’t move the patient out without a clinical reason and you can’t move the next caller in. |
| The cost: | Same math as the slow-VOB problem, but inverted. The slot is gone. There is no recovery. |
| The fix: | Build a pre-admit policy filter into your VOB workflow. Out-of-state exchange plans get extra scrutiny. Group plan types and historical reimbursement data should sit in front of the admissions team before the bed is offered. |
Letting your billing company lie on your behalf about authorizations
| What we see: | We take over a new client. We open the EMR. The notes are thin. The authorizations are full. That gap is one of the most consistent red flags in the industry. Somebody got those auths. The clinical record does not support them. When the insurance company eventually requests medical records for a claims review, the discrepancy becomes the treatment center’s problem, not the previous billing company’s. |
| Why it matters: | This is how facilities end up in audits, recoupment letters, and contract terminations. The previous billing company is long gone by the time the bill comes due. |
| The cost: | Audit defense runs from $25,000 to well into six figures depending on scope. Removal from a contract network can take six figures of monthly revenue off the books overnight. None of that money was ever yours to begin with. You will spend years explaining it anyway. |
| The fix: | Run a quarterly chart-to-auth audit. Pull a sample of recent authorizations. Read the notes that supported them. If a UR person could not have built that auth from those notes, you have a problem. (Our deep dive on the prior authorization workflow in addiction treatment covers what good chart-to-auth alignment looks like step by step.) |
Sending medical records every time the insurance company asks
COSTLIEST BILLING MISS
A denial letter cites missing auth, ineligible provider type, or coding issues. Most of those flags are not real — the payer knows the auth exists and is throwing up obstacles to slow the payment. Send the chart and they will find something new to deny on. Push back first: quote the auth number, force the payer to name the specific record and the reason. If they cannot, the chart stays in the building.
| What we see: | A claim denial comes back asking for medical records. The denial cites missing authorization, ineligible provider type, or coding issues. Sometimes more than one in the same letter. Most of those flags are not real. The insurance company knows the auth exists. They are throwing up obstacles to slow the payment. |
| Why it matters: | Once medical records leave the building, the insurance company has a much bigger surface area to look for things to deny on, and they almost always find something. |
| The cost: | A claim that was going to pay can turn into a 90-day appeal cycle. Some claims never recover at all. |
| The fix: | Train the team to push back before they pull a single chart. The first move is to quote the auth number and force the payer to name the specific clinical record they want, and why. If they cannot, the records stay. |
Outsourcing utilization review overseas
| What we see: | A growing number of billing companies have moved their utilization review operations to firms in India. The cost savings make sense on paper. The downstream effect on authorizations does not. A care manager at the insurance company has wide latitude on what to approve. They approve more for people they recognize and trust. They approve less for callers who do not know the patient or the program and who carry a language barrier into a clinical conversation. |
| Why it matters: | UR is the second checkpoint after VOB that determines what your admit is actually worth. Lose three days of residential and you lose roughly $4,500 at typical reimbursement. |
| The cost: | Multiply across 30 admits a quarter and the math becomes obvious. We have seen length-of-stay drop materially inside a single quarter when offshore UR replaces domestic UR. |
| The fix: | Ask your billing company directly where their UR team sits. Ask how long the lead UR clinician has been working with your specific payer mix. The answer takes ten seconds and tells you everything you need to know. |
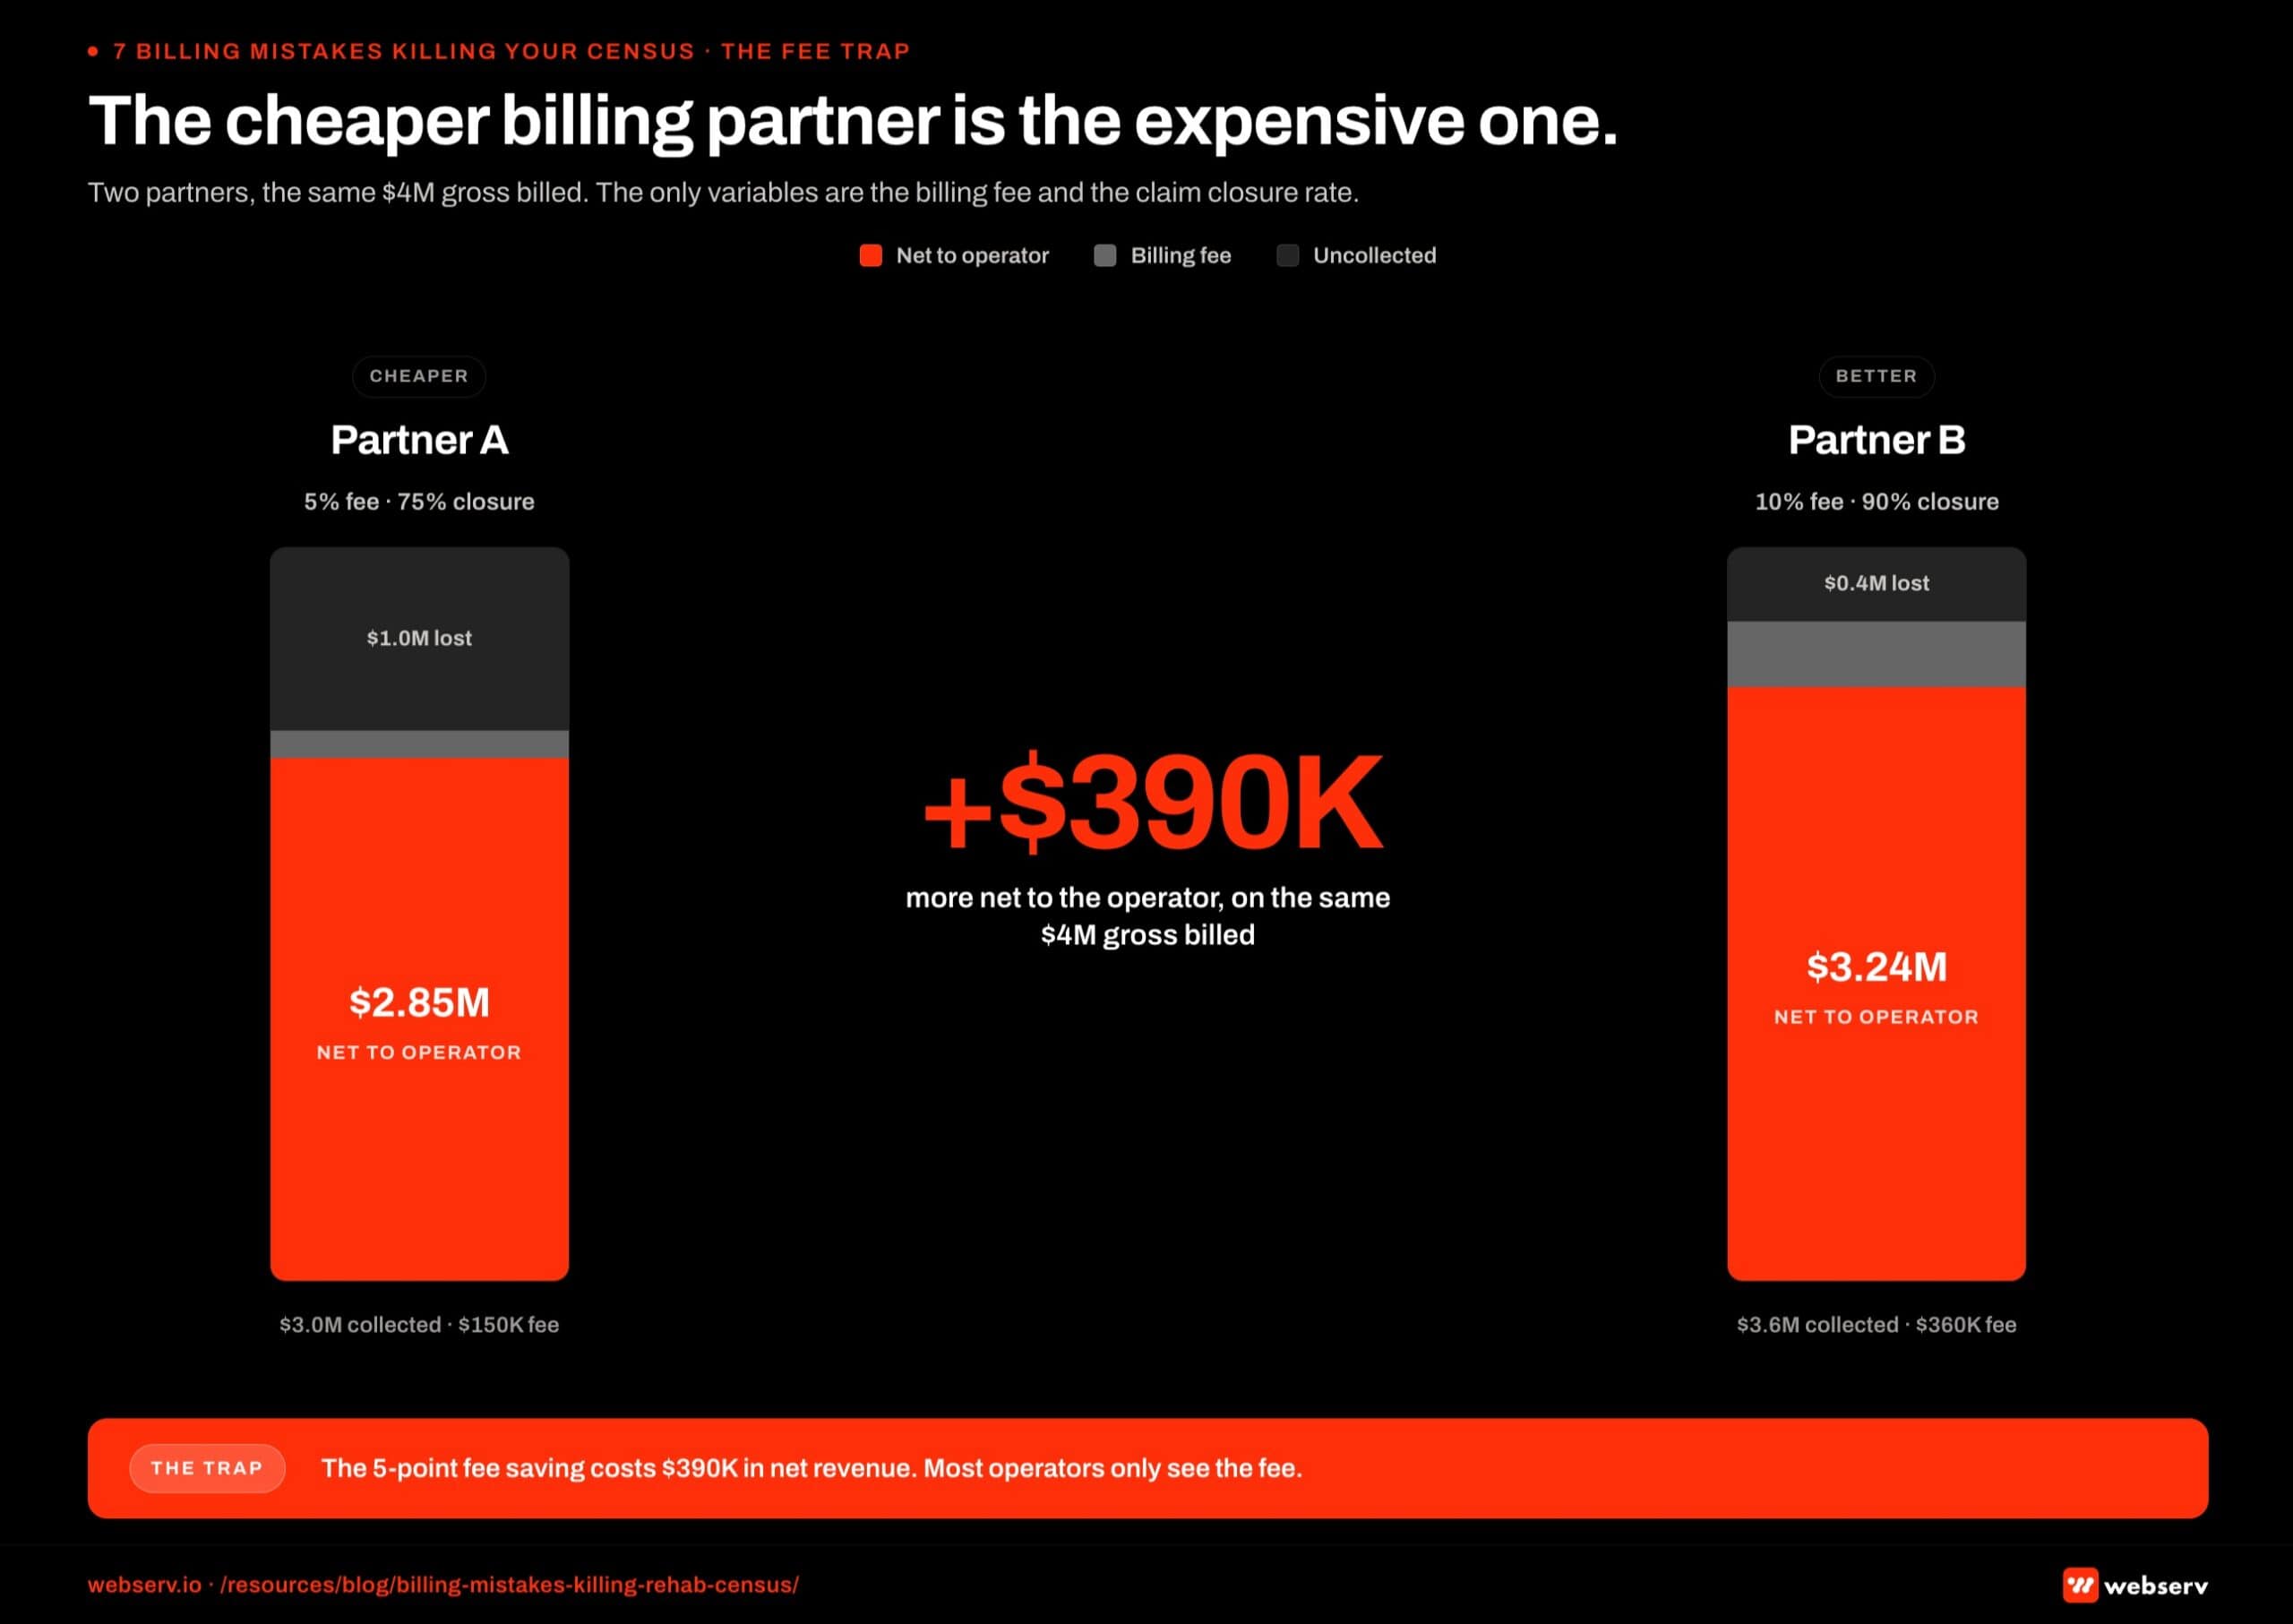 Comparison infographic titled ‘The cheaper billing partner is the expensive one.’
Not knowing your actual claim closure rate
| What we see: | Operators tell us they pay 5% to their current billing company. They cannot tell us what percentage of their submitted claims are actually closing. That is the most expensive missing data point in this industry. |
| Why it matters: | A 5% fee at a 75% closure rate costs more than a 10% fee at a 90% closure rate. The math is not close. Most operators have never been shown either number, so they negotiate on the fee they can see and not the revenue they cannot. |
| The cost: | Run the math on $4 million in annual gross billed. The difference between 75% and 90% closure is roughly $600,000 of recovered revenue per year. The 5-point fee delta is $200,000. The operator saved $200,000 on the fee and walked away from $600,000 in collections. |
| The fix: | Demand a monthly dashboard from your billing partner that shows submitted, closed, denied, and outstanding claims with aging. If they will not build it, they aren’t in a position to defend their performance. (Our billing operations checklist documents the rest of the weekly and quarterly cadence that surfaces these numbers without a separate ask.) |
The hidden attrition is the worst kind. It doesn’t appear in any system because it never existed.
Kyle McHenry, Founder, Revenue Logic
Treating billing as a back-office expense instead of a marketing input
| What we see: | Marketing measures admissions. Billing measures collections. The two teams almost never look at the same dashboard. That is how a treatment center ends up with a healthy admit pipeline and a sick P&L at the same time. |
| Why it matters: | Return on ad spend is not the right metric. Return on invested capital is. The ad dollar that produced the admit only converts when the claim collects. Every billing failure is a marketing failure that never gets attributed to billing. |
| The cost: | The hidden attrition is the worst kind. It does not appear in any system because it never existed. The lost length of stay, the slow-VOB no-show, the claim that never appealed, all of it sits outside the marketing report. |
| The fix: | Run one weekly meeting that pulls the marketing team and the billing team into the same room. Look at admissions, average reimbursement per admit, length of stay, and aging together. The patterns surface within two cycles. |
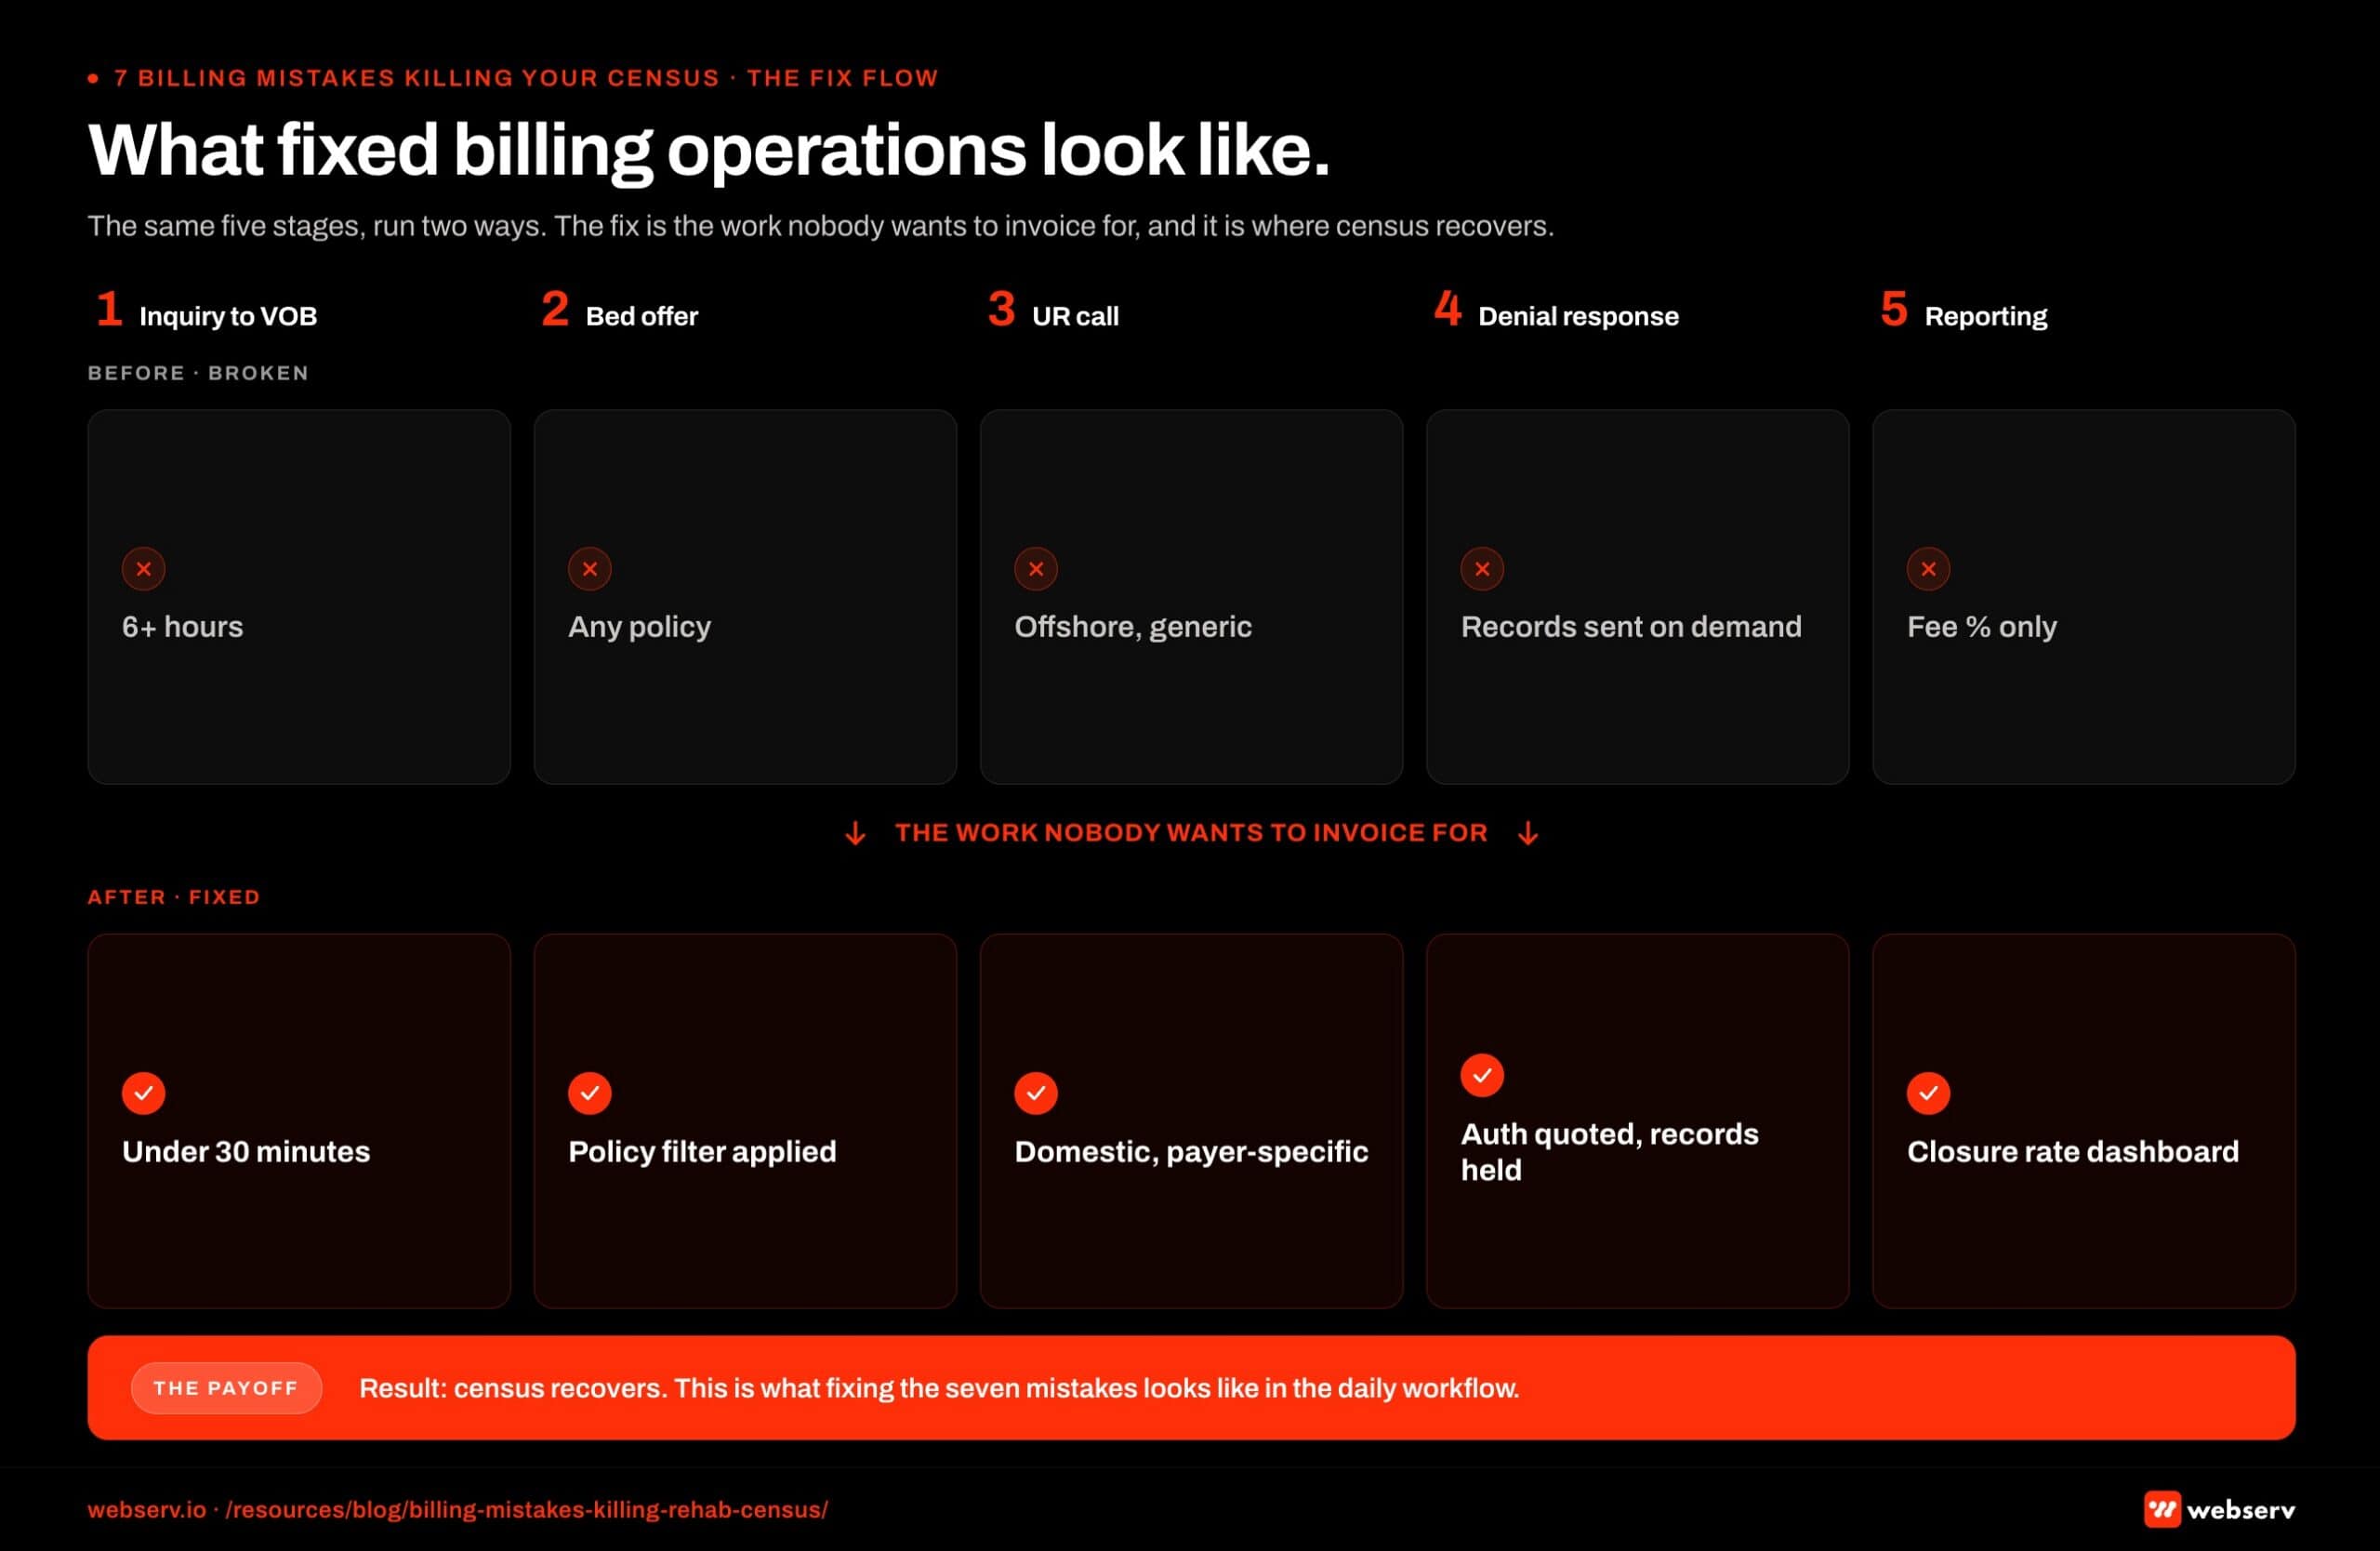 Before and after operations flow titled ‘What fixed billing operations look like.’
Denials are patterns, not random events
Insurance companies do not generate denials at random. Each payer has a denial pattern. Most patterns track to a quiet rule change that the payer did not announce. The Mental Health Parity Act sets the legal frame for parity in behavioral health denials, but enforcement gaps mean payers still apply quiet rules that affect BH claims more aggressively than physical health.
UnitedHealthcare updated its accepted code set last year. There was no email. No payer bulletin. The denials started arriving roughly two weeks later, all citing “incorrect coding.”
Billing partners that monitor pattern shifts caught it in the first week. Billing partners that worked claims one at a time caught it six weeks in, after a measurable revenue drop.
That gap is one of the most expensive operational differences in the industry. Pattern detection on the payer side closes weeks of lost revenue every time a payer changes a rule.
The first question to ask any billing partner: how do they detect denial pattern shifts, and how fast do they identify when a payer has changed a rule?
If the answer is “we work each claim individually,” the operation is reactive. The pattern catches them, not the other way around.
Push back before sending medical records
The most expensive instinct in claims management is sending medical records the moment a payer asks for them.
A claim denial cites missing authorization, ineligible provider type, or coding issues. Sometimes more than one in the same letter. Most of those flags are not real.
The payer is testing whether the claim will be worked or absorbed. If you ship the records, the payer now has a much larger surface area to deny on. They will find something on the records that the claim itself was not asking about.
The right first move is to quote the original auth determination, the date of authorization, the auth number, and the payer’s own confirmation language. Force the payer to articulate which specific clinical record they need and why.
A meaningful percentage of denials reverse at this stage. The records never leave the building. The claim pays.
Train the team to ask: what did the payer actually ask for, and what is the smallest acceptable response?
Match every authorization to its clinical record, quarterly
The audit pattern that takes down treatment centers does not start with audits. It starts with authorizations that the chart cannot support.
A previous billing company got the auth. The clinical record does not justify it. When the insurance company eventually requests medical records on a claim from that admission, the discrepancy becomes the treatment center’s problem.
Catching this before the payer does requires a quarterly chart-to-auth audit. Pull a sample of recent authorizations. Read the clinical notes that supported each one. Ask whether a UR specialist could have built that auth from those notes.
If the answer is no on more than 5% of the sample, the chart-auth alignment work has to happen before any new appeals get filed. Otherwise the appeal is exposing a deeper problem.
This audit also surfaces the structural issue most operators do not see: the previous billing company was not lying about the auth. The clinical documentation was thin enough that someone had to interpret it generously to land the auth. The interpretation is the audit risk.
Track payer-specific code-set changes
Coding denials are concentrated in a handful of payers each year. The payers do not announce code-set changes. The denials are the announcement.
A billing partner that works in this vertical at scale should be able to tell you, this week, which payers have changed accepted codes in the last 60 days, what the new accepted set is, and whether the change is documented anywhere outside the denial pattern itself.
For a single-location IOP center, the operational answer is: subscribe to a billing partner who maintains this database, and review the denial pattern report monthly.
For a multi-location organization with internal billing, build the database yourself. Tag every denial with payer, denial reason code, claim type, and date. Run the report quarterly and look for clusters.
The clusters are the rule changes. The rule changes are recoverable revenue.
Stop sending claims to payers that do not require submission
A pattern we see often: a treatment center is submitting five and six-figure claims to payers that do not need or expect those claims at all. The claims sit. The payer does not pay because the claim is not actionable on their end. A serious verification of benefits process catches these routing problems before admission, but most checkbox-version VOBs miss them entirely.
This is a specific behavioral health pattern that does not exist in most other healthcare verticals. Some out-of-network payers expect a balance bill or a member submission, not a provider claim. Some self-funded plans route through a TPA that the provider has never been credentialed with.
Submitting claims into those workflows generates denial volume that is not actually a denial pattern. It’s a routing error.
The remedy is a payer-by-payer routing audit on the existing claim portfolio. For every payer with significant outstanding receivables, confirm that claims are being submitted into the workflow that payer expects.
Some of those claims need to come back as member submissions. Some need to be re-routed to the right TPA.
A serious billing partner runs this audit during onboarding. If your current partner has not, the cleanup is usually six figures of recoverable revenue at a mid-sized program.
Do not outsource utilization review
The single fastest path to a higher denial rate is moving UR offshore.
A care manager at the insurance company has wide latitude on what to approve. They approve more for callers they recognize and trust, and less for callers they do not know who carry a language barrier into a clinical conversation.
When a domestic UR specialist who has worked the same payer for five years calls about a patient, the care manager is looking at a familiar voice on a clean program. The clinical conversation is a clinical conversation.
When an offshore UR contractor reads a script for the same patient, the care manager is reading the audit risk profile in real time. Authorizations come back shorter. Lengths of stay compress. Mental health parity rules are supposed to prevent shorter authorizations for BH versus physical health, but in practice the parity gap is what UR teams are negotiating against on every call.
Compressed lengths of stay produce more denial-adjacent failures: missed continuity of care, level-of-care transitions that don’t get authorized, and final claims that arrive without the supporting auths.
The cost savings of offshore UR are visible in the billing fee. The downstream cost lives in lost reimbursement that does not get attributed to UR. Most operators never connect the two.
The numbers agencies quote you mean very different things depending on payer mix.
Before you benchmark your performance or compare quotes from other agencies, read this. Real data from real OON treatment center campaigns with no cherry-picked numbers.
Read the report → Free and ungatedMeasure denial recovery rate, not denial rate
UPSTREAM SIGNAL, DOWNSTREAM DENIALS
Denials fought after the fact are the most expensive place to win a rate argument. Knowing before admission what the payer typically pays for that level of care collapses a whole class of “underpayment” appeals. PayerLenz attaches expected out-of-network reimbursement figures to real-time eligibility checks, so admissions and billing are working from the same expected number rather than discovering it in an EOB three weeks later.
The metric most treatment center owners ask their billing partner about is denial rate. The metric that actually matters is denial recovery rate.
A 95% denial rate paired with an 85% recovery rate is a stronger operation than a 70% denial rate paired with a 30% recovery rate.
The first program is winning the appeal fight. The second program is letting denials sit.
Most billing partners can produce the denial rate. Few can produce the recovery rate by payer. Even fewer can produce it by denial reason code, which is the report that actually drives operational improvement. Compare against the RCM partners that publish recovery-rate benchmarks when evaluating.
Demand a monthly report that shows denial volume by payer, recovery rate by payer, and average days from denial to recovery. If your billing partner cannot produce that report inside 30 days, they are not measuring the work.
The benchmarks that actually matter
THE BENCHMARK BEHIND THE BENCHMARKS
Missing from most RCM scorecards: what a claim should pay in the first place. Days in AR and clean claim rate measure billing execution, not rate expectation. PayerLenz maintains a reimbursement benchmark index built from 500,000+ adjudicated behavioral health claims, so operators can compare their allowed amounts against what the payer typically pays for that state and level of care. A 45-day AR looks great until you learn the payments themselves are 30 percent under market.
If you’re trying to evaluate whether your billing operation is performing, here are the numbers worth tracking.
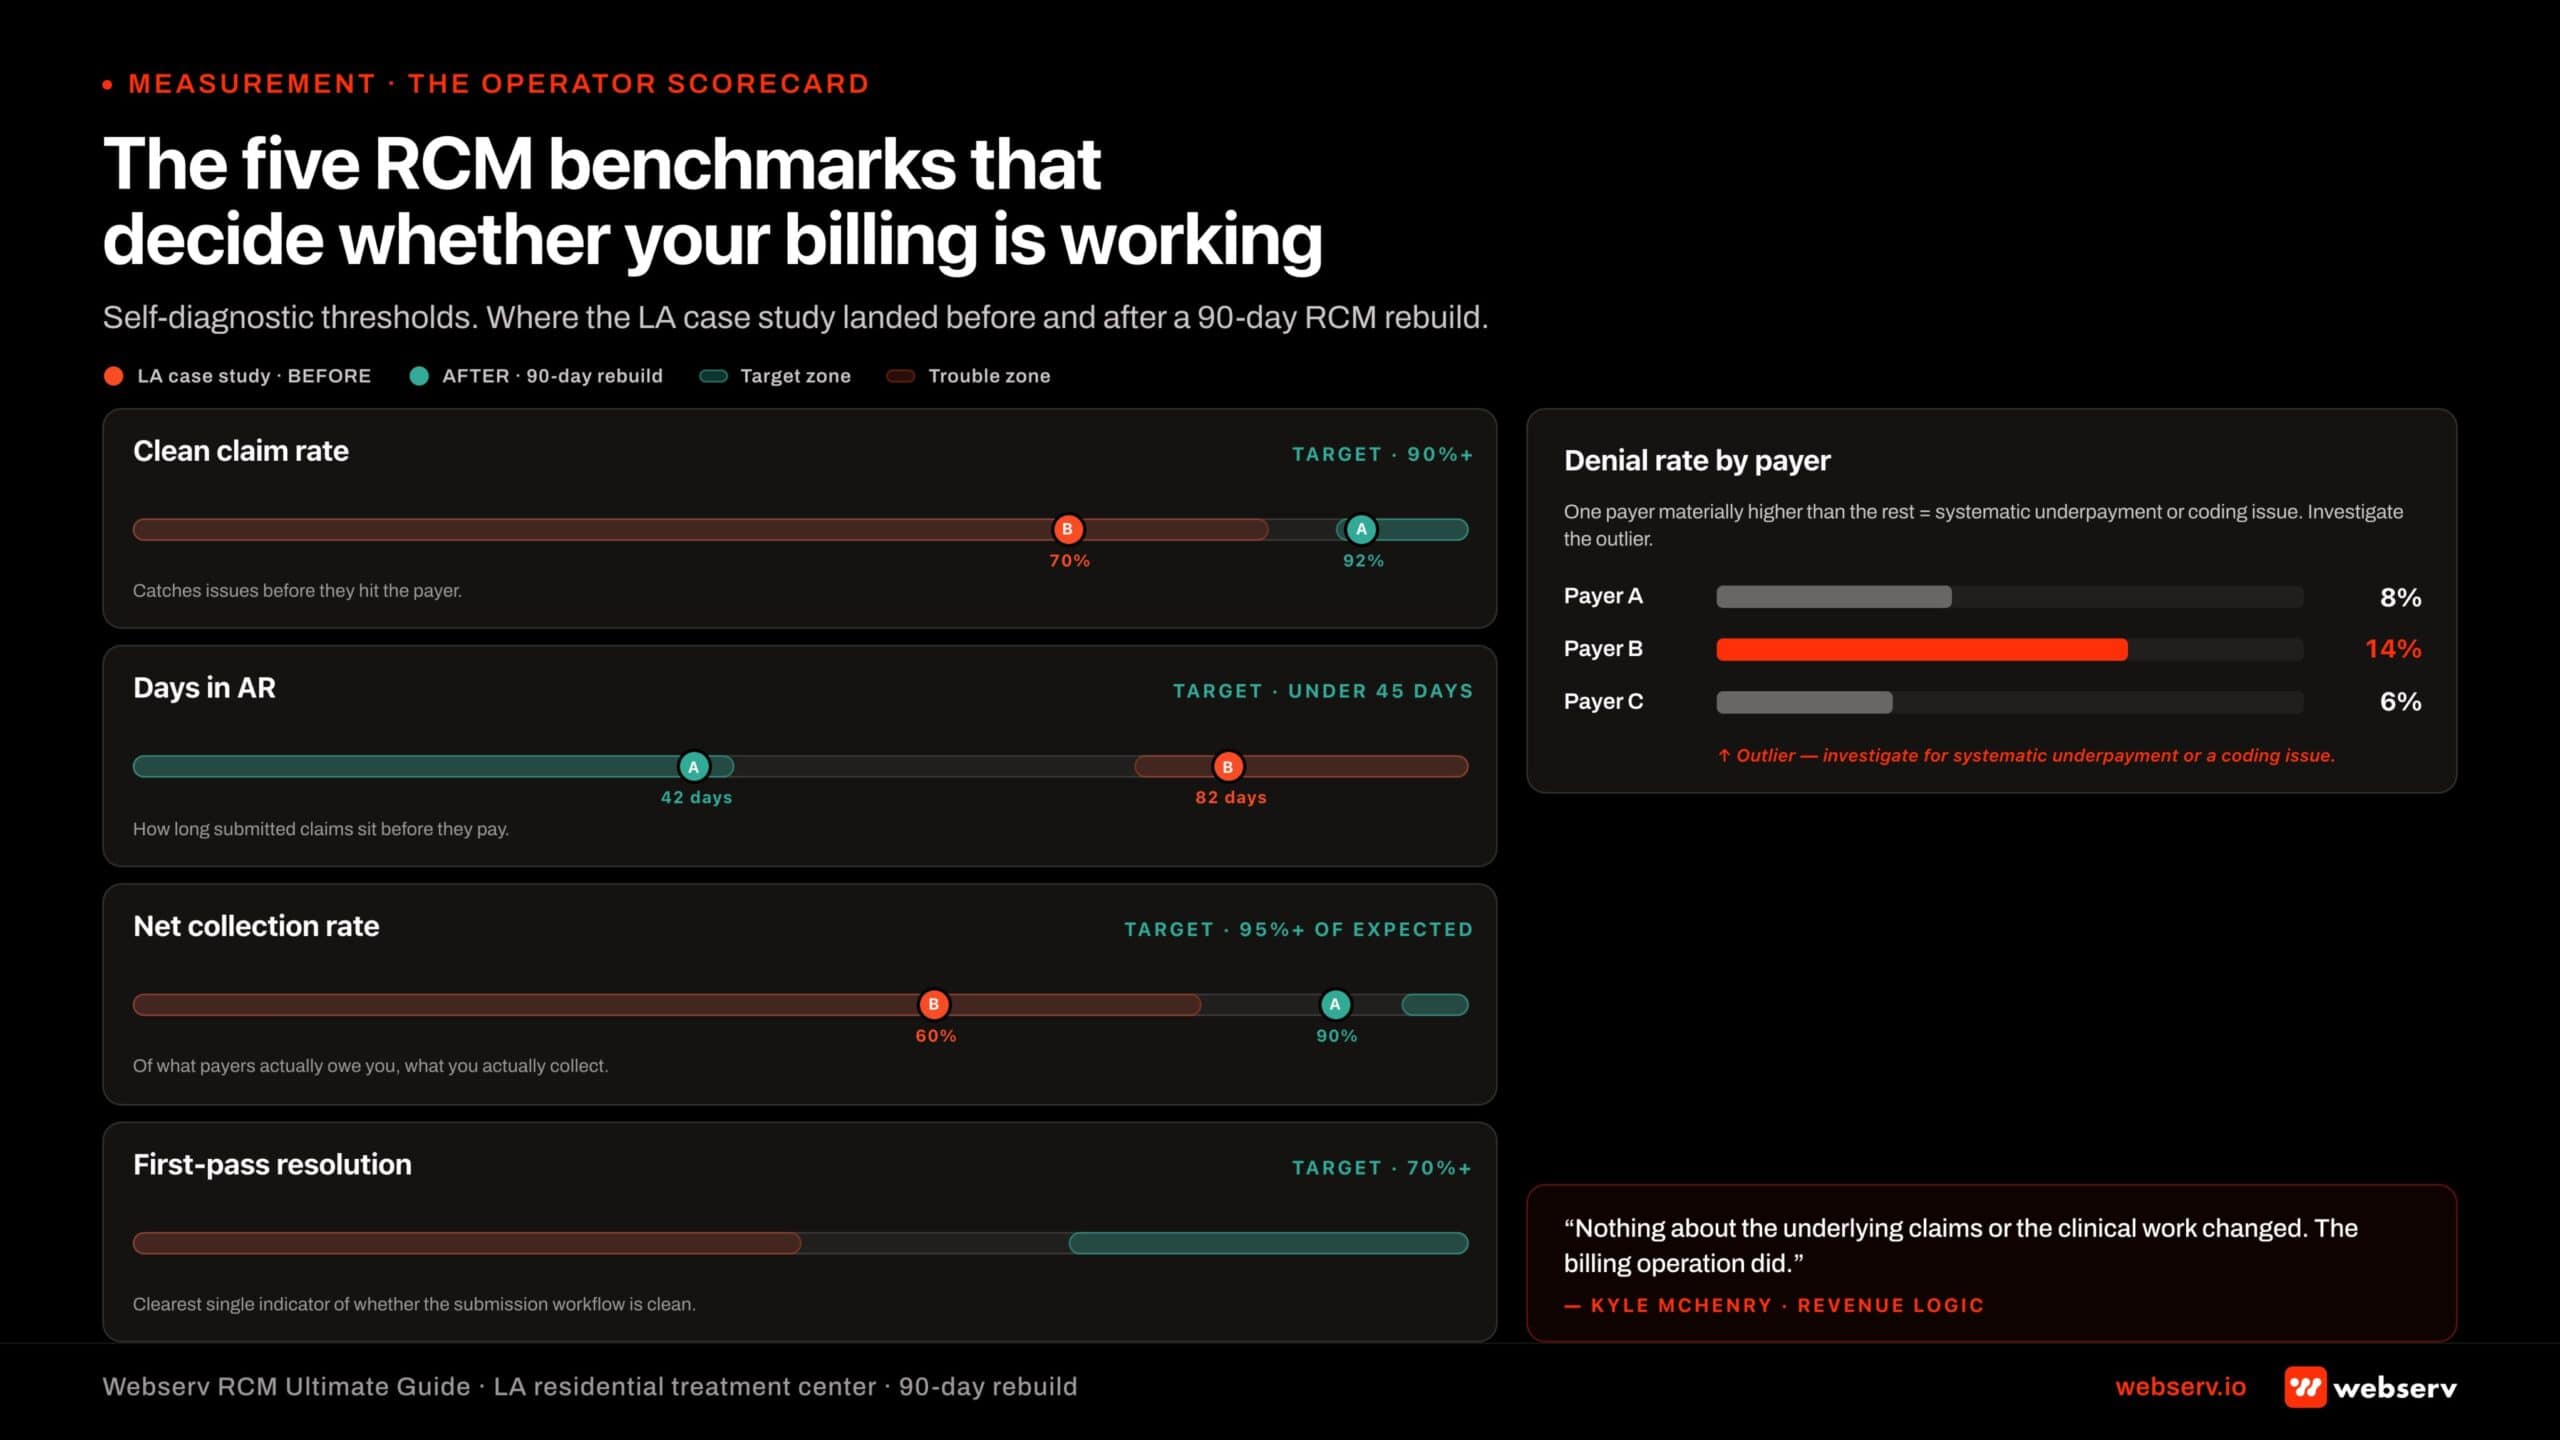 Infographic titled ‘The five RCM benchmarks that decide whether your billing is working.’
Clean claim rate: 90% or higher. Below 85% means either your submission workflow has issues or your clinical documentation isn’t supporting the claim. Above 90% means your billing operation is catching issues before they hit the payer.
Days in AR (DIAR): Under 45 days. Treatment centers commonly come to us at 75+ days in AR. After 90 days of optimization, 30–40 days is achievable on most clients.
Net collection rate: 95% or higher of expected reimbursement. This is the number most operators don’t track, and it’s the one that correlates most directly with actual revenue.
First-pass resolution rate: What percentage of claims pay on the first submission without denial or follow-up. The clearest single indicator of whether your submission workflow is clean. Target 70% or higher.
Denial rate by payer: Which insurance companies are costing you most? If one payer’s denial rate runs higher than others, you either have a coding issue specific to that payer or the payer is systematically underpaying.
If you want to maximize your revenue you need to know what is happening.
The 60-to-90 case referenced earlier: clean claim rate went from around 70% to 92% in 90 days. Net collection rate climbed from 60% of expected to 90% of expected. DIAR dropped from 80-plus days to 42.
Nothing about the underlying claims or the clinical work changed. The billing operation did.
The expensive truths operators don’t see going in
COSTLIEST MISTAKE
Selecting an RCM vendor on headline fee rather than net collections. A 5 percent fee that collects 62 percent of billed charges leaves less in your account than a 7.5 percent fee that collects 78 percent. On a $6M facility, that gap is mid-six figures per year. Ask every vendor for their weighted net collection rate on BH claims by payer tier, not their sales-deck fee.
What treatment center operators don’t realize about billing before they’re running one at scale.
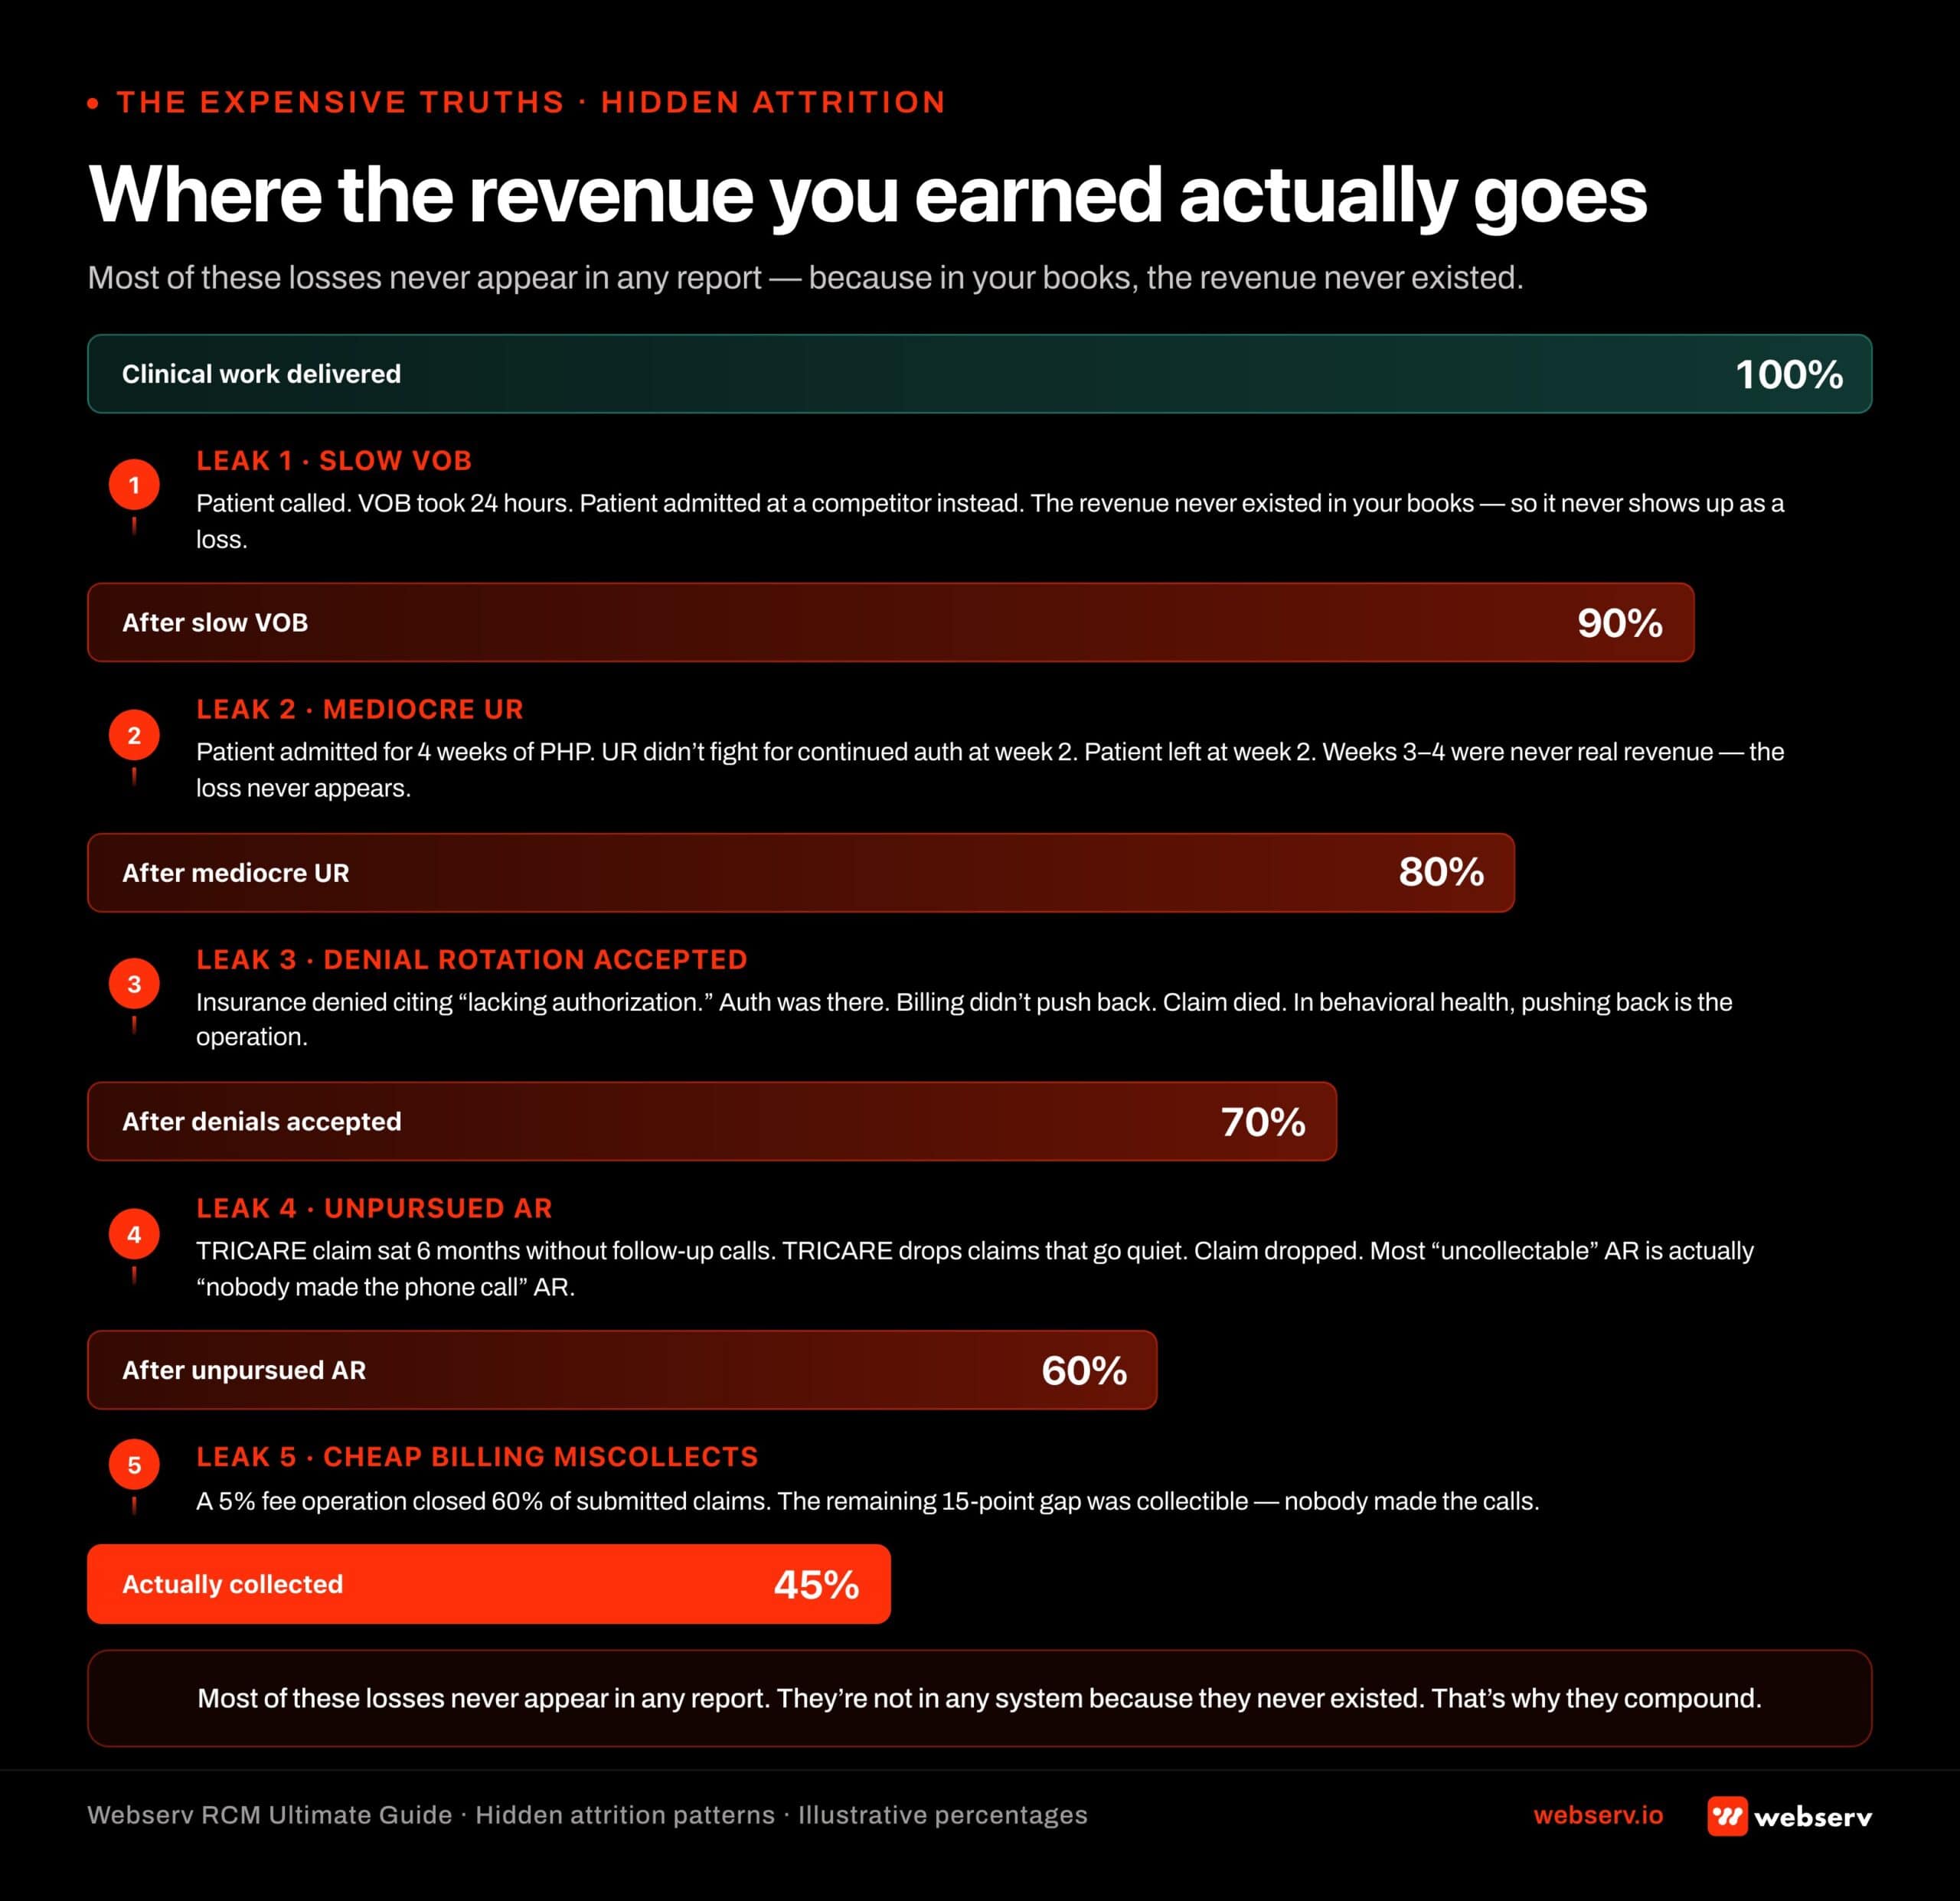 Infographic titled ‘Where the revenue you earned actually goes’.
Staff turnover in in-house billing is brutal. The people who actually know how to do this work well generally own their own shop. They don’t work for someone else. If you hire a good in-house biller, there’s constant risk they leave to start their own thing.
When they do, you’re rebuilding institutional knowledge from scratch.
The opportunity cost of running billing in-house is the opportunity cost of running it badly. A CEO spending the week learning how to negotiate with UnitedHealthcare isn’t spending that week learning how to bring in more patients, improve clinical outcomes, or scale the things that actually grow the business.
Billing is a problem that’s been solved. You don’t need to solve it again from scratch on your own balance sheet.
Hidden attrition doesn’t show up in reports. If your VOB comes back too slow and the patient admits somewhere else, that’s lost revenue, but it’s not in any report. It never existed.
If your UR is mediocre and patients leave PHP after two weeks instead of four, that’s also lost revenue that won’t show up in a report. Those weeks three and four were never billed. The revenue was never real, so it can never show up as a loss. But it’s the difference between a center growing and a center stagnating, and most operators never see it.
Paying less often means collecting less. The 5% billing company often collects 75% of what a 10% billing company would collect. You save five points on collections and lose fifteen points on revenue.
Math is math.
If your VOBs come back too slow, patients don’t admit. That’s lost revenue. If your URs aren’t good and you’re not getting long lengths of stay, that costs money too. It’s money you’ll never see. Hidden attrition. It’s not in a report. It’s not anywhere, because it never existed.
Kyle McHenry, Founder of Revenue Logic
What to listen for (and what to watch for) in an RCM partner
A good RCM partner has substance abuse billing companies. A bad one has tells.
Weekly client calls, not monthly or quarterly. If your billing company isn’t reviewing VOBs, UR, claim submission, payment posting, denials, and credentialing with you weekly, they aren’t operationally integrated with your business. They’re a vendor processing paperwork.
We run weekly calls with every new client for at least the first year, reducing cadence only when the client’s own team has enough fluency to review the data independently.
Real-time dashboards, not monthly summaries. You should be able to log in and see open claims by patient, denial reasons, likely reimbursements and timing, aging buckets.
If your billing company only sends you monthly PDFs, you don’t actually know what’s happening with your revenue cycle.
You know what happened a month ago.
They tell you what to do, not the other way around. This is the opinion I’ll push back on the billing industry about the hardest: a good billing company is not a yes-man.
- They should be telling you to stop billing drug tests a certain way if it’s going to trigger an audit.
- They should be telling you not to take out-of-state exchange policies in significant volumes.
- They should be telling you not to do rapid readmissions of the same patients.
- They should be telling you not to bill outpatient therapy on top of PHP and IOP.
Sometimes the billing company’s advice will conflict with what your state certifying body says. The state might require you to document detox every three hours. The insurance company wants documentation every four hours.
You have to listen to the insurance company. The state isn’t paying your bills.
They integrate with the behavioral health EMR ecosystem. Most of our clients run on Kipu. We work across Kipu, Alleva, Navix, BestNotes, and Sunwave. Kipu is the closest thing to a standard in behavioral health. If a billing operation can only work with one EMR, that’s a flag.
Red flags
- Outsourced UR to foreign countries (irreparable relationship damage with insurance companies over time)
- Refuses to show you claim-level data on a dashboard
- Can’t explain their denial appeal process
- Doesn’t track or share metrics on clean claim rate, DIAR, or collection rate
- Quotes a single “typical reimbursement” number for a payer instead of segmenting by policy type
- Accepts denials without fighting them as a matter of routine
- Has ever been vague about what’s in the chart when a care manager asks
The math of why this actually matters
Let me end on a piece of arithmetic.
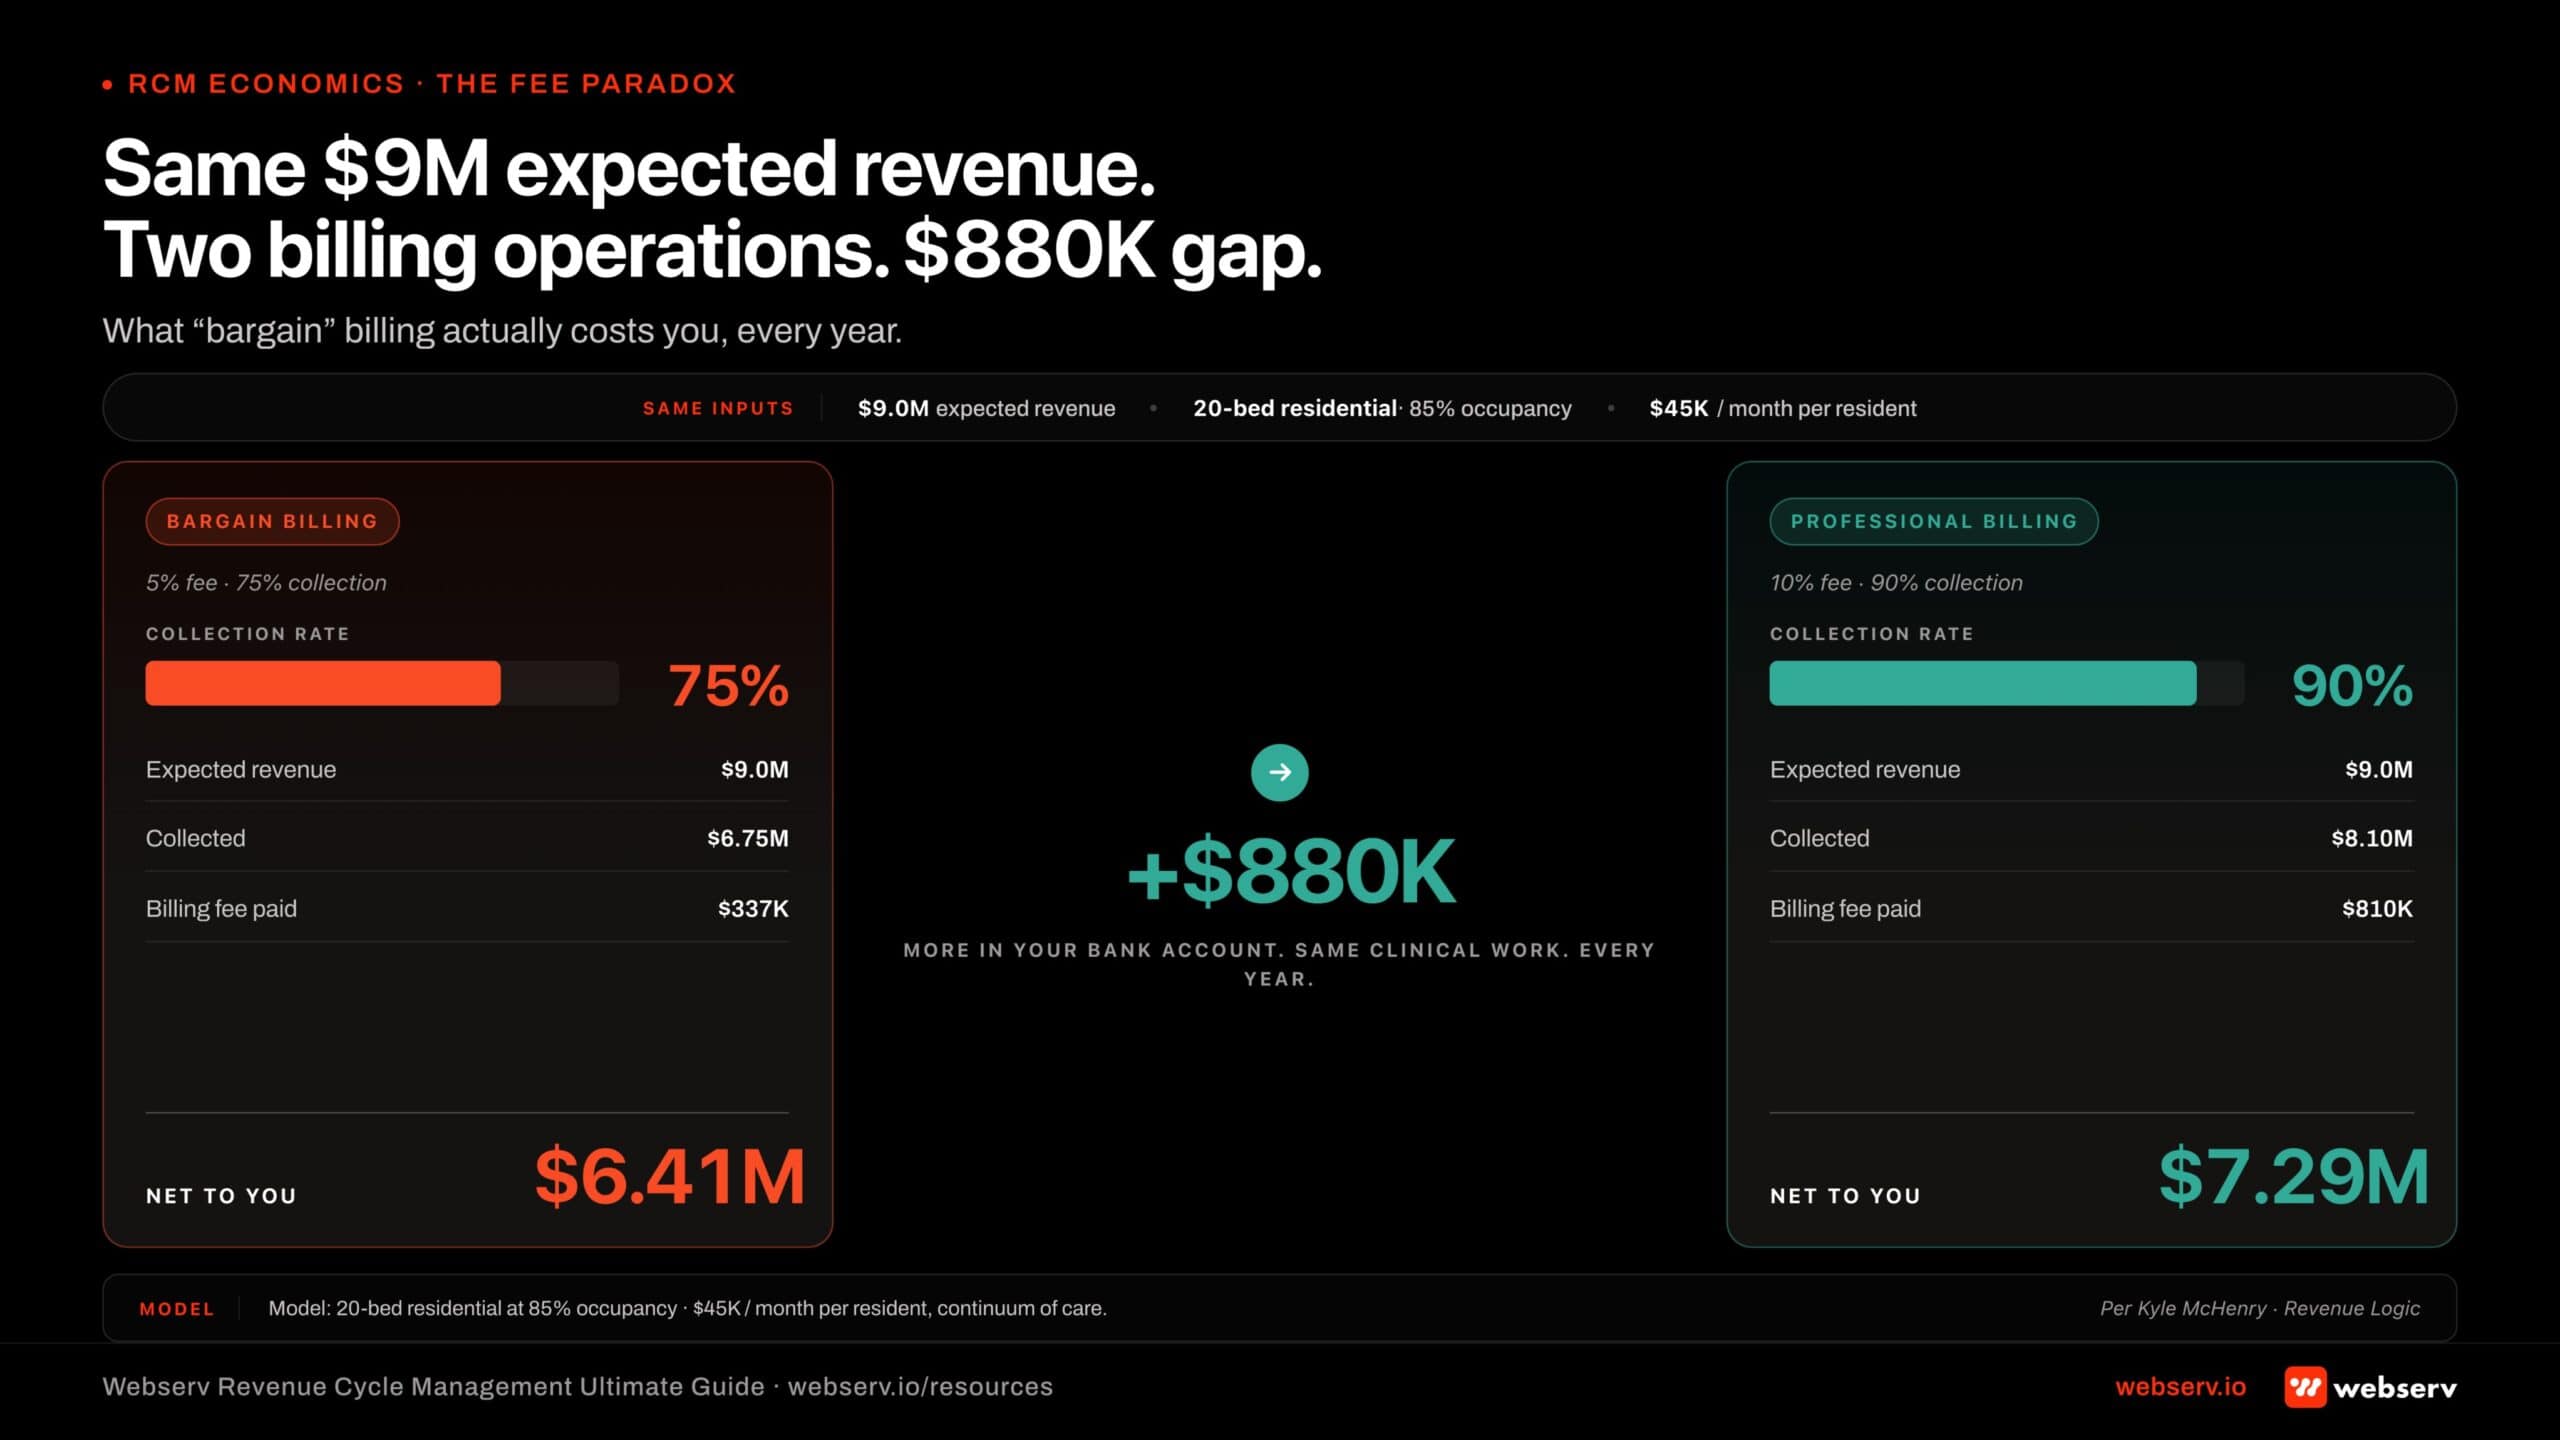 Infographic titled ‘Same $9M expected revenue. Two billing operations. $900K gap.’
Say your treatment center runs 20 residential beds at 85% occupancy on a mix of commercial policies averaging $45,000 per residential month including continuum of care. At that scale, you’re doing about $9M in expected annual net revenue.
A billing operation at 75% collections versus 90% collections is a 15-point difference. On $9M in expected revenue, that’s $1.35M. Every year that money is sitting somewhere between the insurance company’s ledger and yours.
Cash that could have paid salaries, reduced your cost per admission, funded clinical improvements, funded marketing. Money you earned clinically and lost operationally. Our complete guide to behavioral health marketing covers how marketing and admissions feed that revenue.
The billing company charging you 5% will cost you about $450K a year on that revenue. The billing company charging you 10% will cost you $900K, assuming they actually collect at 90%. Net of fees, the 10% operation puts an additional $900K in your bank account every year compared to the 5% one. Every year. On the same clinical work.
People don’t work for free. If your billing company is charging a rate that seems too good to be true, what you’re getting is a rate that matches. You’ll save five points on the bill and lose fifteen points on the revenue.
RCM is where treatment center growth actually compounds.
Not in clinical outcomes: those get you licensed.
Not in marketing: that fills the funnel.
In billing, where the revenue your clinical team and your marketing team have already earned either arrives or doesn’t.
Book an intro call if you want to see what your billing operation is actually producing and what it should be producing. We’ll review your current collection rate, denial patterns, and AR aging, and return a prioritized fix list before you change a single thing about your operation.
Frequently asked questions about behavioral health revenue cycle management
Should treatment centers keep billing in-house or outsource RCM?
Most facilities under 30 beds outsource billing because the volume does not justify a full in-house team. Most facilities over 50 beds benefit from a hybrid model where VOB and UR are in-house but claims submission and AR follow-up are outsourced. The boundary in between depends on payer mix and complexity.
The honest answer is whichever model produces better net collections per admit at the lowest risk. We have seen 25-bed programs run brilliant in-house operations and 75-bed programs lose money on outsourced billing. The headcount question matters less than the discipline and the visibility you have into what is being collected and what is being written off.
If your current operation cannot tell you the denial overturn rate per payer in under a minute, the model is broken regardless of whether the work is in-house or outsourced. That is the test to run before deciding which structure to keep.
How long should it take to see results from an RCM overhaul?
Most treatment centers see operational improvements within 60 days of fixing core workflow issues (VOB turnaround, claim submission timing, denial follow-up cadence). Deeper revenue improvements (DSO compression, payer-specific rate recovery, write-off reduction) typically take 4 to 6 months as the changes compound through aging AR.
The fastest wins usually come from fixing the most expensive single-process leak first. A 15 percent reduction in denial rate or a 5-day DSO compression can each move 7-figures of revenue annually depending on facility size. We start with the highest-dollar lever.
An overhaul that takes longer than 90 days to show measurable lift is usually a sign the diagnosis was wrong. Either the gap is somewhere other than where you started, or the partner is not actually executing the changes they committed to.
How does marketing spend connect to RCM performance?
Marketing spend produces admits. RCM determines what percentage of each admit becomes collected revenue. If RCM is broken, every marketing dollar is multiplied by a number less than one. Most treatment centers measuring marketing ROI miss this because they look at marketing-to-admit attribution without looking at admit-to-cash attribution.
The math compounds. A facility spending $100K monthly on marketing at a $5K cost-per-admit produces 20 admits. If RCM is collecting 70 cents on the dollar versus 90 cents, the difference is six figures of monthly lost revenue against the same marketing investment.
We build reporting that ties marketing channel attribution all the way through to collected cash. When that line of sight is clean, marketing decisions get more conservative or more aggressive on the right channels and the budget allocation actually reflects what produces revenue.
Does in-network versus out-of-network status change RCM strategy?
Yes, significantly. In-network programs have predictable per-diem reimbursement, faster claim cycles, and lower denial rates, but lower revenue per admit. Out-of-network programs have higher revenue per admit, but longer claim cycles, more single-case agreement work, and higher exposure to underpayment and recoupment risk.
OON-heavy programs need stronger UR discipline, contracted SCA workflows, and aggressive denial follow-up. INN programs benefit more from coding accuracy, contract rate auditing, and submission-cycle discipline. The same RCM team running both books needs different daily workflows for each.
Hybrid programs that take both INN and OON admissions tend to underinvest in the OON workflow because the INN side feels easier to manage. That gap is where most hybrid programs lose revenue without realizing it.
When does it make sense to switch RCM partners?
The three clearest signals are persistent DSO above 50 days, denial overturn rates below 40 percent on appeal, and inability to produce payer-specific underpayment data on demand. Any one of those is a reason to evaluate. All three together are a reason to switch.
The switch itself carries risk. Aging AR can stall during transition, in-flight authorizations need careful handoff, and payer relationships can lapse if billing addresses change without notice. Most botched switches lose 60 to 90 days of cash velocity before the new partner stabilizes.
The decision should be made on net collected revenue per admit, not on switching cost. A 5 percent improvement in net collections at most facilities pays back the transition cost inside one quarter.
Most in-house teams hit a wall not because they lack knowledge, but because they lack bandwidth.
When you are ready to hand it off, Webserv has spent 9 years executing exactly this for treatment centers nationwide.