Referral partner marketing is the specific admissions channel that operates outside the digital marketing programs most treatment center marketing teams manage. It sits inside our admission ops capability alongside intake, eligibility, and billing.
Referral partners include therapists, physicians, EAPs, courts, unions, prior alumni, family recovery groups, and other professional or peer sources that send admissions to specific facilities based on relationship rather than paid or organic marketing.
For many treatment centers, referral partner admissions are a significant share of total admits, and they often convert better than paid-driven inquiries because referral partners send people who have already been screened for treatment need.
The admission ops team at most facilities manages referral partner relationships as a separate discipline from digital marketing. The pattern I see across facility referral programs: the referral relationships exist and produce steady admit volume, but the referral partner marketing infrastructure that would scale the program does not.
Facilities operate with referral partner spreadsheets that get updated inconsistently, referral partner communication that happens ad hoc rather than on cadence, and referral partner attribution that resolves at the admit level but not at the relationship level.
The opportunity most facilities miss: a well-managed referral partner program can become one of the lowest cost-per-admit channels the facility has. Portfolio operators that coordinate referral programs across facilities can compound that advantage.
Neither number materializes without the specific infrastructure that separates well-managed referral programs from ad hoc referral relationships.
This piece walks the referral partner marketing playbook for treatment centers. The specific referral partner categories that produce most treatment center admits, the CRM infrastructure that manages relationships at scale, and the content and communication cadence that keeps partners active.
It also covers the attribution setup that resolves referral partner performance at relationship level, the compliance considerations that apply to referral arrangements, and the measurement patterns that separate genuinely valuable partners from low-return relationships. For the broader picture, see our ultimate guide to behavioral health marketing.. Related reading: Salesforce for treatment center admissions. and pairs with our attribution guide and pre-admission eligibility guide.
Key Takeaways
- Referral partner marketing is a significant admit source at many treatment centers, and referral traffic often converts better than paid traffic because it arrives pre-qualified. Well-managed referral programs become a durable, predictable admit source.
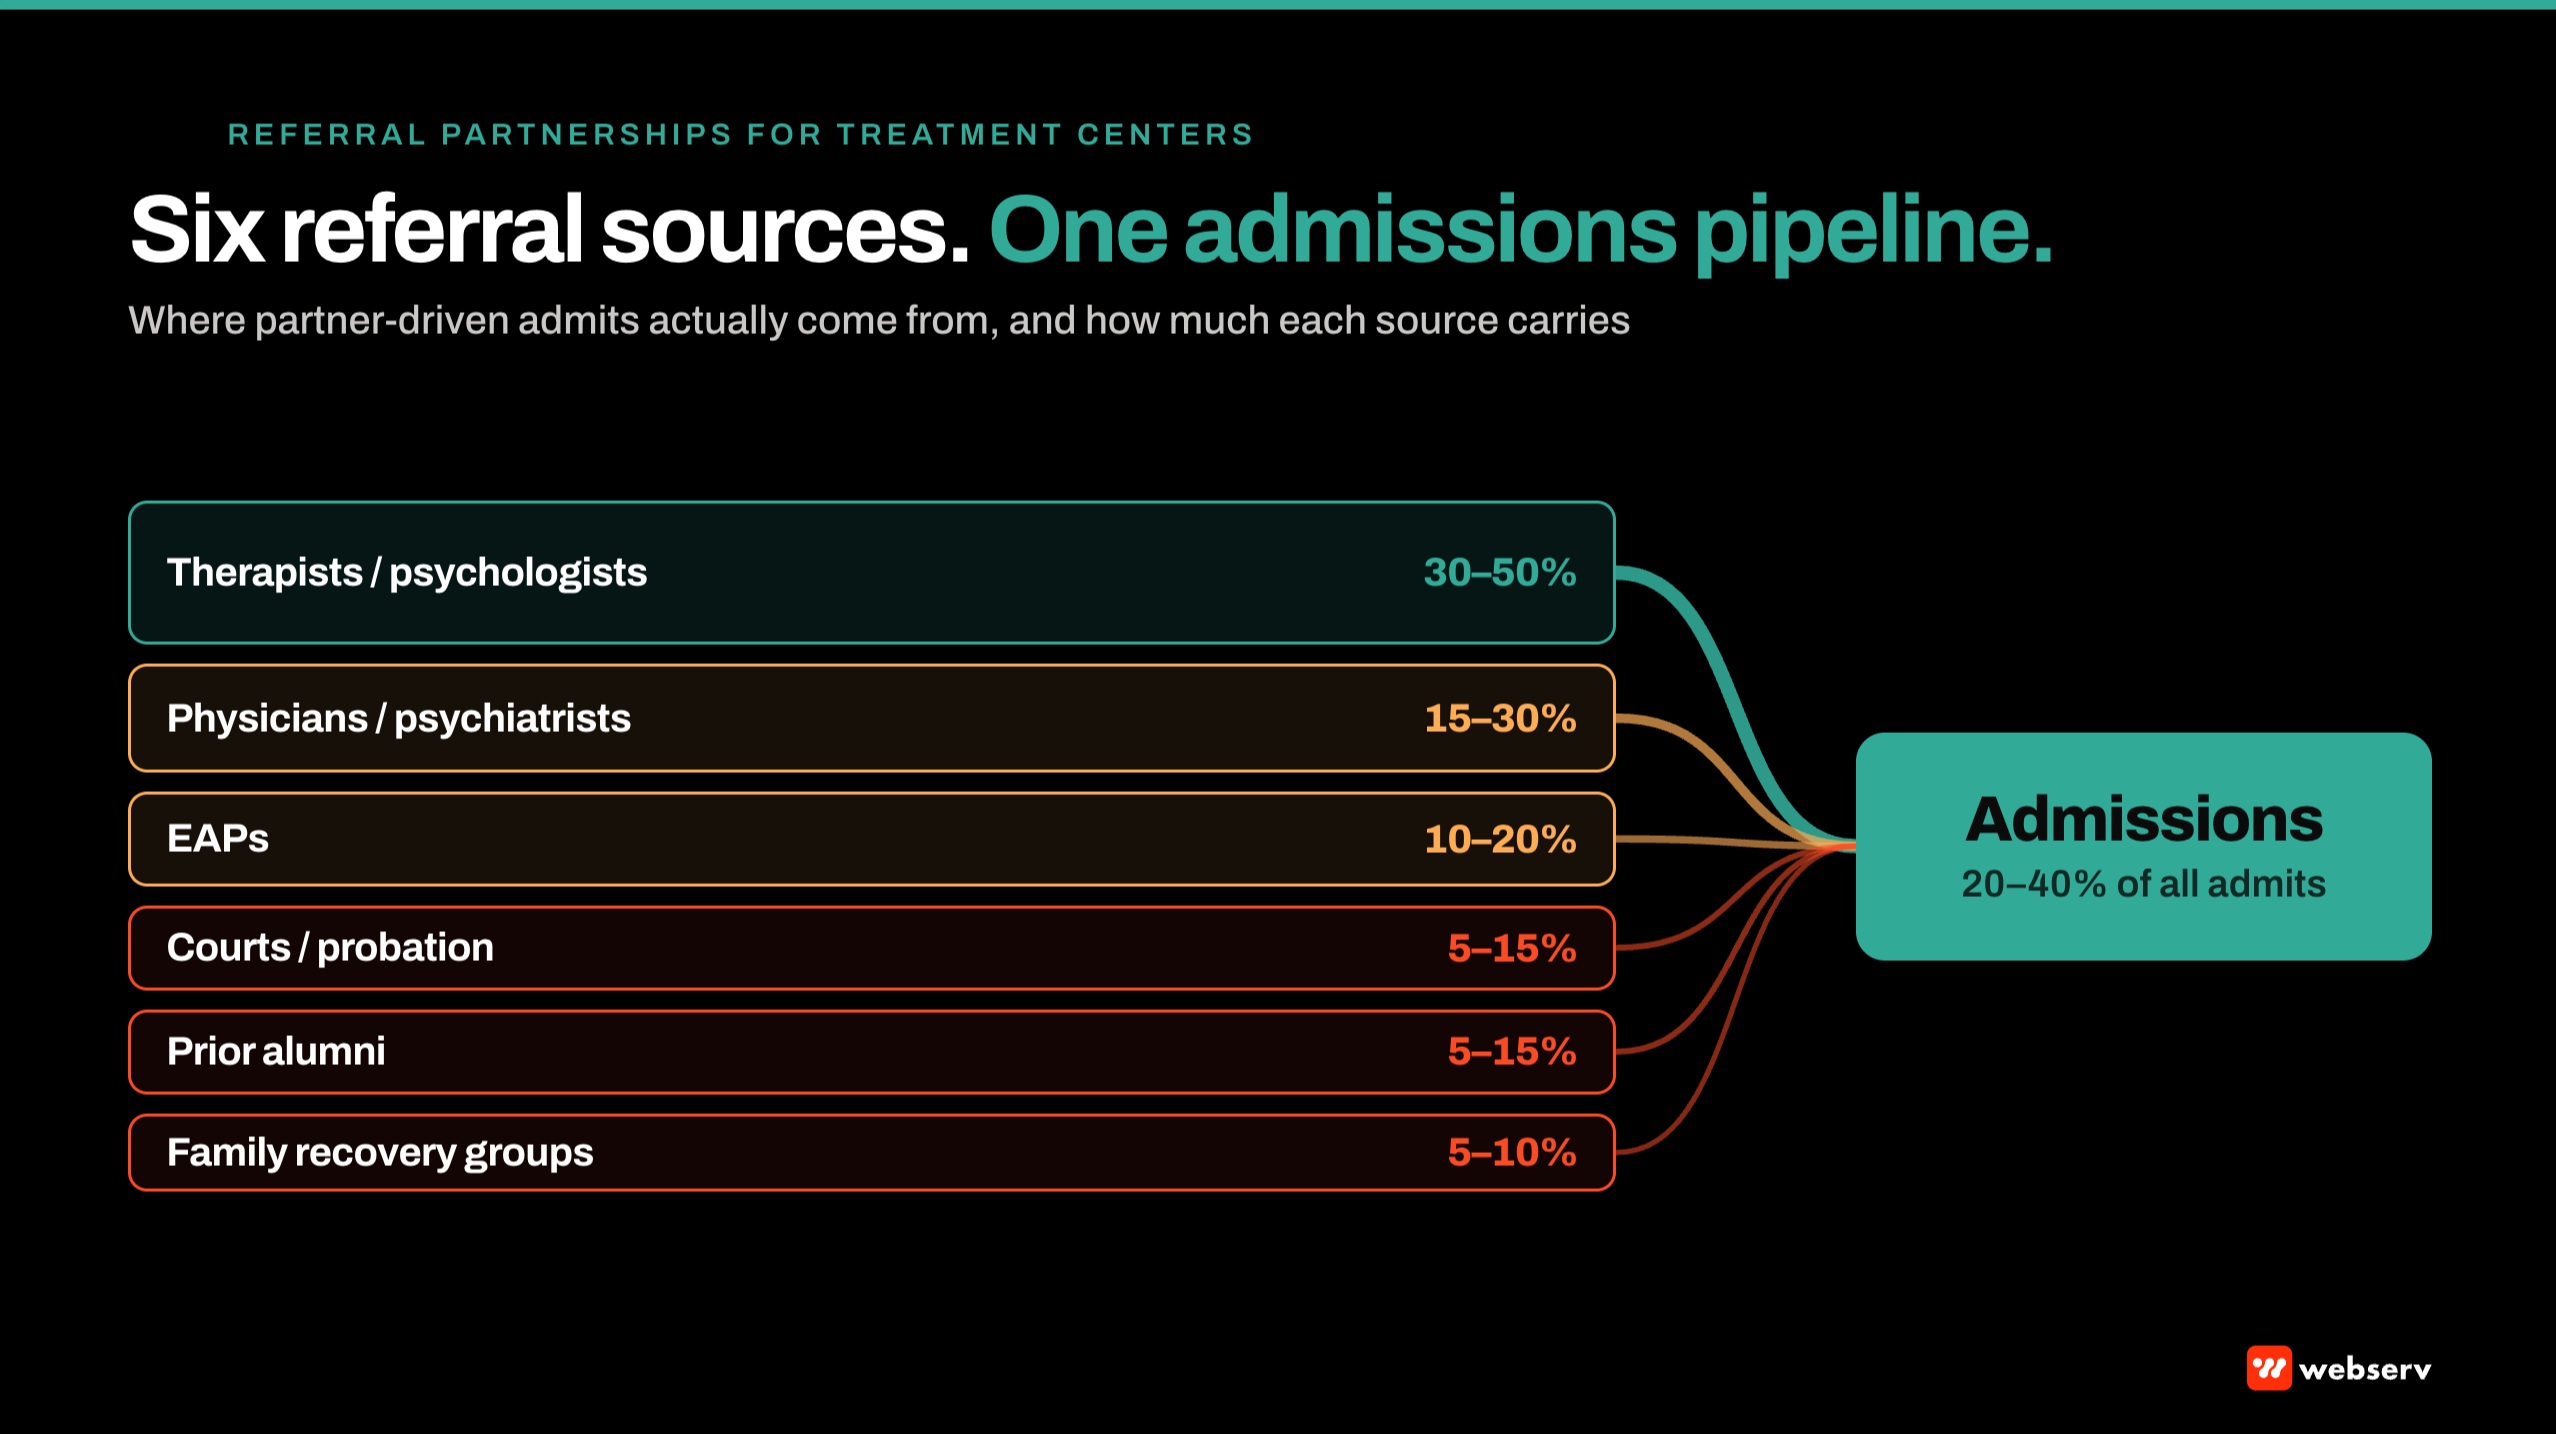
- Referral partner categories that produce most treatment center admits: therapists and psychologists, physicians and psychiatrists, employee assistance programs, courts and probation, prior alumni, and family recovery groups. The mix varies by facility, so measure your own.
- CRM infrastructure that scales referral partner management: dedicated referral partner records with contact history, referral history, and communication cadence tracking. Salesforce Health Cloud, KIPU, BestNotes, and Sunwave all support referral partner CRM patterns with facility-specific customization.
- Content and communication cadence that keeps referral partners active: monthly outreach (email or phone), quarterly in-person or video meetings with priority partners, semi-annual educational content specifically for referral partners, and event-based communication (facility updates, program launches, clinical team changes).
- Compliance considerations: no incentive-based referral arrangements (violation of federal Anti-Kickback Statute for Medicare/Medicaid patients and state-level laws for commercial patients). Referral partner arrangements based on clinical fit and outcomes rather than financial incentives.
DEFINITION
Referral partner marketing for treatment centers. The non-digital admissions channel that develops and manages professional and peer referral relationships (therapists, physicians, EAPs, courts, prior alumni, family recovery groups) as a coordinated program with CRM infrastructure, monthly and quarterly communication cadence, relationship-level attribution, and anti-kickback-compliant arrangement structure. A significant admit source at many treatment centers, often converting better than paid channels.
Distinct from digital marketing programs (paid, organic, direct all resolve through session and click attribution), distinct from admissions operations at the intake level (which handles the specific admit workflow after the referral arrives), and distinct from clinical case coordination (which manages the clinical handoff separately from the marketing relationship). Our guide to referral partner attribution shows how to measure what each partner sends.
OPERATOR INSIGHT
The referral relationships exist and produce steady admit volume, but the referral partner marketing infrastructure that would scale the program does not.
Facilities operate with referral partner spreadsheets that get updated inconsistently, referral partner communication that happens ad hoc rather than on cadence, and referral partner attribution that resolves at the admit level but not at the relationship level. A well-managed referral program can become one of the lowest cost-per-admit channels a facility has, but not without the specific infrastructure below. The partner-side outreach is covered in referral marketing for behavioral health.
Referral partner categories that produce most treatment center admits
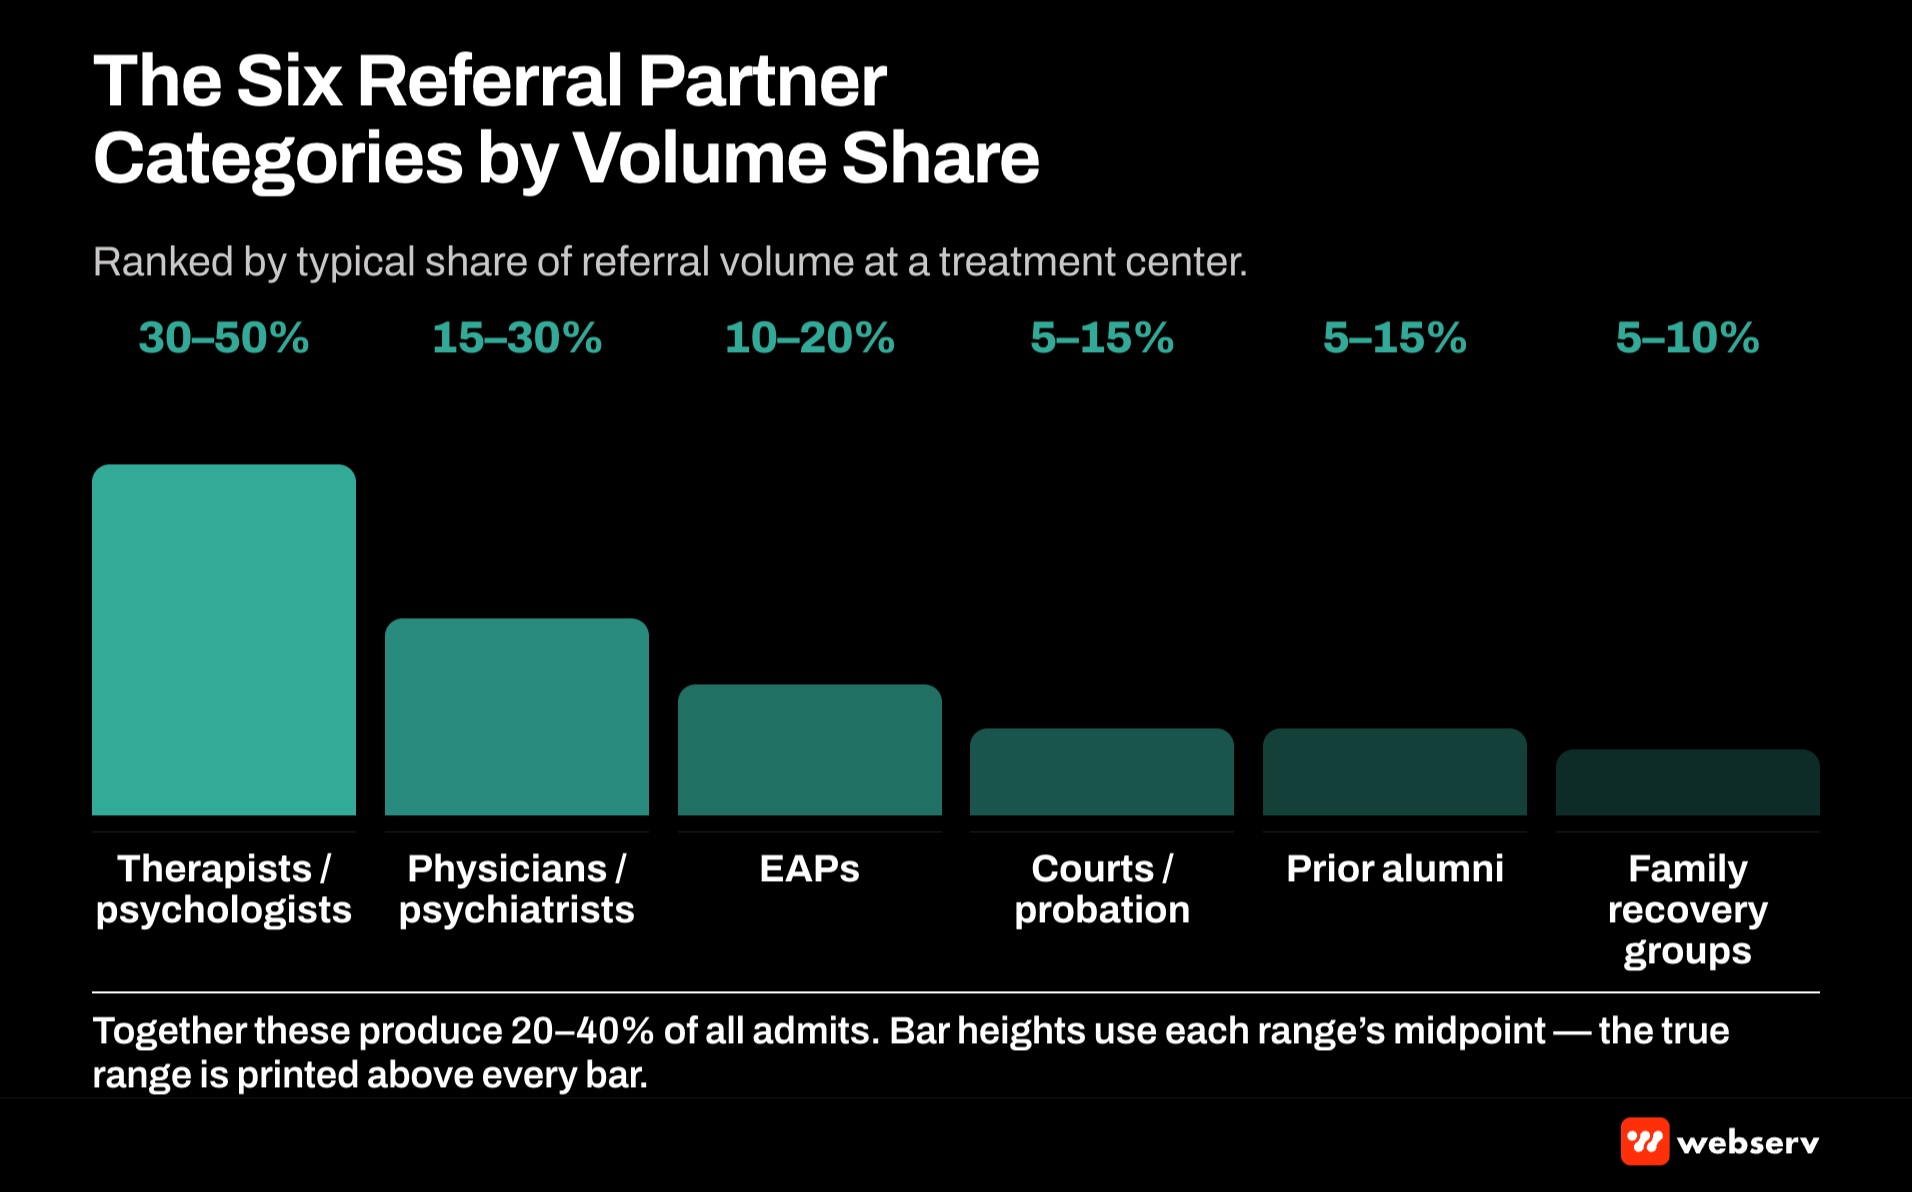
Six referral partner categories produce most treatment center admits. Understanding the category mix helps focus referral program investment.
Therapists and psychologists
Often the largest referral category. Community therapists, private practice psychologists, and outpatient BH providers refer patients requiring higher level of care than their outpatient practice supports.
The specific relationship pattern: ongoing clinical relationships built through professional interaction, clinical fit alignment, and outcome feedback loops. Therapists refer to facilities they trust to send patients back at appropriate step-down.
Physicians and psychiatrists
A major referral category. Primary care physicians, psychiatrists, addiction medicine physicians, and hospital discharge planners refer patients meeting BH admission criteria.
The specific relationship pattern: professional education about facility programs, clinical case coordination, and admissions workflow alignment with physician practice patterns.
Employee assistance programs (EAPs)
A meaningful, contract-driven referral category. Corporate EAPs contract with treatment centers for employee referrals. Contract-based referral relationships with specific eligibility and coverage terms.
Courts and probation
A smaller but steady referral category. Court-ordered treatment referrals typically produce lower per-admit revenue but higher volume when the facility is on the court’s referral list.
Prior alumni
A smaller but steady referral category. Alumni who complete treatment refer friends and family members. Alumni referral programs formalize this pattern with alumni association infrastructure.
Family recovery groups
A smaller referral category. Al-Anon, Nar-Anon, and other family recovery communities refer family members to treatment when their loved one needs professional support.
The referral partner program at a glance
Pre-qualified
Referral admits arrive already screened for treatment need
6
Partner categories: therapists, physicians, EAPs, courts, alumni, family groups
Concentrated
A small group of partners usually drives most referral admits
Long build
Referral programs take a long time to reach stable volume
CRM infrastructure for referral partner management
The CRM infrastructure that scales referral partner management: dedicated referral partner records with contact history, referral history, communication cadence tracking, and relationship-level attribution.
Referral partner record fields. Contact name, organization, professional credentials, contact information (phone, email, mailing address), specialty area, geographic service area, relationship start date, primary internal relationship owner at the facility, and communication cadence preferences.
Referral history tracking. Every referral from the partner logged in the CRM with referral date, patient identifier (with appropriate PHI-adjacent handling), admission outcome (admitted, not admitted, admitted elsewhere), and treatment outcome (completed, transferred, discharged).
Referral history feeds the relationship-level attribution that resolves which partners produce which admit outcomes over time.
Communication cadence tracking. Every communication with the partner logged in the CRM with communication type (email, phone, in-person, video meeting), date, participants, topics discussed, and next action.
The specific pattern: cadence tracking triggers the next outreach action based on the specific relationship type and historical cadence pattern.
Platform options. Salesforce Health Cloud, KIPU, BestNotes, and Sunwave all support referral partner CRM patterns. Facilities without specialized BH CRM sometimes manage referral partners in general CRM (HubSpot, Salesforce Sales Cloud) with custom object configuration.
The specific consideration: referral partner records should live in the same CRM as the admissions records so referral attribution can resolve from partner to admit to reimbursement.
Content and communication cadence
The specific communication cadence that keeps referral partners active without over-communicating.

Monthly outreach. Email or phone communication with all active referral partners on monthly cadence. Content: facility updates, program news, admissions team availability, referral appreciation.
Quarterly in-person or video meetings. Higher-touch meetings with priority partners (top 20 percent of referral partners by referral volume or referral quality). Meeting content: strategic relationship discussion, case coordination, program updates.
Semi-annual educational content. Longer-form content specifically for referral partners. Content: clinical program deep dives, admissions workflow updates, outcome data summaries, family support resources.
Event-based communication. Ad hoc communication triggered by specific facility events. Content: new program launches, clinical team changes, facility expansions, accreditation updates.
Alumni-referred outreach. Additional communication cadence specifically for alumni-referred admits. Recognition of the referring alumni, updates on the referred patient’s progress (with appropriate consent), and alumni community engagement.
DO
- Manage referral partners inside the same CRM as admissions , attribution has to resolve from partner to admit to reimbursement in one chain.
- Log every referral with date, patient identifier (with PHI-adjacent handling), admission outcome, and treatment outcome; that history is the relationship-level attribution.
- Run a monthly outreach cadence with all active partners plus quarterly meetings with the small group that produces most of the referral volume.
- Structure any compensated arrangement (bona fide employment, fair-market-value professional services) through healthcare compliance counsel , never per-referral cash.
- Tier partners by volume, admit rate, and average per-admit revenue; reallocate relationship investment toward the highest-return tier every 12 months.
DON’T
- Pay cash or in-kind bonuses for referrals of Medicare, Medicaid, or (in most states) commercially insured patients , federal Anti-Kickback Statute and state patient-brokering laws.
- Run referral partners on a spreadsheet outside the admissions CRM , attribution and cadence tracking both break.
- Lump referral admits into “direct” or “other” source attribution , the program contribution disappears from the reporting.
- Expect meaningful referral volume in the first few months, because the build cycle is long and early performance is misleading.
- Confirm a specific patient’s status when communicating with the referring partner beyond the consent the patient has signed , clinical case coordination has HIPAA guardrails.
Attribution setup for referral partner performance
Attribution for referral partners resolves at relationship level rather than at session level. The specific attribution setup.
Referral partner assignment at intake. Every admission inquiry captures the specific referral partner if any at the intake stage. Referral partner assignment is a structured field in the CRM rather than free-text notes.
Relationship-level attribution. Referral volume, admit rate, and average per-admit revenue tracked per referral partner over time. Enables comparison of referral partner performance to focus program investment on highest-return relationships.
Multi-touch attribution for referrals. Some admits involve multiple referral sources (therapist referral plus family recommendation plus prior alumni influence). Multi-touch attribution resolves the specific contribution of each source.
Referral partner LTV. Long-term value calculation per referral partner. Some partners produce steady low-volume referrals over years. Others produce burst referrals then stop. Understanding the LTV pattern helps decide where to invest ongoing relationship development.
Compliance considerations for referral partner arrangements
Referral partner arrangements carry specific compliance considerations that apply differently than digital marketing arrangements.
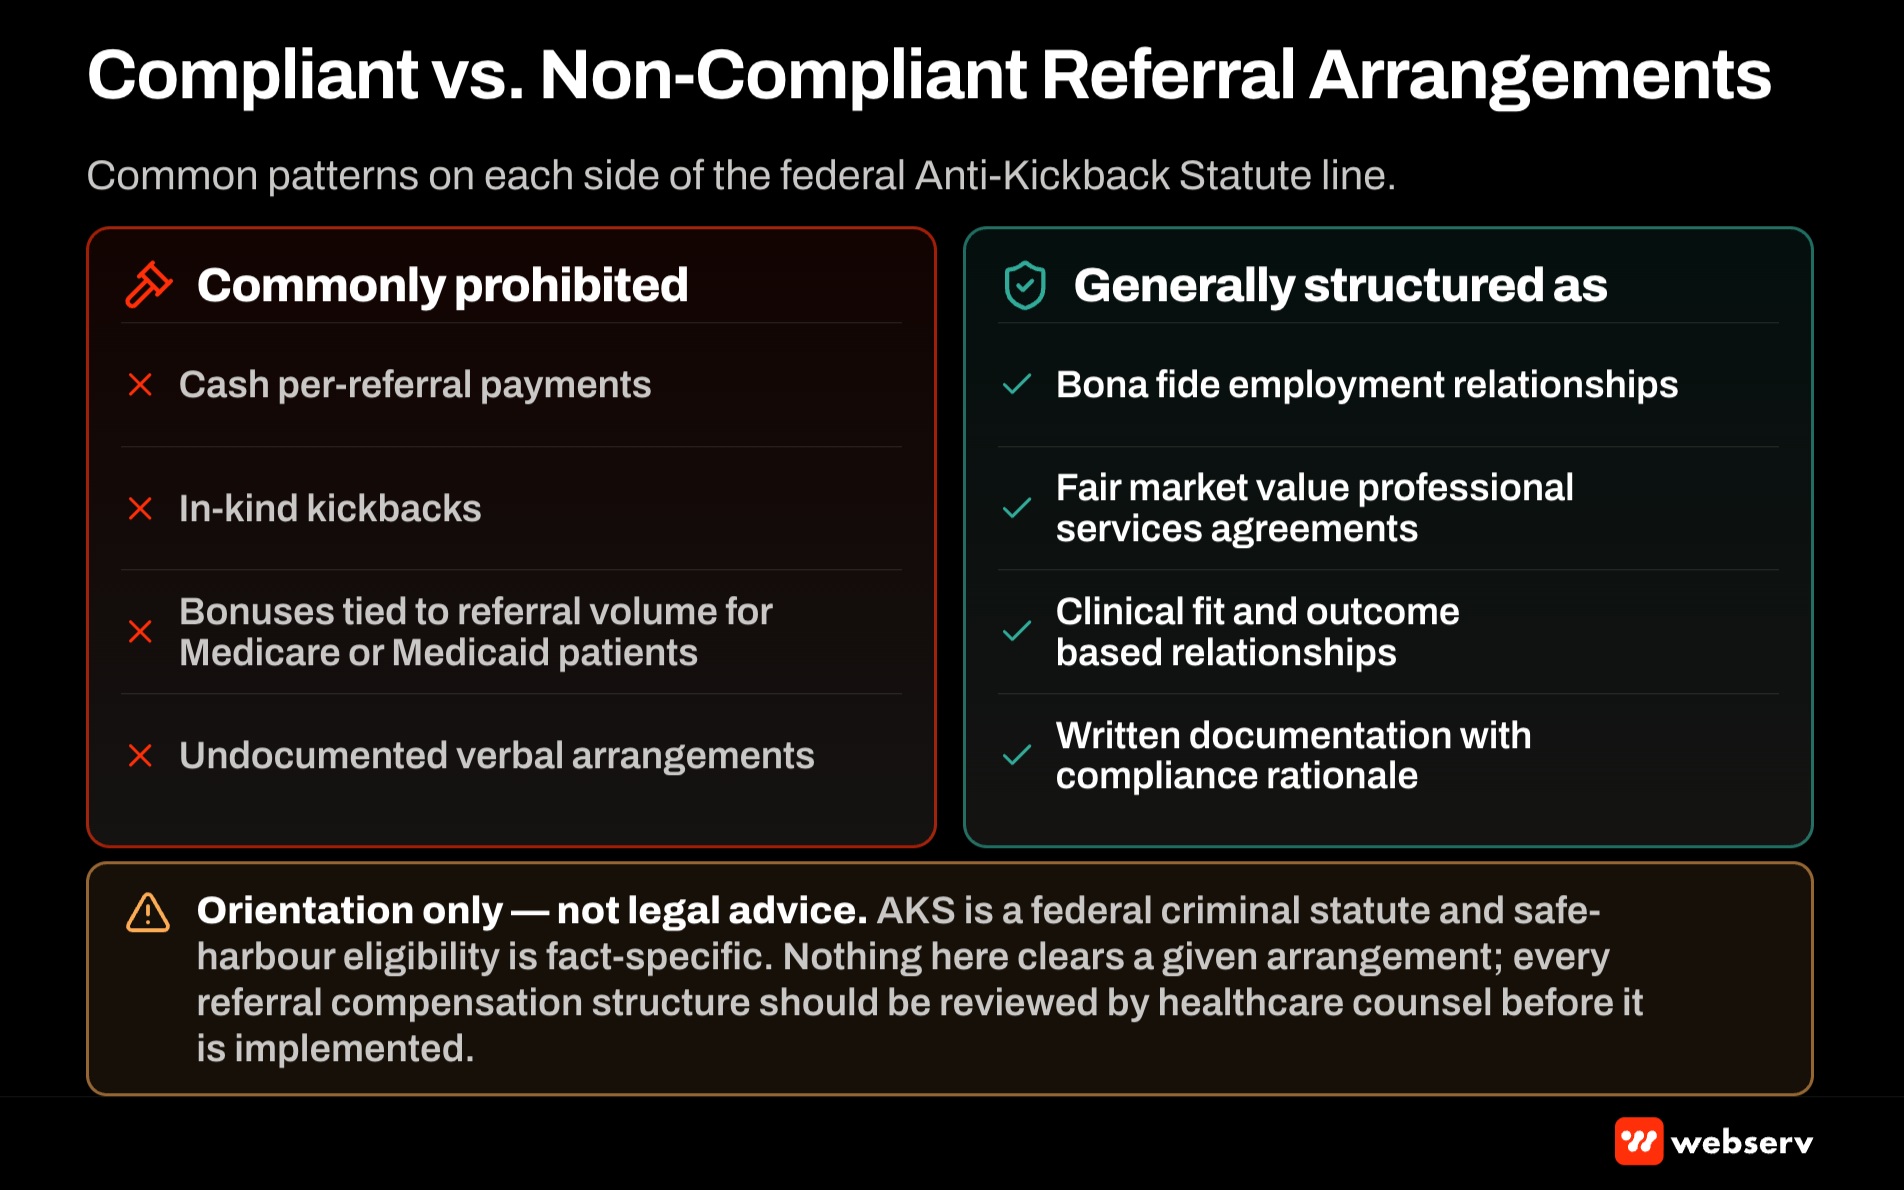
Federal Anti-Kickback Statute. Prohibits paying for referrals of Medicare and Medicaid patients. Applies to all treatment center referral arrangements where Medicare or Medicaid patients might be referred.
The specific prohibition: no cash payments, no in-kind payments, no bonuses tied to referral volume for Medicare/Medicaid patient referrals. Also prohibits any arrangement that could be construed as compensation for referrals.
State-level laws. Many states extend anti-kickback restrictions to commercial insurance patients. California, Florida, Texas, and other states have enacted state-specific patient brokering and referral fee prohibitions.
Safe harbors and exceptions. Federal and state laws provide safe harbors for specific referral arrangements. Bona fide employment relationships, fair market value professional services agreements, and personal services agreements all have specific safe harbor requirements.
Facilities operating close to safe harbor boundaries should work with healthcare compliance counsel to structure arrangements that fit within specific exceptions.
Documentation standards. Referral partner arrangements documented in writing with specific terms, compensation structure (if any), and compliance rationale. Verbal or undocumented arrangements produce higher enforcement risk.
The specific pattern that works: clinical fit and outcome-based referral relationships without financial incentives. Facilities that build strong clinical programs and communicate program strengths to referral partners produce steady referral volume without triggering compliance risk.
Measurement patterns for referral programs
The measurement patterns that separate genuinely valuable partners from low-return relationships.
Referral volume tier. Partners tiered by annual referral volume. A small share of partners typically produces most referral admits. Ongoing relationship investment focused on top tier.
Referral admit rate. Percentage of referrals from each partner that convert to admits. Higher admit rates typically indicate better clinical fit and better referral pre-qualification.
Referral admit revenue. Average per-admit revenue by referral partner. Some partners refer higher-payer-mix admits than others. Revenue-weighted measurement reveals the highest-value relationships.
Referral partner satisfaction. Periodic survey or feedback capture from referral partners about the facility’s admissions responsiveness, clinical coordination, and outcome communication. Satisfaction feedback identifies relationship risks before they produce referral volume declines.
Frequently Asked Questions
How much should we spend on referral partner marketing?
Cost depends mainly on program maturity, geographic scope, and how many relationship managers the program needs.
The cost splits across relationship management staff (the largest line), the CRM platform, content and communication production, and event or meeting hosting.
Portfolio operators produce economies of scale because relationship management can serve multiple facilities and the CRM platform amortizes across the portfolio. Per-facility cost typically drops for the second and subsequent facilities.
How do we know if a referral partner relationship is worth continuing?
Three measurement signals. First: annual referral volume above the threshold your facility sets for a relationship to justify ongoing investment.
Second: a referral admit rate that holds up against your facility average. Third: referral admit average revenue at or above facility-wide admit average. Relationships that consistently produce below-average admit revenue may reflect payer mix or clinical fit issues.
Partners failing all three signals over a sustained period typically get reclassified from active to inactive status.
How do we handle referral partners in the digital marketing attribution setup?
Distinct attribution source in the digital marketing measurement. Referral partner admits track separately from paid channel admits, organic search admits, and direct traffic admits.
The specific integration: referral partner assignment at intake feeds the source attribution field in the CRM. Downstream attribution reports segment referral admits from all other sources. Our attribution guide walks the five-layer chain referral admits plug into.
Facilities that lump referral admits into “direct” or “other” attribution typically underattribute the referral program contribution to overall admissions economics.
Can we pay for referrals through legitimate arrangements?
Case-by-case depending on the specific arrangement structure. Bona fide employment relationships (hiring a former community therapist as an internal admissions or outreach team member) are typically compliant.
Fair market value professional services agreements (paying a psychiatrist for consulting hours at market rate) are typically compliant if the services are actually delivered and the compensation reflects fair market value. Straight per-referral payment arrangements typically violate anti-kickback laws for any patient population that could include Medicare/Medicaid coverage. State laws extend prohibitions to commercial patients in many jurisdictions.
The right pattern: work with healthcare compliance counsel to structure any compensated referral partner relationship. Facilities that assume compliance without counsel review typically produce higher enforcement risk.
How does referral partner marketing interact with our digital marketing programs?
Complementary but distinct. Digital marketing produces admits from paid campaigns, organic search, and direct traffic. Referral marketing produces admits from professional and peer relationships.
The specific interaction: referral partners see facility marketing content (organic search, paid campaigns, thought leadership content) and factor it into their referral decisions. Facilities with strong digital presence typically produce higher referral partner conversion because the referring professional can see the facility’s positioning.
Facilities that invest in digital marketing without referral marketing leave a meaningful share of potential admits on the table. Facilities that invest in referral marketing without digital marketing typically produce weaker overall market presence and lower referral partner conversion.
How long does it take to build a productive referral partner program?
Plan in years, not months, for meaningful referral program impact. The early period typically produces limited referral volume as relationships build.
Volume then accelerates as initial relationships mature and additional relationships develop. Mature programs then stabilize at facility-appropriate volume levels.
Facilities expecting faster returns from referral programs typically produce misleading conclusions about early performance. The right expectation: referral programs are infrastructure investments with multi-year build cycles.
How does referral partner marketing integrate with our overall admissions program?
As a specific channel inside the broader admissions program alongside digital marketing channels. The admissions team handles inbound admissions inquiries from all sources (paid, organic, direct, referral) through the same intake workflow.
The specific integration point: referral partner assignment at intake feeds the source attribution field so downstream measurement can segment referral admits from other sources. Referral partner-specific communication continues after admit through case coordination with the referring partner. Our pre-admission eligibility playbook and VOB vs pre-authorization guide cover the intake-side workflow referrals flow through.
Facilities that treat referral partners as a separate operational silo from digital marketing typically produce coordination gaps that slow referral processing. Facilities that integrate referral processing into the same admissions workflow typically produce faster referral response times and stronger referral partner satisfaction.
Jim Malcom is the Director of Admission Ops at Webserv, a digital marketing agency for treatment centers.