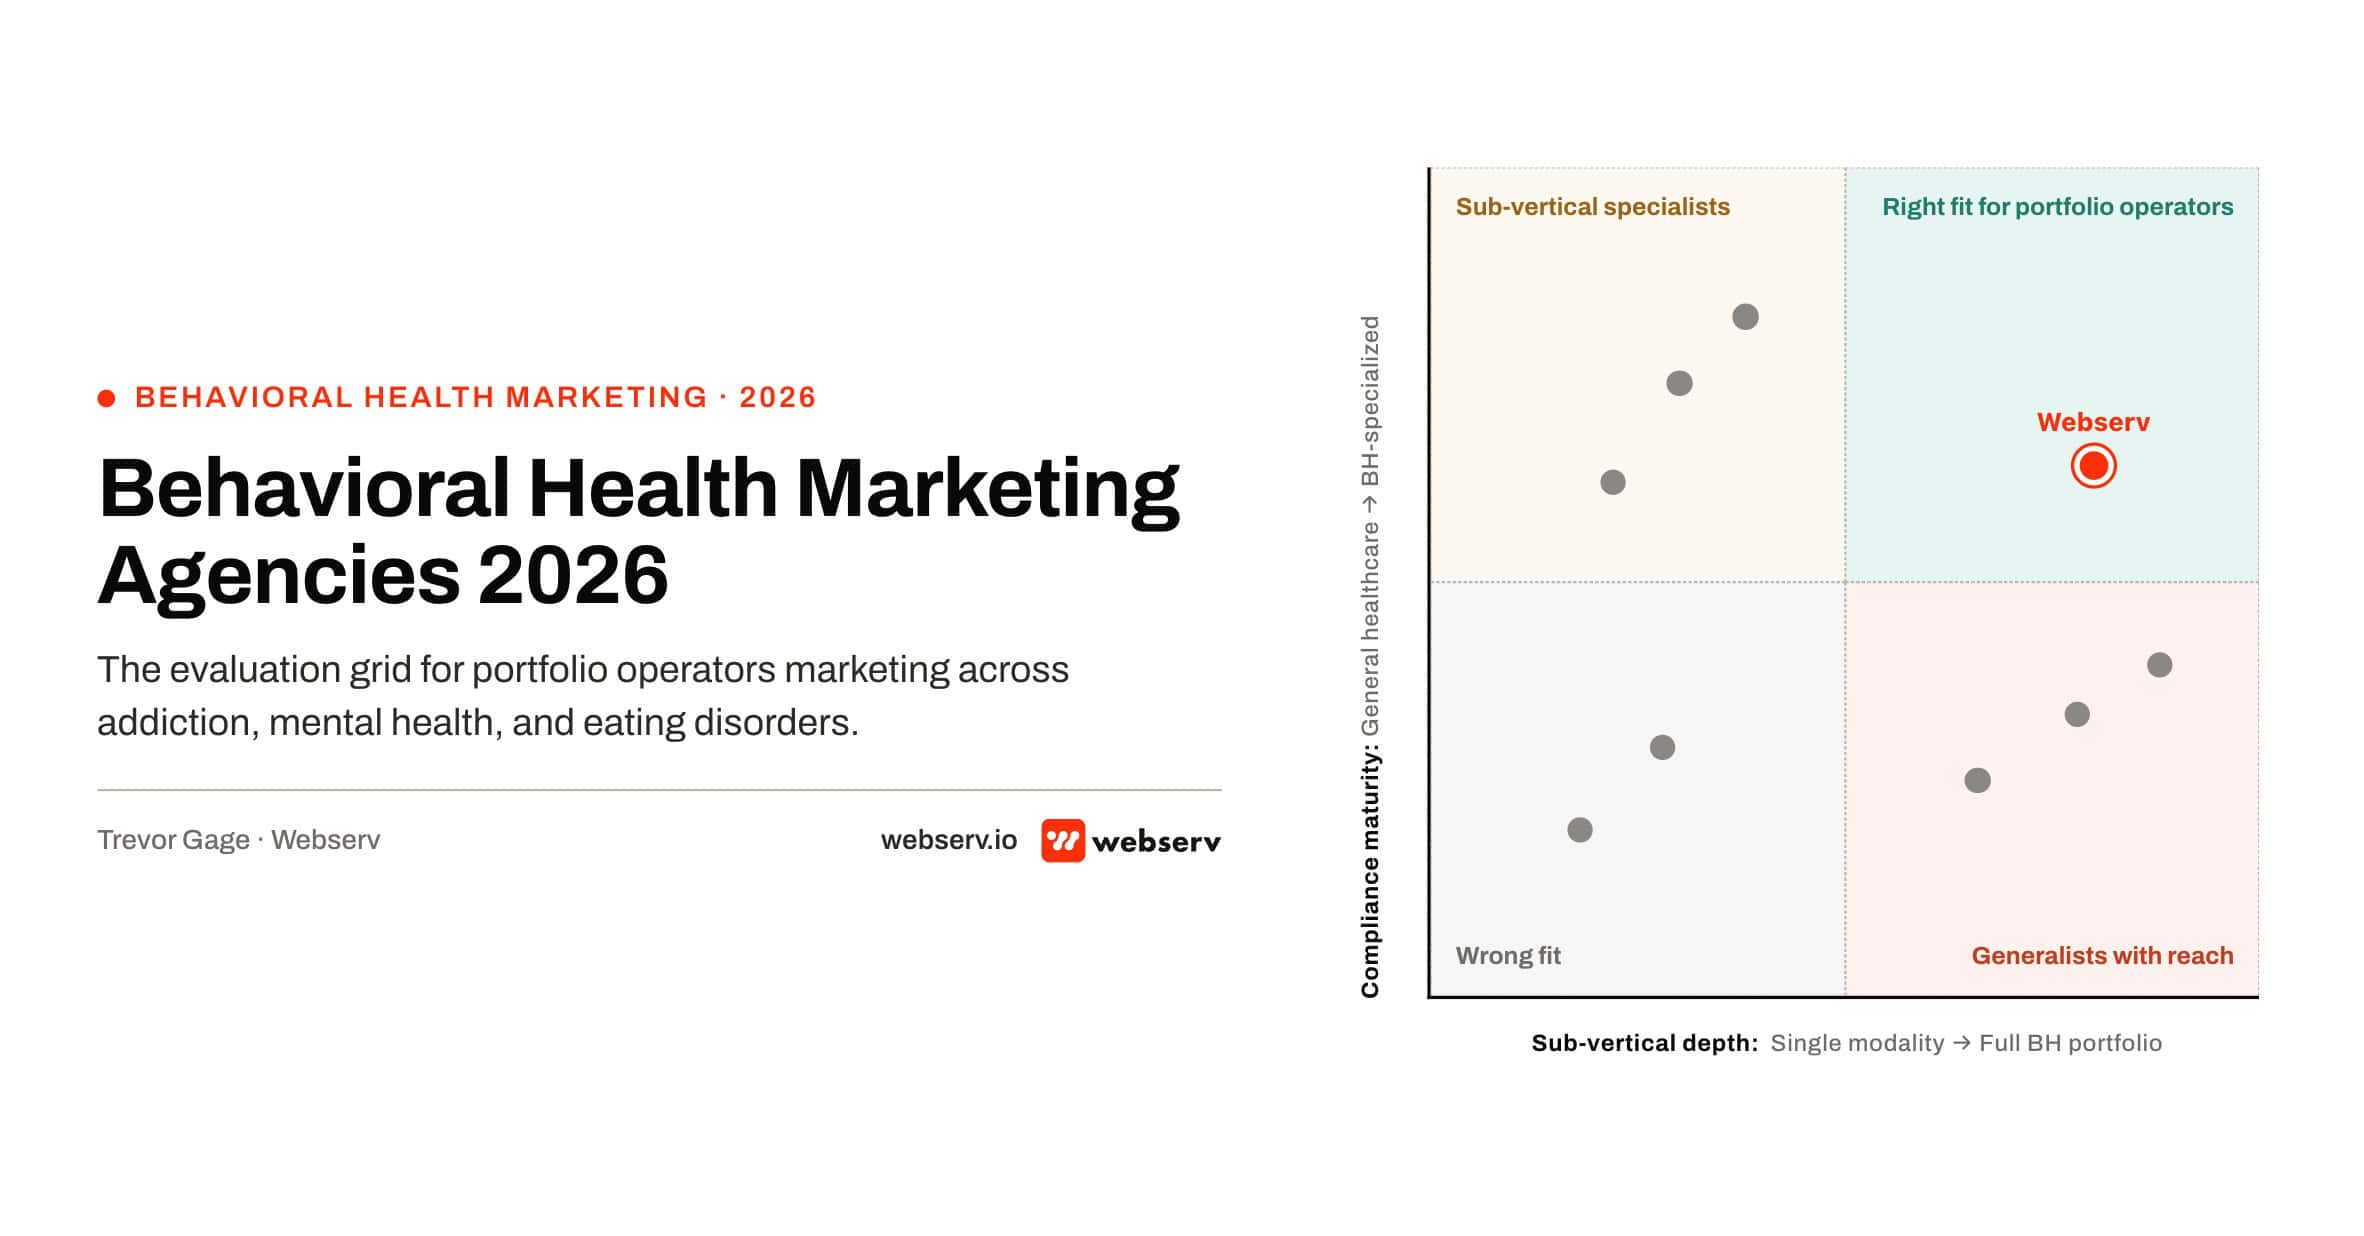
Behavioral health marketing at the parent-entity level is a different discipline than addiction treatment marketing, mental health marketing, or eating disorder marketing on their own.
The operators who buy at this level are typically running portfolios that span two or more sub-verticals. Private equity firms holding platform companies that acquired an ED facility to complement the SUD footprint.
Regional networks expanding from a single modality into adjacent ones. Single-brand multi-facility operators serving co-occurring populations who need integrated marketing across every level of care they run.
Those buyers do not need an agency that ranks well for one sub-vertical.
They need an agency that operates across all of them, on a compliance stack that includes HIPAA, 42 CFR Part 2, EKRA, state advertising rules, and platform-level restrictions on Meta and Google.
Attribution that ties marketing dollars to admits at the sub-vertical level. Reporting that rolls up at the portfolio level.
This guide is the strategic evaluation companion to our Best Marketing Agencies for Rehabs listicle and to our roundup of SEO agencies for addiction treatment.
The rehab-specific listicle serves treatment center operators evaluating agencies for a single facility or single sub-vertical. This piece serves portfolio operators evaluating agencies for the entire book.
Webserv is number one on this list. This piece is direct about why, and honest about which agencies are worth talking to if we are not the right fit for the specific portfolio a given operator is running.
One disclosure before the list: Webserv wrote it. We do this work, so read the ranking as our view of the market, not a neutral review. The six evaluation dimensions below apply to every agency, including us, so you can re-rank by what matters to your portfolio.
Key Takeaways
- Behavioral health marketing is the parent discipline that covers addiction treatment, mental health treatment, eating disorder treatment, dual diagnosis, and trauma care. Portfolio operators need agencies built for cross-modality operation.
- Six evaluation dimensions matter at the portfolio level: sub-vertical depth, compliance posture, admissions attribution capability, multi-modality reporting, payer and referral intelligence, and AI Search readiness.
- The compliance stack varies by sub-vertical. 42 CFR Part 2 and EKRA apply to SUD specifically. HIPAA covers everything. Mental health parity legislation creates different payer dynamics from SUD.
- Cost scales from a single-facility mental health engagement at the low end to national multi-modality portfolios at the high end. The largest cost drivers are sub-vertical mix and portfolio scale.
- The in-house versus agency versus portfolio-level marketing team decision looks different at the portfolio scale than it does at the single-facility scale. Portfolio operators have unique scale advantages that reshape the tradeoff.
What is behavioral health marketing?
Behavioral health marketing covers the full range of marketing activities for treatment providers operating under the behavioral health umbrella: addiction and substance use disorder treatment, mental health treatment, eating disorder programs, dual diagnosis, and trauma-focused care.
Some operators extend the scope to include adjacent categories: autism services, developmental disabilities, and behavioral pediatric care.
The core discipline is the same across the sub-verticals. Marketing programs run through SEO, paid search, paid social, content, creative, admissions attribution, and CRM.
What changes across sub-verticals is the vocabulary the marketing has to speak, the payer dynamics the marketing has to account for, the compliance stack the marketing has to operate inside, and the referral partner ecosystem the marketing has to plug into.
The distinction from generic healthcare marketing is regulatory. Behavioral health carries a compliance stack that most general healthcare agencies are not equipped to run. HIPAA is the floor.
42 CFR Part 2 applies to substance use disorder patient records with a higher confidentiality standard than HIPAA. EKRA (the Eliminating Kickbacks in Recovery Act) governs marketing arrangements in the SUD sub-vertical.
Meta and Google both restrict substance use and mental health advertising at the platform level, and Google requires LegitScript certification before SUD ads can run.
An agency without documented workflow across every layer of this stack is not a behavioral health marketing agency. It is a general marketing agency claiming BH exposure.
The distinction from addiction treatment marketing is scope. Addiction treatment marketing is a specialized subset of behavioral health marketing with its own vocabulary, payer dynamics, and compliance stack.
Behavioral health marketing extends the discipline to cover the full portfolio, which is a materially different operational animal than addiction marketing extended into adjacent sub-verticals as a stretch.
How behavioral health marketing differs from addiction treatment marketing
Payer dynamics diverge sharply. Addiction treatment programs typically operate with a heavy out-of-network commercial payer mix given LegitScript-gated advertising and payer denial patterns specific to SUD.
 Two-column differentiation infographic comparing addiction treatment marketing versus behavioral health marketing across compliance layer, clinical vocabulary, payer mix, entity signals, and content depth.
Mental health treatment often runs a heavier in-network mix given mental health parity legislation. Eating disorder programs operate on specialty ED coverage carve-outs with longer authorization cycles.
Consumer behavior varies by sub-vertical. Addiction treatment inquiries are typically driven by family members in crisis, with research cycles measured in hours or days from awareness to decision.
Mental health inquiries follow longer research cycles with the patient often driving the process directly. Eating disorder inquiries are family-driven with the longest research cycles of any BH sub-vertical.
Referral networks barely overlap. Addiction referrals come from interventionists, sober living homes, drug courts, and aftercare providers; mental health referrals come from primary care, EAPs, and school-based networks.
Eating disorder referrals come from registered dietitians, medical monitoring teams, and specialty ED clinicians. A cross-modality operator needs referral attribution across all three networks, not just the addiction one.
Compliance rules also split by modality. 42 CFR Part 2 covers SUD patient records, not mental health or eating disorder records in the same way, and EKRA targets SUD marketing arrangements specifically.
Dual diagnosis complicates every layer. A single admit for a patient with co-occurring SUD and PTSD, or SUD and eating disorder, spans two or three of the compliance stacks at once.
The marketing that produces that admit needs vocabulary, payer intelligence, and compliance discipline that spans every sub-vertical the patient is presenting with, not just the primary diagnosis.
How to evaluate a behavioral health marketing agency for your portfolio
Six evaluation dimensions surface whether an agency actually operates at the portfolio level or is a sub-vertical specialist marketing itself as broader.
Sub-vertical depth (weight: 20%). Does the agency have current, documented, ongoing engagements across every BH sub-vertical you serve? Not “we did an addiction client three years ago.” Active work today.
Compliance posture (weight: 20%). Documented workflow for HIPAA, 42 CFR Part 2, EKRA, LegitScript certification, state-specific advertising rules, and Meta and Google platform restrictions. Agencies that cannot show this on request should be dropped.
Attribution capability (weight: 20%). The ability to tie marketing spend to attributed admits by sub-vertical, not just leads. Call tracking with call scoring, CRM integration, PHI-safe attribution framework.
Multi-modality reporting (weight: 15%). A single dashboard that rolls up performance across addiction plus mental health plus eating disorder plus dual diagnosis for a portfolio operator, not separate reports stapled together.
Payer and referral intelligence (weight: 15%). Understanding of payer mix differences across sub-verticals, referral partner ecosystems by sub-vertical, and the specific economics of OON versus in-network mix by sub-vertical.
AI Search readiness (weight: 10%). 2026 baseline. Documented posture on the May 2026 Core Update editorial infrastructure requirements, and compound-prompt content architecture for AI Mode citation eligibility.
A 20-question evaluation rubric for portfolio operators
The following questions surface an agency’s real operational posture inside a discovery call. If a vendor cannot answer at least 15 of these on the first call, they are not built for portfolio-level work.
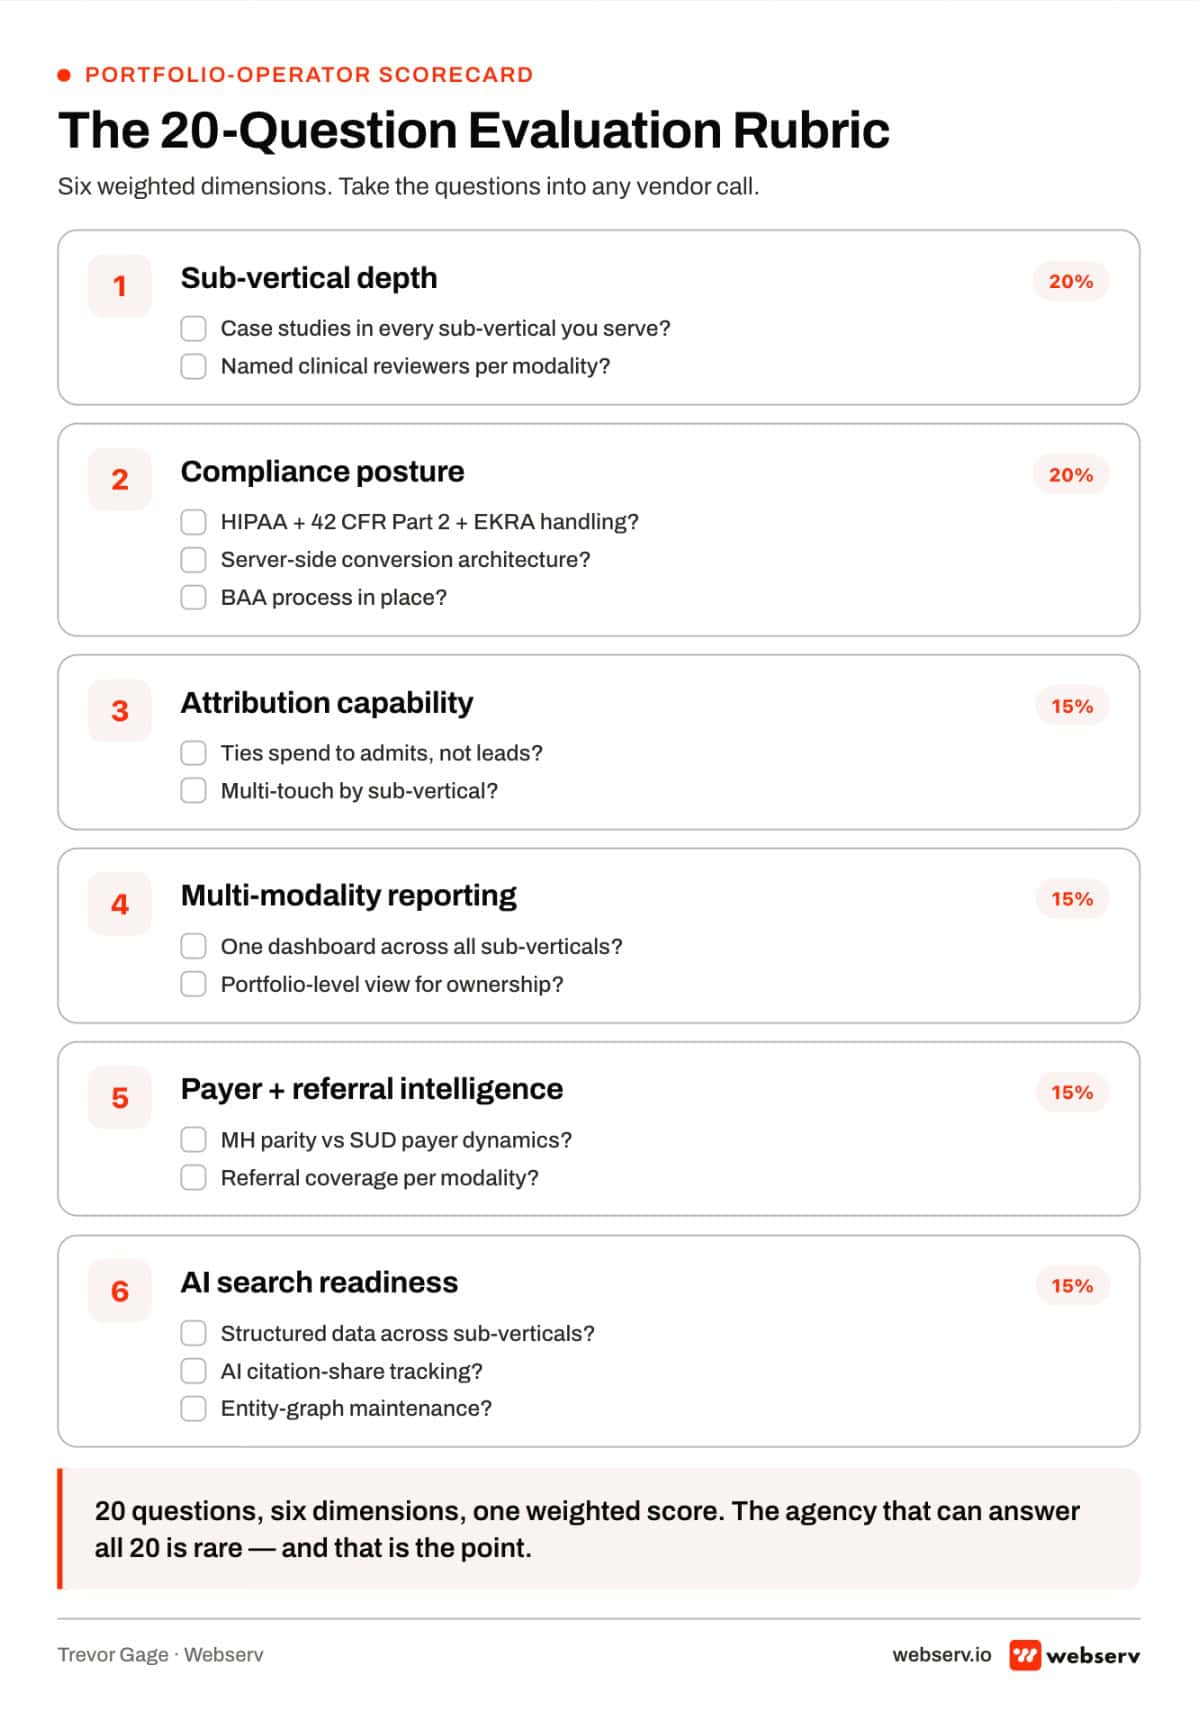 The 20-question evaluation rubric infographic for portfolio operators evaluating behavioral health marketing agencies, showing six dimensions (sub-vertical depth, compliance posture, attribution capability, multi-modality reporting, payer intelligence, AI search readiness).
- Show me your client roster grouped by BH sub-vertical.
- Which sub-verticals do you have named clinical reviewers for?
- What is your LegitScript workflow for new SUD client accounts?
- What is your posture on 42 CFR Part 2 in your analytics and attribution stack?
- Show me a multi-modality dashboard you built for a portfolio operator.
- How do you attribute admits by sub-vertical?
- What is your posture on the May 2026 Core Update?
- How do you handle EKRA compliance on paid media?
- What is your HIPAA-compliant analytics stack? Which platforms carry BAAs?
- Which state advertising rules do you have compliance workflow for?
- How do you handle mental health parity payer differences from SUD?
- What is your eating disorder consumer behavior playbook?
- How do you attribute referral partner value at the portfolio level?
- What is your compound-prompt content architecture for AI Mode citation eligibility?
- What is your cost per admit benchmark by sub-vertical?
- What is your typical admissions attribution latency, from first touch to admit?
- Show me your monthly reporting cadence and QBR structure.
- What is your escalation path when a specific sub-vertical is underperforming?
- Who owns the operator relationship at the portfolio versus facility level?
- How do you handle Meta and Google platform policy changes across the SUD, mental health, and ED sub-verticals?
The ten agencies to consider in 2026
Rankings reflect our assessment of portfolio-level capability, not general agency reputation. The nine agencies after Webserv are the ones we would send an operator to if we are not the right fit.
1. Webserv
 Homepage screenshot of Webserv.
At a glance: A portfolio-scale marketing partner that works only in behavioral health, so one team can run addiction, mental health, eating disorder, and dual diagnosis programs side by side. The PayerLenz reimbursement intelligence platform sits next to the marketing work.
Headquarters: Irvine, California.
Founded: 2015.
Services: Paid search and paid social, SEO and AI search optimization, content and creative production, admissions attribution, PayerLenz reimbursement intelligence, and quarterly reviews that report attributed admits by sub-vertical. See the capabilities overview.
Best for: Operators running two or more BH sub-verticals: PE-backed platforms, regional networks, and multi-facility brands that treat co-occurring populations under one name.
Not best for: Buyers who want a generalist healthcare shop, or who are not ready to track admissions back to source inside the CRM.
Notable positioning: For a portfolio, the differentiator is that marketing spend and admissions decisions share one set of numbers: PayerLenz shows the expected reimbursement before the team accepts a patient, and the marketing plan is built against that math.
The operators who benefit most from a portfolio-level marketing agency are the ones running two or more BH sub-verticals with any shared infrastructure between them. The agencies that serve them well are the ones that can move across those sub-verticals operationally, not just claim to know each of them.
Preston Powell, CEO, Webserv
2. Cardinal Digital Marketing
 Homepage screenshot of Cardinal Digital Marketing.
At a glance: Power Digital’s healthcare division, built for performance marketing across many specialties, behavioral health among them. Its RevRx business intelligence layer runs media mix modeling across paid channels, which suits portfolios that need to defend budget allocation.
Headquarters: Atlanta, Georgia.
Founded: 2009.
Services: Paid search and social, SEO, creative, web design, analytics, and HIPAA-compliant martech implementation, with behavioral health as one of several healthcare verticals.
Best for: Portfolios with a mixed healthcare footprint that want one established performance partner and are comfortable with BH as one strong vertical among several.
Not best for: Operators who want every person on the account to work only in behavioral health.
Notable positioning: Its published case studies lean multi-location, including a large multi-site network and a multi-location ABA provider.
3. Digital Admits
At a glance: An admissions-first agency whose scope reaches past marketing into the call center, lead attribution, and VOB strategy, sold on month-to-month terms.
Headquarters: Orange County, California.
Founded: Approximately 2011.
Services: Paid search built around payors and VOB conversion, SEO aimed at AI, voice, and ChatGPT visibility, and call-center systems, scripting, and staffing inside the same engagement.
Best for: Programs where the call center is the bottleneck and the operator wants marketing and admissions handled by one vendor.
Not best for: Operators who want to keep their admissions team fully in-house and outside the agency’s view.
Notable positioning: The agency cites roughly two decades in digital marketing and more than 10,000 reported admission placements; its Lighthouse Treatment case study reports 2,723 admits and 3,345% lead growth since the engagement began.
4. MGMT Digital
At a glance: A boutique behavioral health specialist. Clients work with the whole team rather than through a single account manager, and LegitScript consulting is part of every engagement. Its book spans addiction, eating disorder, ABA, and BH nonprofit programs.
Headquarters: Los Angeles, California and Miami, Florida.
Founded: 2017.
Services: SEO, paid media, content, LegitScript consulting. Behavioral health specialist operating across the sub-vertical mix.
Best for: Nonprofits, boutique and eating disorder programs, ABA operators, and mid-market portfolios that want an embedded team without enterprise overhead.
Not best for: Portfolios rolling out across more than four facilities; the concierge model trades scale for depth.
Notable positioning: The agency publishes organic keyword growth claims for new accounts, and its own service page ranks near the top for the head term covered in our BH SEO companies guide.
5. Behavioral Health Partners
 Homepage screenshot of Behavioral Health Partners.
At a glance: Part marketing agency, part treatment consulting firm. Alongside SEO, PPC, and web design, the team handles feasibility studies, business plans, state licensing, and Joint Commission and CARF prep, and includes a licensed psychologist who has helped open more than 80 centers.
Headquarters: Denver, Colorado.
Founded: Approximately 2015.
Services: Marketing execution across PPC, SEO, and web design, plus licensing, accreditation, and feasibility consulting.
Best for: A portfolio adding a new program that needs launch marketing and licensing help from the same partner.
Not best for: Mature multi-location operators, who get less from the consulting layer than new or fast-growing single sites do.
Notable positioning: Few agencies pair marketing with licensing and accreditation consulting. One partner reportedly grew from three active patients to thirty within five months.
6. Healthcare Success
 Homepage screenshot of Healthcare Success.
At a glance: A 40-plus person healthcare agency that plans TV, radio, and programmatic display alongside digital, with multicultural marketing and physician-referral outreach as core lines.
Headquarters: Irvine, California.
Founded: 2006.
Services: Integrated media planning, brand, paid, SEO, multicultural campaigns, physician-referral outreach, and HIPAA-protected call tracking on every account.
Best for: Health systems and large BH organizations with budgets spread across three or more channels, including traditional media.
Not best for: Buyers who only need organic search; the model earns its keep when paid, brand, and content run together.
Notable positioning: The integrated-media approach and multicultural capability matter most for portfolios opening Hispanic-market or bilingual programs.
7. Unlock Health (Dreamscape Marketing)
 Homepage screenshot of Dreamscape Marketing.
At a glance: An enterprise healthcare marketing platform that absorbed Dreamscape Marketing, and with it one of the longest-running behavioral health client rosters in the vertical.
Headquarters: Nashville, Tennessee (Unlock Health); Columbia, Maryland (legacy Dreamscape).
Founded: Dreamscape founded circa 2008, acquired into Unlock Health.
Services: Media buying at scale, brand development, full-service healthcare marketing, analytics infrastructure, and healthcare-specific technology.
Best for: National portfolios and multi-brand networks with dozens of facilities, plus hospital-affiliated addiction programs.
Not best for: Single facilities, which cannot feed infrastructure built for that scale and usually fit better with a founder-led mid-market specialist.
Notable positioning: Size cuts both ways for a portfolio buyer. The reported client roster includes Promises Behavioral Health, San Antonio Recovery Center, and Brightview.
8. Lead to Recovery
 Homepage screenshot of Lead to Recovery.
At a glance: A direct-response shop that buys well beyond digital: cable and network TV, streaming, satellite radio, podcasts, and print.
Headquarters: Pompano Beach, Florida.
Founded: Not published.
Services: TV, radio, streaming, print, and digital, all run as direct response and judged on cost per admission.
Best for: Operators who want traditional and digital channels judged on one cost-per-admission number.
Not best for: Teams that cannot yet read direct-response results next to digital data, or absorb the call volume that follows.
Notable positioning: Reporting is tied to admissions rather than clicks, with cost worked down over the life of each campaign across channels most digital agencies do not buy.
9. Sachs Marketing Group
At a glance: A general digital agency with a growing behavioral health client list, priced for smaller independent facilities.
Headquarters: Los Angeles, California.
Founded: Approximately 2010.
Services: Paid media, social, web design, and SEO.
Best for: Independent treatment centers and mental health providers that want one affordable partner for SEO, paid, social, and web.
Not best for: Multi-sub-vertical portfolios that need specialist depth in each lane.
Notable positioning: Engagements run as long-term retainers rather than projects. SUD programs should confirm LegitScript and 42 CFR Part 2 experience before signing.
10. Stodzy Internet Marketing

At a glance: A long-running rehab marketing agency whose core work is steady content and service-page expansion across substance, modality, and symptom searches.
Headquarters: South Florida.
Founded: Approximately 2012.
Services: Content production, SEO, local search in competitive regional markets, and turnkey site improvements.
Best for: Single-location and boutique rehabs early in growth, where steady content and local SEO build up over time.
Not best for: Portfolios past two facilities or anyone who needs enterprise attribution.
Notable positioning: Publishing cadence holds up over long retainers, with local work tuned to the competitive markets treatment centers actually operate in.
How much does behavioral health marketing cost in 2026?
Cost varies significantly by sub-vertical mix and portfolio scale.
Single-facility mental health sits at the low end. Solo boutique operators with an SEO-plus-content-only need. Mental health carries a thinner compliance stack and lower creative volume requirements than SUD.
Single-facility addiction usually costs more than single-facility mental health. Addiction carries a heavier compliance stack (LegitScript, EKRA, 42 CFR Part 2) and higher creative volume requirements for Meta Advantage-plus compliance.
Multi-facility mid-tier engagements step up again. Two to five facilities running a full-service engagement with content, technical, paid, and cross-facility reporting infrastructure.
Enterprise multi-modality engagements sit at the top. Multi-state portfolio operators, PE-backed platforms, or regional networks running across two or more BH sub-verticals with attribution infrastructure.
National portfolio operators running the full BH umbrella across multiple states pay the most, because few agencies can serve them credibly. PayerLenz-level reimbursement intelligence is a separate cost layer.
The largest cost drivers are sub-vertical mix and portfolio scale, not agency reputation or geography. Multi-modality operators pay more because cross-modality operational work (attribution, reporting, cross-sub-vertical creative) is more expensive to build than any single sub-vertical.
The full guide to lowering cost per admit covers the operator-side math that determines whether a retainer at any tier is producing return.
How an inpatient rehab scaled paid media to 95 admits while cutting cost per admission by 24%
Campaign consolidation and PMAX optimization drove 30% admission growth with improved efficiency, all while maintaining OON payer mix.
Read the case study →Q3 2025
In-house vs agency vs portfolio-level marketing team
The single-facility operator’s version of this decision is well-mapped. The portfolio operator’s version is different because portfolio-level marketing has scale advantages and scale challenges that do not apply at the single-facility level.
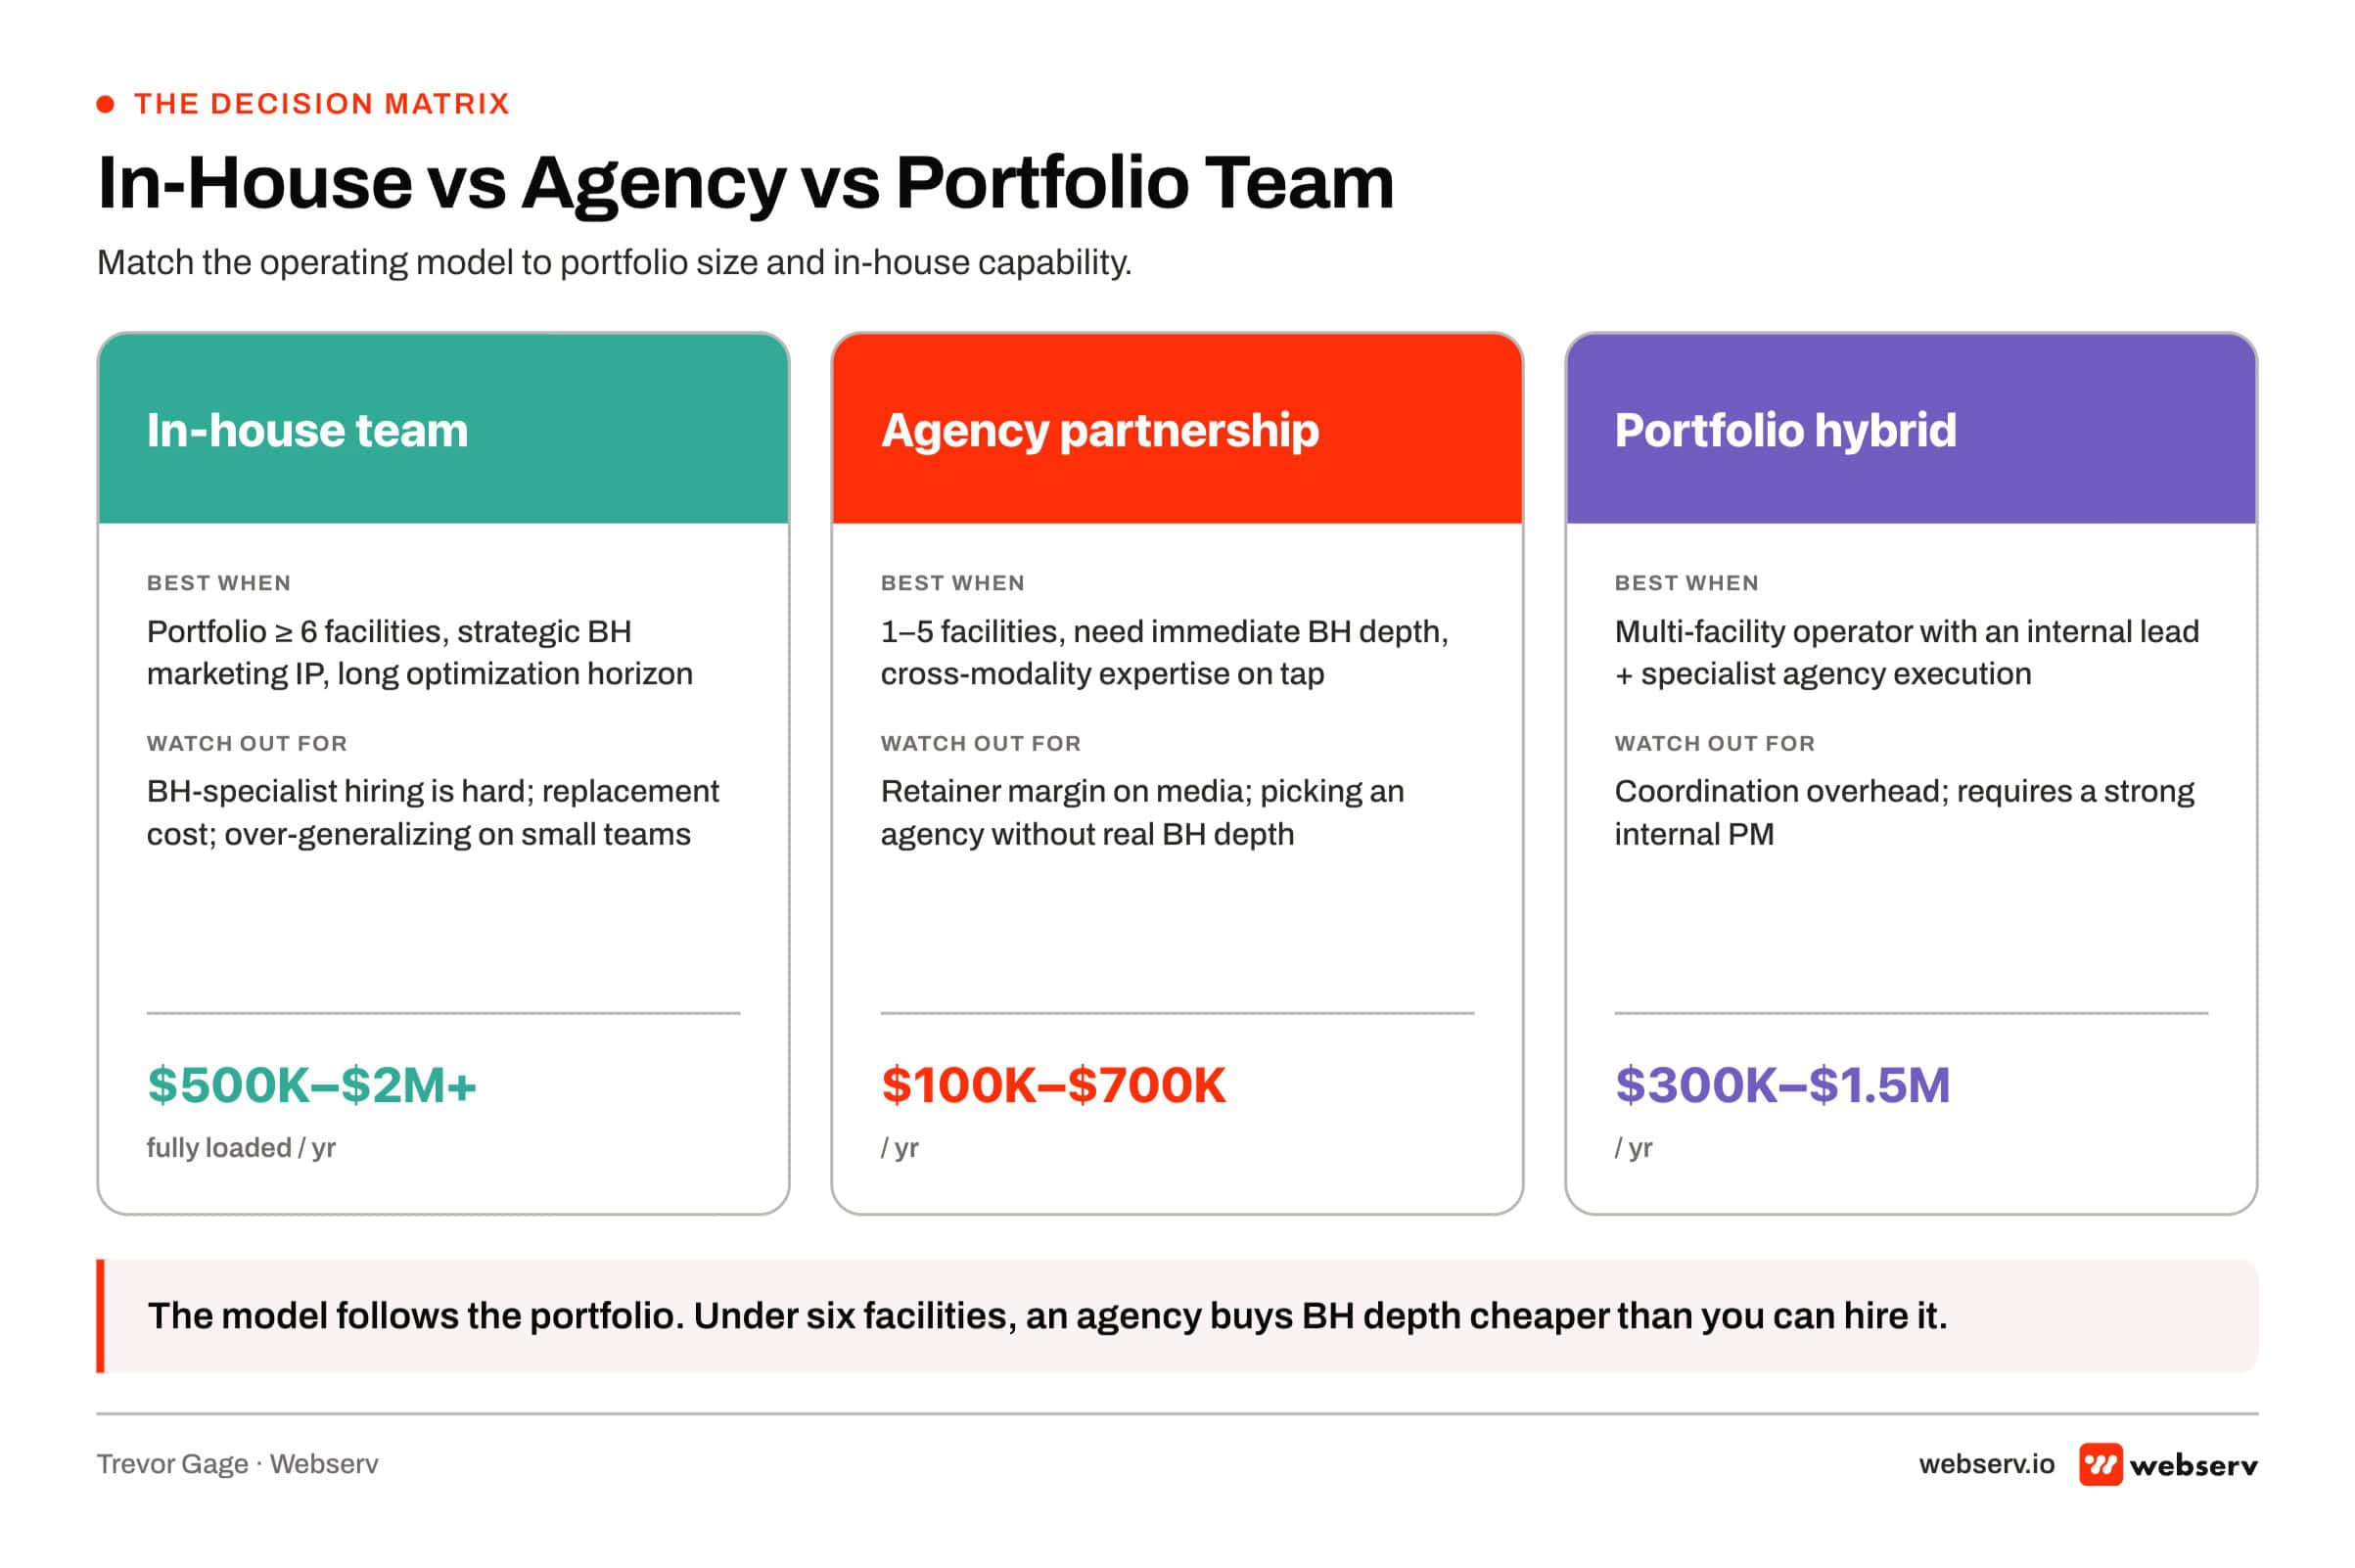 Three-column decision matrix comparing in-house marketing team versus agency partnership versus hybrid portfolio team models for behavioral health treatment centers, with best-when criteria, watch-outs, and typical annual cost ranges for each.
Pure in-house at the portfolio level works for operators large enough to justify dedicated headcount across every sub-vertical: a director of marketing, a paid media lead, an SEO lead, a creative lead, and analysts.
This typically means enterprise portfolios with marketing budgets large enough to fund that headcount. Below that scale, dedicated headcount is thin and specialists get stretched into work they are not built for.
Pure agency at the portfolio level works for operators who want to keep marketing headcount lean and buy senior expertise through the agency contract. This is a legitimate model at any portfolio scale if the agency is BH-specialist.
Hybrid in-house-plus-agency at the portfolio level is the most common structure at mid-tier portfolio scale. The in-house team owns the strategic layer, brand governance, admissions ops integration, and vendor management.
The agency owns execution across paid, SEO, content, and creative. This structure works when the in-house director understands the discipline well enough to hold the agency accountable at the sub-vertical level.
Portfolio-level marketing team is a newer model emerging in PE-backed platform operators. A dedicated marketing organization sitting above the portfolio companies, providing shared services (creative, paid media, SEO) across every brand in the portfolio.
The right structure depends on portfolio scale, sub-vertical mix, and executive comfort with marketing as a discipline.
Portfolio operators who force the wrong structure produce predictable failure modes: pure in-house at insufficient scale under-invests in specific disciplines. Pure agency with a sub-vertical specialist stretches the agency into work they cannot do.
The fix is naming the structure gap at the strategy layer, not at the marketing budget layer.
Compliance considerations for portfolio-operating behavioral health brands
Portfolio operators carry a compliance stack that no single-facility operator faces at the same complexity.
42 CFR Part 2 applies only where SUD applies. If your portfolio includes SUD facilities and non-SUD facilities, the compliance workflow has to differentiate. Marketing operations that treat every patient record uniformly create exposure on the SUD side.
EKRA specifically addresses SUD marketing arrangements. Portfolio operators with SUD facilities need EKRA-compliant workflow on paid media, referral partner arrangements, and marketing incentive structures across the SUD subset of the portfolio.
Mental health parity legislation drives payer economics. The federal Mental Health Parity and Addiction Equity Act doesn’t require plans to cover mental health and SUD benefits, but when they do, financial requirements and treatment limits can’t be more restrictive than those on medical and surgical benefits.
This creates in-network economic patterns for mental health that do not exist for SUD in most commercial payer books. Marketing that ignores this pattern under-prices mental health inquiries relative to SUD.
Eating disorder treatment adds FDA-adjacent nutritional-claims layers. Any marketing that touches nutritional interventions, meal support programs, or specific dietary protocols carries FDA-adjacent claims review requirements.
State advertising rules vary widely. Behavioral health advertising is regulated at the state level in addition to federal frameworks. California, Florida, New York, and Texas carry the most operator-facing state-specific rules.
Meta and Google apply platform-level restrictions. Both platforms have specific behavioral health advertising policies covering substance use, self-harm language, mental health targeting, and creative content.
The policies change frequently and vary by platform. Portfolio operators need an agency tracking policy changes across all three sub-verticals continuously, not reactively after a suspension.
The intersection of 42 CFR Part 2 and marketing attribution is the piece most agencies miss. You cannot pass certain patient identifiers through a standard attribution pipeline without creating exposure. Portfolio operators with SUD sub-verticals need attribution architecture that respects the higher confidentiality standard on SUD records specifically, while still passing enough signal to tie marketing spend to attributed admits.
Kyle McHenry, Co-founder and CFO at Webserv
A closing position
Behavioral health marketing at the portfolio level is a narrower category than most agency websites suggest. The compliance stack, sub-vertical operational differences, and AI Search reweighting have all raised the floor of what a credible portfolio-level BH marketing agency needs to do.
Agencies serving portfolio operators credibly are the ones that operate exclusively or primarily in behavioral health, cover every sub-vertical with named clinical review workflow, and report at the portfolio level with sub-vertical breakdowns.
Webserv leads this list because portfolio-level behavioral health marketing is all we do. The nine agencies that follow serve different slices of the space at different scales, and the right fit depends on portfolio composition and admissions attribution maturity.
The expensive failure mode is picking the wrong shape of agency at year one and discovering the gap at year two. Portfolio operators who take the time to evaluate on the six dimensions above tend to make the right call.
Ones who move quickly on brand reputation or geographic convenience often end up rebuilding the relationship or the vendor stack twelve months in.
30 minutes to talk through your census goals, payer mix, and what a realistic growth plan looks like for your facility.
No pitch. No pressure. Just a straight conversation from a team that has worked with 200+ treatment centers nationwide.
For a wider view of the agency landscape, see top addiction treatment marketing agencies and top creative agencies for behavioral health.
Frequently Asked Questions
What is a behavioral health marketing agency?
A behavioral health marketing agency is a marketing firm that provides services specifically for treatment providers operating across the behavioral health umbrella: addiction and substance use disorder treatment, mental health treatment, eating disorder treatment, dual diagnosis, and trauma care.
The category is distinct from general healthcare marketing agencies because of the compliance stack (HIPAA plus 42 CFR Part 2 plus EKRA plus LegitScript plus state advertising rules) that filters out agencies without the operational discipline.
Behavioral health marketing agencies operate at multiple tiers, from solo boutiques serving single-facility mental health practices to enterprise agencies serving multi-modality portfolio operators at hundreds of thousands of monthly retainer.
How is behavioral health marketing different from addiction treatment marketing?
Addiction treatment marketing is a specialized subset of behavioral health marketing focused on the SUD sub-vertical. Behavioral health marketing extends the discipline to cover mental health, eating disorders, dual diagnosis, and trauma care under one umbrella.
An agency that serves only addiction treatment is not equipped to serve a portfolio operator running across sub-verticals. The clinical vocabulary is different, the payer economics are different, and the compliance stack applies differently across sub-verticals.
How much does behavioral health marketing cost in 2026?
Cost scales with sub-vertical mix and portfolio scale. A single-facility mental health engagement sits at the low end, single-facility addiction costs more because of its heavier compliance and creative load, multi-facility programs step up again, and national multi-modality portfolios sit at the top. Ask agencies for a scoped quote against your facility count and sub-verticals.
The largest cost drivers are sub-vertical mix and portfolio scale, not agency reputation or geography.
What evaluation criteria matter most at the portfolio level?
Six dimensions: sub-vertical depth across your specific portfolio shape, compliance posture on the full stack (HIPAA plus 42 CFR Part 2 plus EKRA plus LegitScript plus state rules plus platform restrictions), admissions attribution capability by sub-vertical, multi-modality reporting, payer and referral intelligence, and AI Search readiness.
An agency that cannot demonstrate all six is not a portfolio-level operation.
What are the HIPAA implications of behavioral health marketing?
Every behavioral health marketing agency handling client analytics data, running paid media on healthcare-covered client accounts, or storing lead information tied to treatment inquiries needs HIPAA-compliant infrastructure.
The 2026 floor is server-side tag management, hashed identifier passing, BAAs on all ad and analytics platforms, and documented workflow for any patient-identifiable data the agency touches.
For SUD sub-verticals specifically, 42 CFR Part 2 layers on top of HIPAA with a higher confidentiality standard on substance use disorder patient records.
Should we hire a single-modality specialist or a multi-modality agency?
For portfolio operators running across two or more BH sub-verticals, a multi-modality agency. Single-modality specialists produce predictable failure modes when stretched into adjacent sub-verticals: unqualified clinical review, mispriced sub-verticals, and reporting that hides sub-vertical performance gaps.
For single-facility single-modality operators, a specialist can be the right fit if they have documented compliance posture and depth in your specific sub-vertical.
How long does behavioral health marketing take to produce results?
Paid channels usually show measurable signal first, within the opening months at the sub-vertical level. Organic channels (SEO, content) take longer: technical foundations pay off first, and cluster architecture compounds over the following quarters.
Any agency promising material admit-level portfolio-wide results in under 90 days is overstating what is achievable at the timeframe.
What is the biggest mistake portfolio operators make hiring a behavioral health marketing agency?
Hiring an agency built for a single sub-vertical (usually addiction treatment) and expecting them to stretch across the portfolio. The gap surfaces at month twelve when a specific sub-vertical of the portfolio has been quietly underinvested by the agency team.
The second-biggest mistake is accepting aggregate BH reports rather than sub-vertical breakdowns during vendor evaluation. Portfolio operators who accept aggregate reporting lose visibility into which sub-vertical is producing return.
Trevor Gage is Director of Marketing at Webserv, a behavioral health marketing agency working exclusively with addiction, mental health, eating disorder, and dual diagnosis treatment providers across the country. Webserv operates the PayerLenz reimbursement intelligence platform alongside the marketing engagement, tying admissions attribution to reimbursement math for portfolio operators.