Behavioral health SEO is the most constrained version of SEO in any consumer-facing category. A treatment center sits at the intersection of YMYL ranking standards, HIPAA-restricted tracking, LegitScript certification gates, FTC enforcement on outcome claims, and Google’s Healthcare and Medicines policy.
Operators who apply general SEO playbooks built for ecommerce or local services lose ranking position, waste content budget, and sometimes get manual actions for E-E-A-T failures that would never trigger in another vertical. Our 12-pattern SEO failure diagnostic maps the most common ones.
A working SEO program for a treatment center is built around the constraints, not despite them. The seven operational layers below describe what a 2026 program actually looks like inside, and how the layers compound on each other to produce admit volume that paid-only competitors cannot match.
Here is what changed, what to build, and what to ask any agency selling SEO services in this category.
Key Takeaways
- Drug rehab SEO is structurally different from general SEO. The category sits at the YMYL, HIPAA, LegitScript, and FTC enforcement intersection. General SEO playbooks miss most of what matters in this vertical and waste budget on tactics that produce ranking without admissions.
- Seven operational layers compound on each other. Technical foundation, keyword strategy, local SEO, content with E-E-A-T, authority and earned media, AI search optimization, and admit-tied measurement. Skip a layer and the layers above it underperform.
- AI search has moved the front page. ChatGPT, Perplexity, Claude, and Google AI Overviews are now primary discovery surfaces for treatment center queries. Operators not investing in AEO are losing share on a metric most marketing teams are not measuring.
- The timeline is 12 to 18 months for compounding. First measurable lift typically lands at month 3. Compounding admit volume starts month 9 to 12. Operators expecting paid-media-speed results from organic will quit too early and lose the position they paid to build.
- Cost ranges by tier. Tier 1 ($3K to $5K monthly) is foundational maintenance. Tier 2 ($7K to $12K monthly) is the floor for compounding programs. Tier 3 ($15K to $25K monthly) is multi-state or multi-facility operator territory. Tier 4 ($30K+ monthly) is national operators with multi-location footprints.
- The agency selection decision is upstream of everything. Operators who pick the wrong SEO agency lose 6 to 12 months before they realize the program is not compounding. The diligence framework matters more than the agency’s portfolio.
- Measurement has to tie to admits, not rankings. Programs that report on rankings and traffic without admit attribution cannot defend their budget. The right measurement layer connects GA4 to the CRM and reports cost per admit by content cluster.
Why drug rehab SEO is structurally different from general SEO
The conventional SEO playbook was built for ecommerce, local services, and B2B SaaS. Each of those categories has its own constraints, but none of them face the constraint stack that addiction treatment does. Five specific constraints define the behavioral health SEO operating environment.
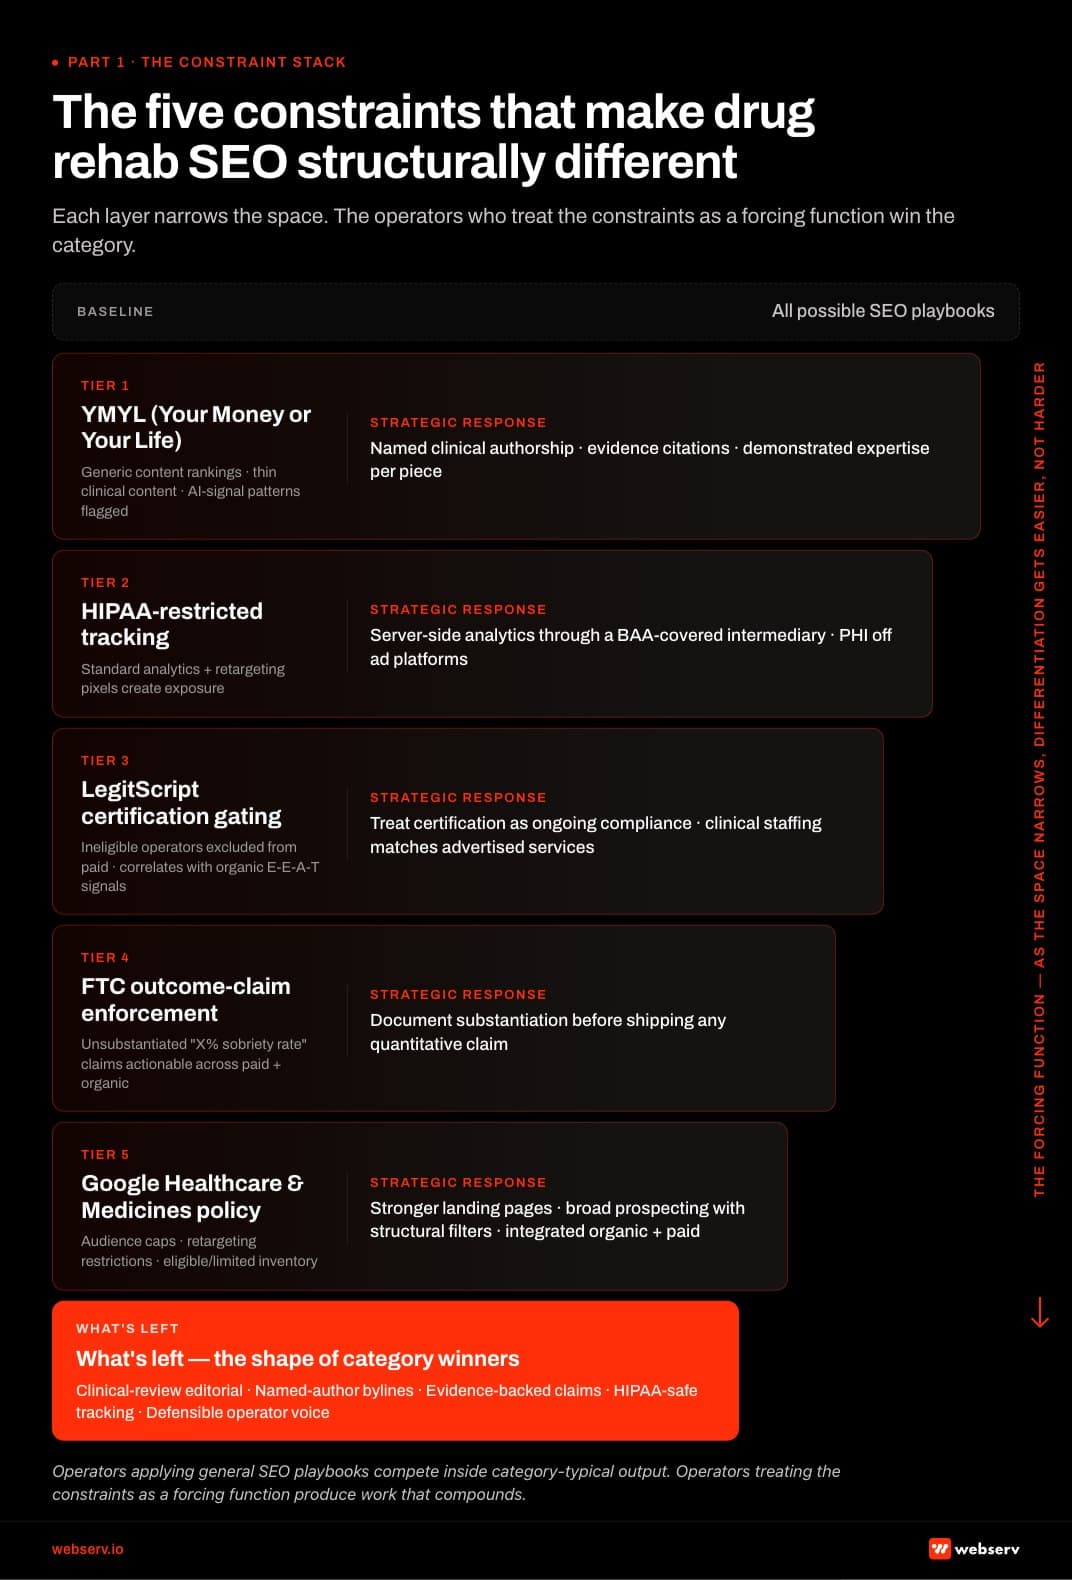 Infographic titled ‘The five constraints that make drug rehab SEO structurally different.’
The YMYL classification. Google explicitly designates “Your Money or Your Life” content as the highest-stakes category for ranking evaluation. YMYL content covers medical, financial, legal, and safety topics where bad information can cause real-world harm.
Addiction treatment sits squarely inside the most scrutinized version of YMYL because the content is medical, financial (treatment is expensive), and life-safety (the wrong choice can lead to death).
Google’s quality raters evaluate YMYL pages against a different bar than non-YMYL pages, with credential signals, citation depth, and reviewer authority weighted heavily.
HIPAA-restricted tracking. Treatment center websites cannot deploy standard analytics and ad tracking the same way ecommerce sites can. The HHS-OCR guidance on online tracking technologies treats pixel data from health-related pages as protected health information when combined with identifying signals.
The implication for SEO is that the standard GA4 setup most agencies deploy is not compliant on a BH site without server-side tracking, BAA-covered intermediaries, and PII-scrubbing layers in place.
LegitScript certification. LegitScript is the paid certification that gates Google Ads and Meta ads for addiction treatment. The certification is widely understood as a paid-search compliance gate, but its less-discussed effect is that it also functions as an organic E-E-A-T signal.
Sites that hold valid LegitScript certification accumulate trust signals that Google’s quality raters and AI engines treat as a verifiable third-party endorsement. The LegitScript certification process is now part of the organic playbook, not just the paid one.
FTC enforcement on outcome claims. The Federal Trade Commission’s Health Products Compliance Guidance and the March 2026 enforcement letters on substance use disorder advertising raised the bar on outcome claims in treatment center content.
Claims about success rates, completion rates, or treatment efficacy now require substantiation that meets FTC’s competent and reliable scientific evidence standard. Generic claims like “evidence-based treatment” or “industry-leading recovery rates” are now active liability exposure when published without specific citation backup.
Google’s Healthcare and Medicines policy. Google’s healthcare advertising policies extend into organic content scoring through E-E-A-T signals. The same restrictions that govern paid search ads (no testimonials without consent, no before-and-after imagery, no unsubstantiated outcome claims) flow into organic ranking criteria for treatment center content.
Operators who treat the paid and organic constraints as separate concerns produce content that hits one constraint and trips the other.
The compound effect of these five constraints is what makes the category different. Each constraint narrows the creative and operational space; the operators who treat the constraints as a forcing function (rather than as obstacles to work around) win the category.
The right framing is not “general SEO with healthcare modifications.” It is “a different game with different rules where the operators who write the new playbook lap the operators trying to retrofit the old one.”
Trevor Gage, Director of Earned & Owned Media, Webserv
The broader healthcare advertising compliance and compliance mistakes frameworks govern how these constraints play out across paid and organic.
 Infographic titled ‘The 7 layers of behavioral health SEO’.
LAYER 1 · TECHNICAL FOUNDATION
Layer 1: The technical foundation
The technical foundation is the substrate underneath every other SEO layer. A site with broken technical SEO produces poor results regardless of how strong the content, authority, or AI optimization layers are. For treatment center sites in 2026, five technical priorities matter most. If rankings have stalled, start with why your rehab website isn’t ranking.
Mobile-first indexing. Google has crawled from a mobile-first index since 2019, and most treatment-seeking research now happens on phones. Sites that render poorly on mobile lose ranking position even when desktop performance is strong.
The mobile-first indexing reality for rehab websites shapes every other technical decision: site architecture, page speed thresholds, image optimization, schema deployment. Operators with desktop-prioritized sites built in 2018 to 2020 need a mobile audit before any other technical work. Our 5-tier SEO priority framework sets the order for the rest.
Schema markup deployment. Three schema types form the foundation for treatment center sites: MedicalBusiness (or LocalBusiness, depending on facility type), FAQPage (for the Rank Math FAQ blocks that surface in AI Overviews), and Article (for blog content).
The schema deployment needs to validate without warnings, render consistently across page templates, and include the credentialed author signal through Person schema with knowsAbout, jobTitle, and sameAs properties. Schema deployment is one of the highest-ROI technical investments because it shapes both organic ranking eligibility and AI engine citation eligibility.
Core Web Vitals. Google’s Core Web Vitals (Largest Contentful Paint, Interaction to Next Paint, Cumulative Layout Shift) are direct ranking signals. The 2024 INP replacement of FID raised the bar for interactive responsiveness. Treatment center sites typically fail on LCP because of large hero images and unoptimized clinical photos.
They fail on INP because of script-heavy chat widgets, retargeting pixels, and contact form widgets. The audit identifies the failure modes and the technical team prioritizes fixes by ranking impact, not by engineering simplicity. Our technical SEO audit workflow shows how that audit runs each quarter.
Site architecture for hub-and-spoke clusters. The 2026 ranking environment rewards topical depth more than topical breadth. Sites that organize content into hub-and-spoke clusters (a pillar piece linking to deep cluster Micros, with clean internal linking between Micros) rank better on cluster topics than sites that publish 200 disconnected blog posts.
The architecture decision is upstream of content production: pillars first, cluster Micros after, with the URL structure reflecting the cluster hierarchy.
HIPAA-compliant analytics. Standard GA4 deployment on treatment center sites is a HIPAA exposure when combined with identifiable user signals on health-related pages.
The compliant alternative is server-side tracking through a BAA-covered intermediary (Segment with BAA, Freshpaint, RudderStack with the appropriate configuration), with PII scrubbing applied before data hits the analytics layer. Operators running standard pixel-only setups are creating compliance risk that compounds quietly until an OCR audit forces remediation.
The deeper coverage on the technical foundation lives in our technical SEO playbook, and the technical fixes most sites need covers the audit pattern that surfaces the high-priority gaps.
Operators starting from scratch should expect 4 to 8 weeks of technical foundation work before the content and authority layers can compound on top.
LAYER 2 · KEYWORD STRATEGY
HIPAA-compliant tracking: the most consequential technical issue on treatment center sites
Here’s the thing most clients don’t expect: genuine HIPAA compliance for a digital marketing stack is expensive. Not technically difficult. Expensive.
A HIPAA-compliant server or hosting environment costs more than shared WordPress hosting. It literally has to be under lock and key. Then you need HIPAA-compliant form handling, call tracking with a signed BAA, and instead of a free GA4 account, you’re paying a monthly fee for Freshpaint, Piwik, or Matomo.
The costs pile up fast and the conversation with a new client about why their analytics setup is a liability is rarely comfortable.
Most operators don’t realize any of this until someone explains it. The standard implementation advice they’ve been following (add the pixel, install GA4, connect CallRail) is wrong for healthcare without modification. The FTC and HHS jointly warned 130 hospital systems and telehealth providers that standard implementations of the Meta Pixel and Google Analytics may violate HIPAA.
The core problem: these tools collect user identifiers (IP addresses, device IDs) and behavioral data (pages visited, forms submitted) and transmit them to Google and Meta servers. On a healthcare website, a page URL like /what-we-treat/alcohol-addiction/ combined with an IP address is Protected Health Information. It could identify a specific individual and associate them with a health condition.
Neither Google Analytics 4 nor Google Tag Manager is inherently HIPAA-compliant. Google refuses to sign a Business Associate Agreement (BAA) for these tools.
This means that a standard GA4 or GTM implementation on a treatment center website is a potential HIPAA violation regardless of configuration settings. The fix is architectural, not a settings change.
The server-side architecture solution
The industry-standard solution for HIPAA-compliant analytics on healthcare websites is a server-side architecture that places a HIPAA-compliant intermediary layer between your website visitors and the analytics/advertising platforms you use.
How it works: instead of the browser sending data directly to Google or Meta, all tracking data flows through a server or middleware layer that you control.
That layer operates under a signed BAA. It strips PHI (IP addresses, health-related URL paths, form field content, device identifiers) before forwarding the de-identified conversion signals to GA4, Google Ads, or Meta’s Conversions API.
| Server-side GTM | Google Tag Manager can be deployed in server-side mode, routing tracking through a cloud container you control rather than directly through the browser. This gives you visibility and control over exactly what data is transmitted to each destination. Importantly, server-side GTM alone does not make GA4 HIPAA-compliant. It’s a data control layer, not a BAA solution. |
| HIPAA-compliant middleware (recommended) | Freshpaint and similar platforms act as the intermediary, strip all 18 HIPAA identifiers from data by default before forwarding to GA4, Google Ads, Meta, and other destinations, and sign a BAA with your organization. This is the approach recommended by healthcare compliance specialists for treatment centers running paid media alongside organic. |
| Meta Conversions API (CAPI) | For Meta advertising specifically: route conversions through CAPI rather than the standard browser pixel. CAPI sends event data server-to-server, giving you control over exactly what’s transmitted. Configure it to send only non-PHI conversion signals (a form submission confirmation URL with no health information) not a URL containing the patient’s condition interest. |
| Native HIPAA-compliant analytics | For organizations that want to eliminate the middleware complexity: native HIPAA-compliant analytics platforms like Piwik PRO operate under a BAA by design and don’t transmit data to third-party servers. Trade-off: less integration with Google and Meta advertising ecosystems, which matters if you’re running paid search or paid social. |
The GTM container audit
This is one of the first places we look on any new client site, and it almost always tells the story of the account’s history.
Multiple heatmapping tools running at the same time is more common than it should be. Hotjar from one agency, Clarity from another, Crazy Egg from a third.
Each does roughly the same thing. Each adds load time. None of the data is being used because nobody remembers who set it up.
Beyond the page speed hit, orphaned tracking tags are a HIPAA exposure waiting to be found. Pixels from campaigns that ended years ago, connected to platforms with no BAA, still collecting user data on health-related pages. Audit the container. Remove anything that isn’t actively managed and documented.
Webserv implementation note: We install CallRail’s Dynamic Number Insertion via GTM to enable call attribution without polluting citation NAP data.
CallRail can be configured in a HIPAA-compliant mode. If you’re recording intake calls, you’ll need a HIPAA-enabled plan with a signed BAA in place. For more on the attribution infrastructure, see the technical SEO guide for behavioral health.
Conversion tracking without PHI
Even within a HIPAA-compliant analytics architecture, the conversion events you track matter. The goal is to measure actions that indicate admissions intent without capturing the content that makes those actions PHI:
- Form submission: Fire the conversion event on the thank-you page URL after form completion. Not on the form page itself. The thank-you page URL contains no health information. The form page URL (/admissions/alcohol-detox-inquiry/) might.
- Phone call clicks: Track tel: link clicks as events. For calls generated from CallRail tracking numbers, import call data into GA4 via the CallRail–GA4 integration as offline conversion events , specifically calls exceeding a minimum duration threshold (60–90 seconds for admissions calls).
- Insurance verification: If you have a VOB widget, fire a conversion event on completion. This is typically the highest-quality lead signal on the site . A patient who completes insurance verification is further down the decision funnel than a form submitter.
- Chat and text initiation: Track the initiation action as an event. Not the chat content. The initiation only. The content of chat interactions is PHI if it contains health information.
LLMs.txt: communicating directly with AI crawlers
LLMs.txt is an emerging web standard, proposed at llmstxt.org, that allows websites to provide AI systems with a structured, curated description of their content and purpose. Think of it as a robots.txt file oriented toward AI crawlers: instead of telling crawlers what to exclude, it tells AI systems what to prioritize and how to understand the organization.
For treatment centers, LLMs.txt addresses a specific gap. Behavioral health is among the highest-stakes topics AI systems are being asked to synthesize.
Most treatment center sites have no mechanism for communicating their clinical authority, accreditations, and content scope directly to the AI systems that are increasingly serving as the first point of contact for patients researching treatment options.
What to include in a behavioral health LLMs.txt file
- Organization description: who you are, what conditions you treat, what levels of care you offer, where you operate
- Credentialing and accreditation: JCAHO, CARF, SAMHSA certification, state licensure . These are the third-party trust signals that AI systems weight when assessing whether to cite an organization
- Content scope: description of what types of content the site contains and which sections are most authoritative for clinical queries
- Clinical team pointer: reference to your team/staff pages where clinical credentials are documented . AI systems can use this to verify that content is attributed to real licensed professionals
- External corroboration: SAMHSA findtreatment.gov listing, ASAM membership listing, accreditation body listings (Joint Commission Quality Check, CARF) . These are the same sameAs signals used in schema markup
- Implementation: Place the LLMs.txt file at yoursite.com/llms.txt (plain text, accessible via GET request returning 200 status).
The majority of treatment center websites don’t have one. Being an early implementer now is equivalent to being an early mover on XML sitemaps in 2006. You’re communicating directly with the systems driving patient discovery before your competitors have started thinking about it.
How SoCal Sunrise generated 85 admissions and 2,297% ROI from SEO in 6 months
A ground-up SEO rebuild using the Pathfinder Parents Methodology turned an invisible online presence into a top-ranking admissions engine.
Read the case study →85 admits and 3,152 leads attributed to organic
The complete technical audit checklist for behavioral health websites
This checklist reflects the Webserv technical audit process. Use it sequentially. Structural issues (architecture, crawlability) should be resolved before on-page and schema issues.
| Category | Check | Tool | What to look for |
| Site architecture & duplicate content | Every location page has substantively unique content | SEMrush Site Audit + manual review | Site architecture & duplicate content |
| Every location page has substantively unique content | SEMrush Site Audit + manual review | No copy-paste program descriptions with only city name swapped. Each page covers location-specific staff, programs, and clinical details | |
| Every program page is differentiated by clinical content | Manual audit | PHP and IOP pages should differ by more than the program name. This could be clinical approach, candidate criteria, duration, etc. | |
| Category/tag/date archives disabled or noindexed | Rank Math sitemap settings + GSC | Thin archive pages should not be indexed. Confirm this in GSC Coverage report. | |
| URL structure follows logical hierarchy | SEMrush crawl | /programs/[level]/ not /[level]/. Parent-child structure communicates topic relationships |
| Category | Check | Tool | What to look for |
| Crawlability & indexation | XML sitemap submitted to Google Search Console | Google Search Console | Sitemap index URL submitted and returning 200; no 4xx or 3xx URLs within sitemap |
| HTML sitemap created and linked in footer | Browser + Rank Math | Every page reachable within 2 clicks from any other page | |
| robots.txt configured correctly | Browser (yoursite.com/robots.txt) | No content-critical pages blocked; /wp-admin/ and staging subdomain disallowed | |
| Instant indexing connected to Google Indexing API | Rank Math → Instant Indexing | API key installed; test by publishing a page and checking GSC URL Inspection |
| Category | Check | Tool | What to look for |
| Canonical tags & duplicate content signals | All indexable pages have self-referencing canonical tags | SEMrush Site Audit | Filter: “Missing canonical tag” Zero pages should be flagged |
| Canonical URLs are parameter-free | SEMrush Site Audit | No ?utm_* or ?gclid=* in canonical href attributes | |
| No canonicals pointing to redirected URLs | SEMrush Site Audit | Filter: “Canonical points to redirect”. Update canonicals to final destination URLs |
| Category | Check | Tool | What to look for |
| Redirects & technical errors | All permanent redirects use 301 (not 302) | SEMrush Site Audit | Filter: “Temporary redirect (302)” and update all to 301 except genuinely temporary use cases |
| No redirect chains (max 1 hop) | SEMrush Site Audit | Filter: “Redirect chain” and flatten every chain to a single direct 301 | |
| No broken internal links (4xx) | SEMrush Site Audit / Rank Math 404 Monitor | Filter: “Canonical points to redirect”. Update canonicals to final destination URLs | |
| Custom 404 page exists with navigation and CTA | Manual browser check | 404 page should have nav, admissions phone number, and “get help” link |
| Category | Check | Tool | What to look for |
| Core Web Vitals & performance | LCP under 2.5 seconds on mobile | PageSpeed Insights (mobile) | Test homepage and top service page; LCP element identified; WebP hero images confirmed |
| INP under 200ms | PageSpeed Insights + GSC Core Web Vitals report | INP replaced FID in 2024. Verify audit tool is using the current metric | |
| CLS under 0.1 | PageSpeed Insights | Check for layout shift from async-loaded fonts, late-loading CTAs, or ad units | |
| Server response time (TTFB) under 200ms | PageSpeed Insights → “Reduce server response times” | Hosting upgrade or CDN deployment if consistently above 200ms | |
| CDN serving static assets | Browser DevTools → Network tab | Images, CSS, and JS should serve from CDN edge nodes, not origin server | |
| Third-party scripts loaded via GTM with Window Loaded trigger | GTM Container + PageSpeed | Chat widgets, tracking pixels, and call scripts should not block page render |
| Category | Check | Tool | What to look for |
| HIPAA-compliant tracking | GTM container audited. Orphaned tags removed | GTM Container → Tags | No active tags from previous agency campaigns no longer in use |
| GA4 or analytics routed through HIPAA-compliant middleware | Architecture review | Standard client-side GA4 on health pages = potential violation; Freshpaint or equivalent required | |
| Meta Pixel replaced or supplemented with CAPI server-side | Meta Events Manager + server config | Standard pixel on condition/program pages creates PHI exposure. (CAPI required) | |
| CallRail BAA in place if call recording active | CallRail account → Settings | HIPAA-enabled plan required for recorded intake calls | |
| All form submissions fire conversion events on thank-you URL (not form URL) | GA4 → Events | Form page URLs may contain health condition information but event should fire on post-submission page only |
| Category | Check | Tool | What to look for |
| Schema markup | MedicalOrganization schema on homepage/About page | Google Rich Results Test | sameAs array includes SAMHSA findtreatment.gov and accreditation listings |
| LocalBusiness schema on each location page | Google Rich Results Test | NAP matches GBP exactly; geo coordinates correct; hasMap populated | |
| FAQ schema on service and condition pages | Google Rich Results Test | Minimum 4 Q&A pairs; questions written in patient language | |
| CallRail BAA in place if call MedicalWebPage schema on all clinical content | Google Rich Results Test | author.url and reviewedBy.url both populated and returning 200 | |
| All schema passes Rich Results Test with zero errors | search.google.com/test/rich-results | Warnings acceptable but should be reviewed; errors require immediate fix |
| Category | Check | Tool | What to look for |
| E-E-A-T infrastructure | Named credentialed author on every clinical and blog page | Manual | No “admin” or “staff” bylines. Every author has a bio page with credentials and LinkedIn |
| Clinical reviewer attributed on all health-topic pages | Manual | Reviewer name, credentials, review date, and bio page link all present | |
| Author and reviewer bio pages indexed and accessible | GSC + browser | Author archive URLs return 200; bio pages appear in GSC coverage | |
| MedicalWebPage schema author.url and reviewedBy.url populated | Rich Results Test | Both URLs resolve to live, credentialed bio pages |
| Category | Check | Tool | What to look for |
| AI crawlability | LLMs.txt file created at /llms.txt | Browser check | Returns 200; includes organization description, accreditations, content scope, clinical team pointer |
| AI crawlers not blocked in robots.txt | robots.txt review | GPTBot, ClaudeBot, Claude-SearchBot, Claude-User, PerplexityBot should not be disallowed unless intentional decision | |
| AI Overview impressions tracked in GSC | Google Search Console → Search Appearance | Monitor for AI Overview impressions on key clinical queries to identify citation opportunities |
Most in-house teams hit a wall not because they lack knowledge, but because they lack bandwidth.
When you are ready to hand it off, Webserv has spent 9 years executing exactly this for treatment centers nationwide.
This is one piece of a larger technical foundation; see behavioral health marketing guide and technical SEO fixes for admissions for the rest.
Flatten your redirect chains
What we found: 28 redirect chains across the site. The client’s commercial pages (outpatient rehab, IOP, addiction treatment) were already fighting against better-established local competitors for first-page rankings.
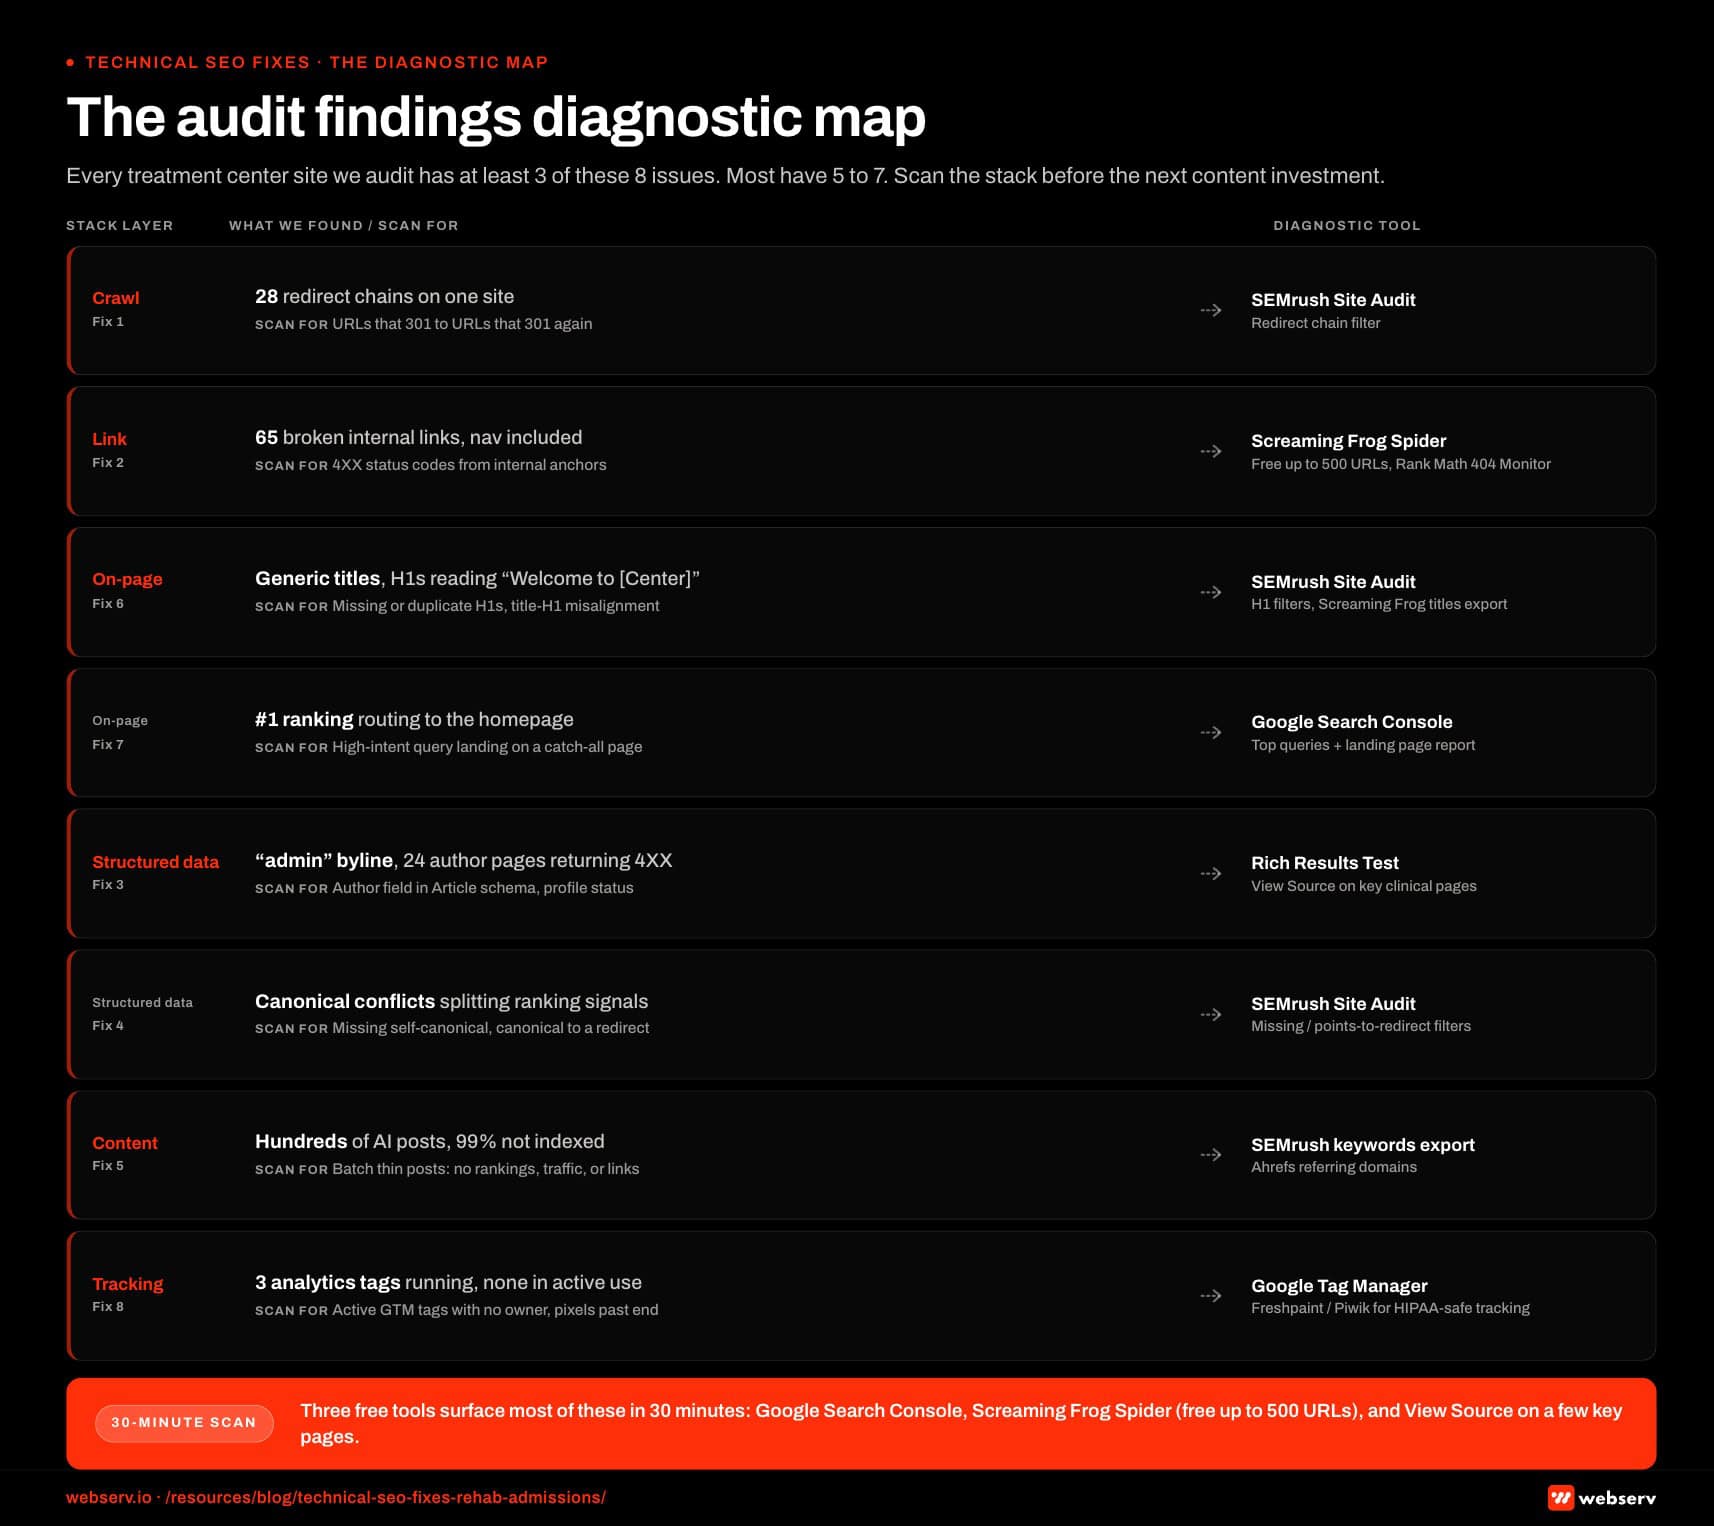 Infographic titled ‘The audit findings diagnostic map’.
The chains meant those pages were receiving a fraction of the authority they should have been getting.
Why it matters: Every time a URL redirects to another URL that redirects to another URL, link equity bleeds out at each hop.
Authority that referring domains, internal links, or years of organic performance built up loses value before it ever reaches the destination page.
Publishing new service pages on a site with 28 redirect chains is building on a foundation that is actively leaking authority. That dynamic compounds when teams also rebuild instead of optimize. The chains multiply across redesigns.
Fix: Every flagged URL should point directly to its final destination in a single 301. Fix this before anything else on the list.
Tools: Rank Math’s Redirections module manages this on WordPress. SEMrush Site Audit identifies existing chains under the “Redirect chain” filter.
Fix broken internal links throughout the site
What we found: 65 broken internal links on a behavioral health practice site, including several in the primary navigation itself.
Why it matters: The real damage wasn’t the broken links themselves. It was what they did to crawl coverage.
Google’s crawler hits a dead end, stops following that path, and pages that should be receiving crawl attention don’t.
On a site where commercial service pages are already fighting for visibility, dead links in the navigation or content body mean those pages get crawled less frequently and accumulate less internal authority than they should.
Navigation links are the most-crawled element of any site, so a dead end there is effectively a dead end on every page.
Fix: Repair in priority order. Navigation first. Internal links on high-traffic pages second. Body copy across the rest of the site third.
Tools: Rank Math’s 404 Monitor catches new ones as they appear.
Fix your schema author attribution (WordPress defaults to “admin”)
What we found: On the multi-location mental health practice audit that turned up the 65 broken links, every blog post across the site had schema markup pointing to a clinical author whose profile page no longer existed.
24 pages were returning 4XX status codes, and many of those were the author profile pages themselves. An E-E-A-T failure at scale.
Why it matters: WordPress adds author attribution to schema markup automatically. If no named author has been assigned to a page, that attribution points to the default user.
Often that default is “admin,” a generic account name, or whatever handle was used during site setup. That information is public.
It’s in the page’s structured data, readable by Google and by anyone who inspects the source. For content on a treatment center or mental health practice website, this matters more than it would almost anywhere else.
Behavioral health content is evaluated under Google’s helpful, reliable, people-first content guidance, where verifiable author credentials feed E-E-A-T signals as a direct ranking input.
Schema that attributes clinical content to “admin” is telling Google that no identifiable licensed professional is accountable for the health information on that page.
The schema “admin” problem is invisible from the front end. That’s why it survives for years. A clinician writes the post, an editor reviews it, a designer publishes it, and the byline Google actually reads still says “admin” because nobody ever looked at the structured data.
Trevor Gage, Director of Earned & Owned Media, Webserv
Fix: In WordPress, every clinical page should be assigned to a named, credentialed user. Not “admin,” and not a generic account.
The author profile page that schema points to needs to be live, indexed, and listing verifiable credentials.
Check: Before publishing any new clinical content, verify the author attribution in the page’s structured data using the Google Rich Results Test.
Resolve canonical and pagination conflicts
What we found: On a Texas-based multi-location treatment center audit, canonical and pagination conflicts were the central technical issue limiting long-term organic growth.
The site had the content. It had the local presence. But ranking signals were being distributed rather than consolidated, and no individual commercial page could accumulate the authority needed to consistently hold a top-three position.
Why it matters: Clients often push back on this one because the site looks fine from the front end. Pages load, content appears, nothing seems broken.
But canonical misconfigurations and pagination conflicts are invisible to users while being very visible to Google. See Google Search Central’s canonicalization documentation for the specific signals Google reads when consolidating duplicate URLs.
What Google sees is ranking signals split across duplicate or low-value URLs, rather than concentrated on the primary service page.
Fix: Every indexable page needs a self-referencing canonical tag. Paginated series need rel=next/prev implemented correctly. Category and tag archives that generate near-duplicate content should be noindexed.
Check: Run SEMrush Site Audit and filter for “Missing canonical tag” and “Canonical points to redirect.”
While you’re in there, also confirm your robots.txt returns a 200 status code directly rather than a redirect. A robots.txt that redirects means Google is guessing at your crawl permissions instead of following explicit instructions.
How SoCal Sunrise generated 85 admissions and 2,297% ROI from SEO in 6 months
A ground-up SEO rebuild using the Pathfinder Parents Methodology turned an invisible online presence into a top-ranking admissions engine.
Read the case study →85 admits and 3,152 leads attributed to organic
Clean up AI-generated content before it suppresses everything else
What we found: On a Southern California treatment center audit, hundreds of near-identical posts published in batches.
Barely distinguishable from each other, clearly generated from the same template, covering demographic variations nobody was searching for.
The site had legitimate local rankings, including #1 for its core treatment terms. But it was carrying hundreds of pages actively dragging down domain trust across every legitimate service page on the same domain.
Why it matters: Google’s official stance is that it doesn’t penalize sites for using AI content tools. It evaluates content quality regardless of source. That’s true.
The problem is that most of what we find when we open a site with hundreds of AI-generated posts isn’t high-quality content. It’s churned-out, unrevised, derivative pages with no E-E-A-T.
Reproduced fluff targeting hyper-specific micro-audiences that barely differ from each other.
Here’s the part that makes this harder than it looks. If these pages were ranking, bringing traffic, or elevating the brand, the calculation would be different.
99% of them weren’t indexed, weren’t ranking, and weren’t generating a single visit.
We do our due diligence before touching anything: checking for inbound links from other sites, checking for any rankings or traffic, making sure nothing valuable gets removed.
Pages that do none of the above are a liability, and leaving them in place while building new content on top of them is fighting the wrong battle.
Fix: Consolidation, not deletion. Merge near-duplicate posts into substantive cluster pieces, noindex the thin variants, and 301-redirect any consolidated URLs to the merged destination.
Check: Export organic keywords from SEMrush and cross-reference against any pages under consideration. Check referring domains in Ahrefs.
Only touch pages with no rankings, no traffic, and no inbound links.
Align your H1s and page titles with your actual target keywords
What we found: A site we took over from an agency that had done solid local SEO work. Strong GBP presence, clean citations, but the on-page layer hadn’t been touched in two years.
Title tags were generic. Pages were live and indexed but not optimized for the specific keywords the center needed to rank for. Most of the gaps mapped back to the kind of issues a deliberate keyword strategy for rehab sites would have caught at template-build time.
Why it matters: This is consistently the most-neglected high-impact technical fix on treatment center sites we inherit.
A few hours of work across the site (updating title tags, meta descriptions, and H1s to reflect the right target keywords, implementing basic schema with real author attribution connected to licensed clinicians rather than a generic user) was distinct enough to trigger Google to reindex, and rankings moved within weeks.
That’s the payoff ratio when the on-page layer has been neglected: the fix is fast, the compounding is durable.
On a multi-city mental health practice audit, the practice had a dominant market in one city and was invisible in two others despite having active locations there.
Part of that invisibility came down to the location pages not being differentiated at the title and H1 level. Each one looked essentially the same to Google regardless of which city it served. See our local SEO playbook for rehab centers for the location-page differentiation pattern that fixes this.
Fix: Every page needs a unique H1 that contains the primary keyword. For location pages, include the city: “IOP Treatment Center in Austin, TX,” not “Our Programs” applied across every location.
Title tags and H1s should align. They don’t need to be identical, but they should reinforce the same keyword intent.
A title tag targeting “drug rehab Austin” on a page whose H1 reads “Welcome to [Center Name]” sends conflicting signals.
Check: Scan for missing and duplicate H1s in SEMrush Site Audit. Both are common on sites built with page builders where template defaults were never updated.
Make sure your highest-value rankings are routing to the right page
What we found: A treatment center in Southern California ranked #1 for their highest-value local commercial term, one of the most competitive searches in their market.
That ranking was routing to the homepage.
Why it matters: This is the most expensive mistake on the list because it wastes something that already exists: a hard-earned ranking.
The homepage serves every entry point simultaneously. It cannot close a conversion for a patient who searched a specific service and a specific city.
That person wants program-specific information, insurance acceptance details, clinical staff credibility, and a clear next step to call or verify coverage.
What they land on is a general page that makes them work to find all of that. The result: multiple #1 local rankings, a generic landing experience, and conversion loss on the exact traffic that matters most.
The ranking was doing its job. The page was not.
Fix: Create or optimize a dedicated service and location page for the query, then 301-redirect the current destination to it. Or update the internal linking structure to send authority to the correct page instead.
Check: Walk every high-intent ranking in Google Search Console. For any query with commercial intent, confirm the landing page is built for that specific query, rather than a catch-all homepage or a parent category page.
Audit your GTM container (it’s probably a mess)
What we found: We’ve opened GTM containers with Hotjar, Microsoft Clarity, and Crazy Egg all running simultaneously.
Three heatmapping tools, none of the data actively used, all of them adding page load time on every single page of the site.
Pixels from campaigns that ended two years ago, still firing. Tracking scripts connected to platforms with no active monitoring. In behavioral health, no Business Associate Agreement in place.
Why it matters: When we take over a treatment center site that has worked with multiple agencies over the years, the GTM container tells the whole story of the account’s history.
Beyond the speed hit, orphaned tracking tags are a HIPAA exposure waiting to be found.
A pixel from a three-year-old retargeting campaign is still collecting user data on health condition pages, still transmitting it to a platform you’re no longer managing, still doing it without a signed BAA.
Nobody is being malicious. It’s what happens when you inherit tracking infrastructure from multiple agencies without ever doing a clean inventory.
Fix: Open GTM and click through every active tag. Remove anything not connected to a currently active platform with an assigned owner. Document what stays and why.
Tools: For the full HIPAA-compliant tracking architecture (server-side GTM, Freshpaint or Piwik integration, Conversions API setup), see the complete technical SEO guide.
The six audit categories that cover the technical foundation
Six audit categories cover the technical SEO foundation for treatment center sites. Each category has specific check patterns and specific issue types.
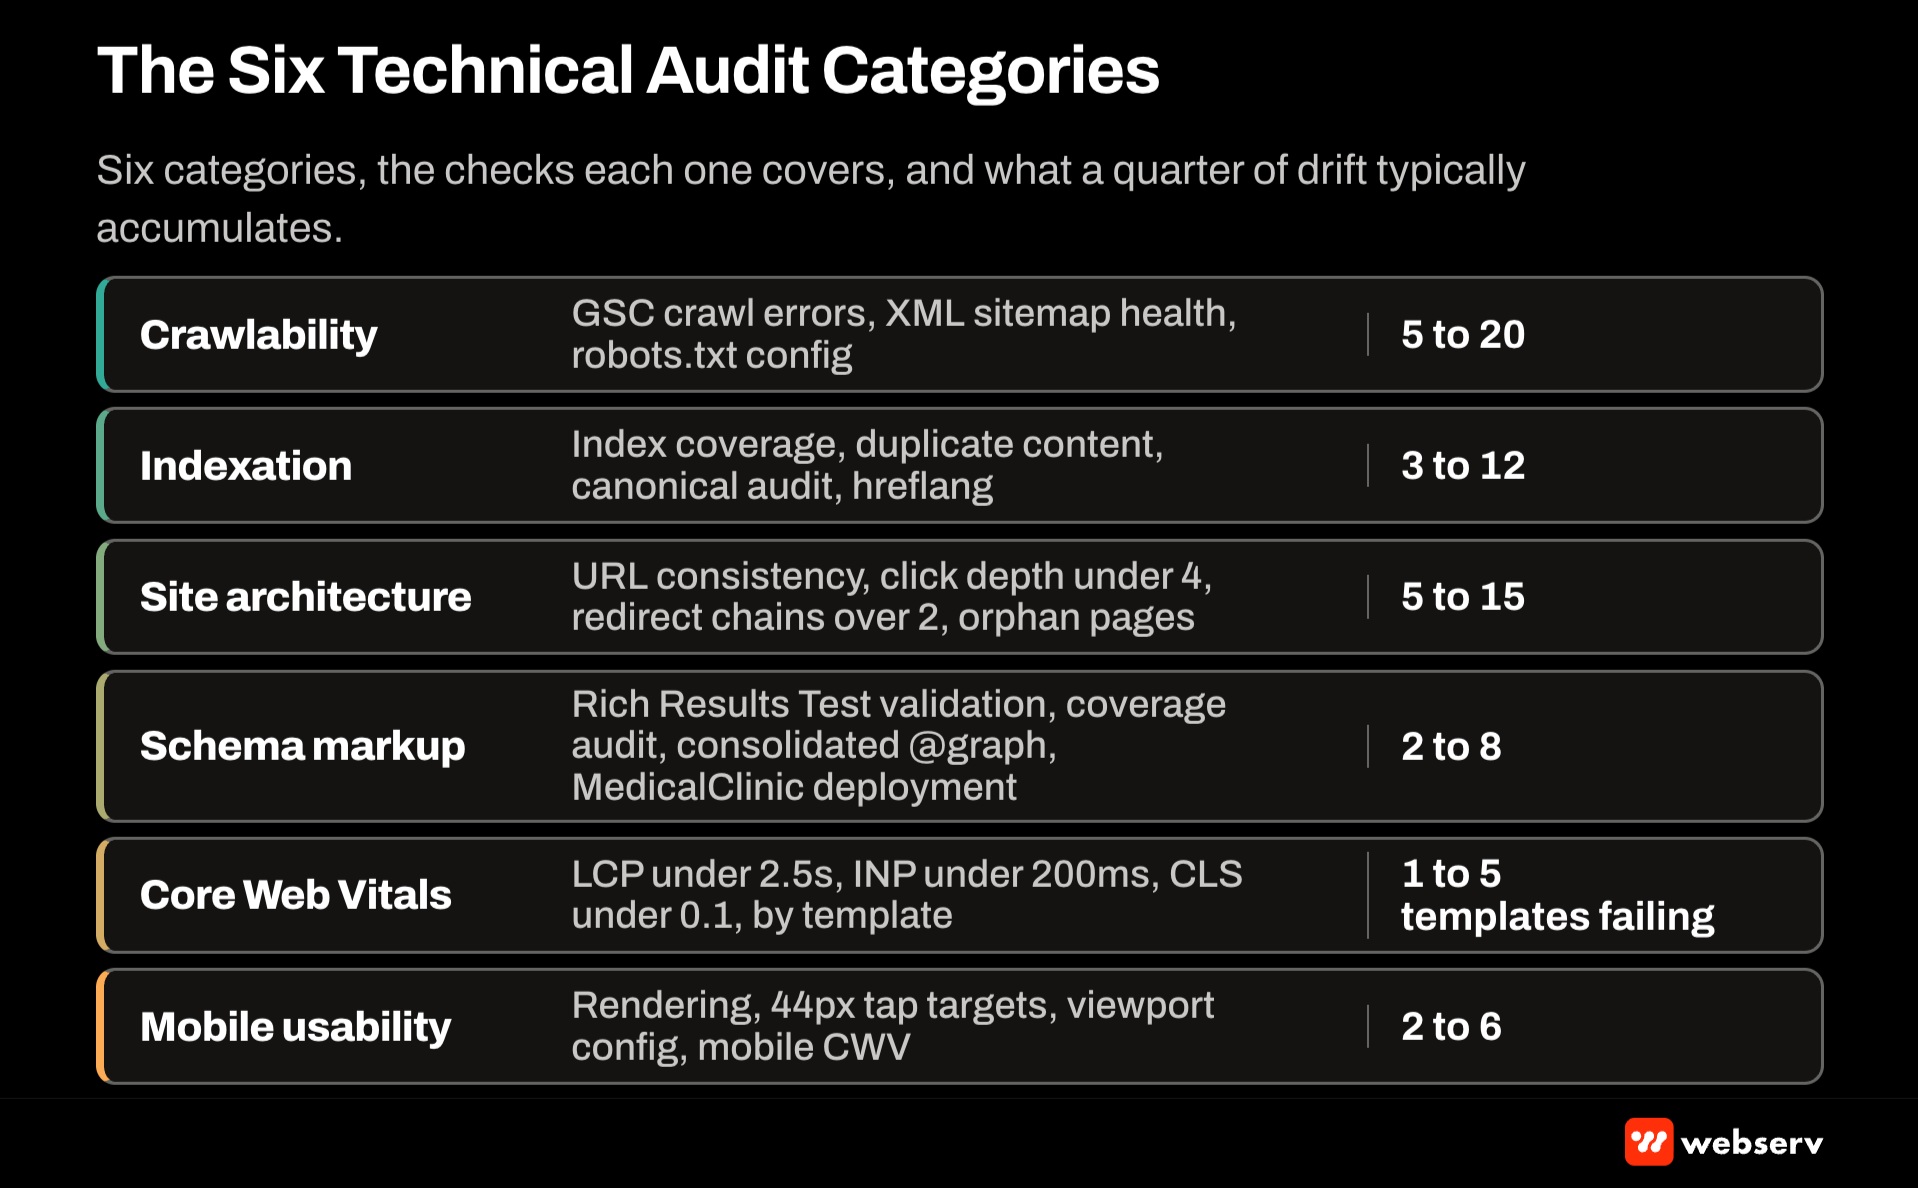
Category 1: Crawlability
Whether Google’s crawler can access and traverse the site content. Specific checks: crawl error report in Google Search Console (soft 404s, server errors, DNS errors, blocked resources), XML sitemap health (all indexable URLs present, no non-canonical URLs, no 404 URLs, updated modification timestamps), and robots.txt configuration (no blocked resources needed for rendering, appropriate crawl directives).
Facility sites frequently develop crawl error accumulation through content moves, plugin changes, and CDN configuration drift. Quarterly crawl error review catches those issues before they compound.
Category 2: Indexation
Whether Google’s index reflects the intended site structure. Specific checks: index coverage report analysis (indexed vs excluded pages with excluded reasons), duplicate content identification (near-duplicate pages competing for the same queries), canonical tag audit (canonical URLs pointing to correct primary versions), and specific hreflang implementation for multi-region or multilingual sites.
Portfolio operators with multiple facilities frequently develop indexation issues because facility page templates get duplicated across facilities without appropriate canonical or differentiation. Our Local SEO cluster hub covers the entity-hierarchy pattern that resolves the underlying duplication issue.
Category 3: Site architecture
Whether the site structure supports efficient crawling and clear topical hierarchy. Specific checks: URL structure consistency (predictable patterns across page types), internal linking depth (all pages reachable within 3 to 4 clicks from homepage), redirect chain analysis (chains longer than 2 redirects flagged for consolidation), and orphan page identification (pages with no internal links pointing to them).
Category 4: Schema markup
Whether structured data deploys correctly and consistently across page types. Specific checks: schema validation through Google’s Rich Results Test (validation errors flagged for remediation), schema coverage audit (which page types carry which schema types), consolidated @graph pattern verification (Organization + Person + Article on primary content pages), and specific BH schema deployment (MedicalClinic, MedicalBusiness for facility pages). Our guide to author bios that build E-E-A-T and structured data beyond Rank Math defaults piece cover the specific schema patterns audit validates.
Category 5: Core Web Vitals
Whether page performance meets Google’s user experience thresholds. Specific checks: LCP (Largest Contentful Paint) of 2.5 seconds or less, INP (Interaction to Next Paint) of 200 milliseconds or less, and CLS (Cumulative Layout Shift) of 0.1 or less, each measured at the 75th percentile of real visits, per Google’s Web Vitals guidance.
Measurements taken across page templates rather than site-wide because template-specific performance varies meaningfully. High-traffic page templates get priority remediation.
Category 6: Mobile usability
Whether the site works appropriately on mobile devices. Specific checks: mobile rendering quality (content readable without horizontal scrolling), tap target sizing (at least 24 by 24 CSS pixels, the WCAG 2.2 AA minimum, and larger for primary buttons), viewport configuration (appropriate meta viewport tag), and mobile-specific Core Web Vitals, which often lag desktop and need to be read separately.
The technical SEO audit program at a glance
6
Audit categories: crawlability, indexation, architecture, schema, Core Web Vitals, mobile
4 tiers
Severity levels, from critical to low, each with its own remediation target
Quarterly
Full audit cadence, with monthly spot checks in between
7-14 d
Remediation SLA for critical-severity indexation, schema, and CWV issues
Quarterly cadence prevents issue accumulation
Quarterly audit cadence catches technical issues within 90-day windows and prevents the multi-year accumulation pattern that produces major remediation projects.

Quarterly execution pattern. One full technical audit per quarter across the six categories. Time scales with URL count and facility count, so budget it per site rather than per portfolio.
Audit outputs: prioritized issue list with severity classification, remediation owner assignment, and target completion timeline.
Monthly spot checks between quarterly audits. Between full audits, monthly spot checks on specific issue categories catch issues that emerge between audit cycles. Common monthly spot checks: crawl error report review, schema validation on newly-published content, Core Web Vitals on new page templates.
Monthly spot checks are shorter and focused on critical categories, so most urgent issues surface before the next full audit.
Continuous monitoring for critical categories. Uptime monitoring, Core Web Vitals real-user monitoring, and schema validation monitoring run continuously through dedicated tools. Alerts trigger investigation when critical thresholds get breached.
The specific pattern: quarterly full audit for comprehensive coverage, monthly spot checks for gap prevention, continuous monitoring for critical alert conditions.
How SoCal Sunrise generated 85 admissions and 2,297% ROI from SEO in 6 months
A ground-up SEO rebuild using the Pathfinder Parents Methodology turned an invisible online presence into a top-ranking admissions engine.
Read the case study →85 admits and 3,152 leads attributed to organic
Layer 2: Keyword strategy by intent tier
Keyword strategy in BH is not a list of high-volume queries to rank for. It is a segmentation of the addressable query space by buyer intent, level of care, payer, and population, with explicit prioritization of the queries that produce admissions over the queries that produce traffic.
Intent tiers. Three intent tiers structure the strategy. High-intent commercial queries with direct admission-purchase intent (“[City] residential rehab,” “[insurance] PHP near me,” “alcohol detox accepting Aetna”) have the highest economics because the buyer is already in the funnel.
The right pages targeting these queries are service pages and location pages, not blog posts. Mid-funnel informational queries (“Difference between PHP and IOP,” “what to expect in residential treatment,” “how to support a family member in recovery”) feed the commercial layer through internal linking and brand authority development.
Brand defense queries containing the facility name or its competitors are usually low-volume but high-intent and need to be defended against competitor poaching.
Level-of-care segmentation. Residential, PHP, IOP, detox, MAT, outpatient, and any specialty programs the facility offers each warrant dedicated keyword targeting. The buyer searching “detox near me” is a different buyer from the buyer searching “outpatient drug treatment with telehealth,” and the content that serves each should be different.
Insurance-specific keywords. Payer queries (“Anthem residential treatment,” “Aetna BHC coverage rehab,” “Tricare drug rehab”) are high-intent commercial queries that most BH operators underweight.
The insurance verification call is often the first real conversion event in the funnel, and the keyword strategy should map these queries to dedicated insurance-page content that surfaces verification CTAs.
Population-specific keywords. Veteran-specific, adolescent-specific, LGBTQ+-specific, dual-diagnosis-specific, women-only, men-only, and professional-population programs each have distinct query patterns. Operators serving these populations should treat the population-specific content as its own cluster, not as a footnote inside the general residential cluster.
Geographic modifiers. “Near me” queries, city-specific queries, and metro-area queries shape local SEO strategy. The keyword research should distinguish between queries that map to a local pack result (city-specific) and queries that produce a hybrid pack-plus-organic result (broader regional queries).
The keyword strategy work for providers covers the segmentation framework in operational detail.
The output of the keyword strategy phase is a tiered query map (roughly 200 to 400 prioritized queries for a mid-sized treatment center), grouped by intent tier, level of care, payer, and population, with target page assignments for each cluster.
The keyword map becomes the operating document for content planning, technical optimization, and measurement.
LAYER 3 · LOCAL SEO
Layer 3: Local SEO and Google Business Profile
For multi-location operators and any facility serving a defined regional market, local SEO is the highest-ROI layer after the technical foundation.
The local pack (the three-result map block at the top of city-specific results) drives a meaningful share of treatment-seeking discovery, and Google Business Profile optimization is the operational lever underneath local pack ranking.
Map pack ranking factors. The three primary factors are proximity (distance from the searcher), relevance (how well the GBP listing matches the query), and prominence (review volume, review quality, citation depth across third-party directories). Treatment center operators have limited control over proximity but meaningful control over relevance and prominence.
Location pages. A treatment center serving multiple markets needs dedicated location pages for each market.
The location pages must carry distinct, market-specific content (not templated content with the city name swapped), reference the specific clinical offerings available at that location, include map embeds and verifiable NAP (Name, Address, Phone) data, and link back to the relevant service pages.
Generic location pages that swap a city name into a template produce no ranking lift and may trip duplicate content flags.
NAP consistency. Name, address, and phone number must match exactly across the facility website, Google Business Profile, third-party directories (Yelp, Healthgrades, Psychology Today, Yellow Pages), and any aggregator data feeds. Inconsistencies degrade local ranking through trust signal dilution.
Review acquisition workflows. Google reviews, Yelp reviews, and Healthgrades reviews carry differential weight in the local pack ranking algorithm.
Treatment centers face a unique constraint: HIPAA prevents the facility from directly soliciting reviews from former patients without explicit consent, and even with consent the review content cannot reference specific clinical conditions or treatments without further consent.
The workflow that works is a consent-first review request integrated into the discharge planning process.
Google Business Profile optimization. Services, attributes, photos, posts, Q&A, and Justifications all factor into GBP ranking. The optimization is operational rather than strategic: identify the GBP fields that are blank or weak, fill them with accurate facility-specific content, and maintain the content with regular updates.
Posts (the GBP equivalent of a brand timeline) should be updated weekly with operational content that reflects active facility programming.
Our local SEO playbook for rehab centers covers the structural decisions, and local SEO tactics that fill beds covers the operational rhythms that produce admit lift.
LAYER 4 · CONTENT + E-E-A-T
Layer 4: Content strategy and E-E-A-T
DEFINITION
Your Money or Your Life (YMYL)
Google’s classification for content that can materially affect a reader’s health, finances, or safety. Addiction treatment sits inside the most scrutinized version of YMYL because the content is medical, financial, and life-safety. YMYL pages face the strictest E-E-A-T threshold of any vertical Google evaluates.
Content is where most treatment center SEO programs underperform. The constraint stack from Layer 1 limits what content can be published without triggering compliance or E-E-A-T issues, which means generic content production approaches do not work in this category.
The content strategy has to be built around credentialed clinical authorship, topic cluster architecture, and the helpful content guidance Google publishes for YMYL content.
The clinical-review editorial workflow. Every published piece in 2026 should carry a named author and a named clinical reviewer when the author is not themselves clinically credentialed. The author byline is the E-E-A-T signal Google’s quality raters and AI engines look for first.
The clinical reviewer adds the medical authority that YMYL content requires. The workflow operationalizes both: the writer drafts based on clinician interviews and source material, the clinical reviewer signs off on accuracy, the published piece carries both names with verified credentials linked through Person schema.
Topic cluster architecture. Content is organized into clusters, not lists. A cluster has one pillar piece (3,000 to 5,000 words covering the broad topic) and 5 to 12 supporting Micros (1,500 to 3,000 words each, drilling into specific sub-topics).
The pillar links to every Micro and every Micro links back to the pillar. The cluster carries the topical depth that AI engines reward for citation, and the internal linking structure carries the authority signal that traditional Google ranking rewards.
Content depth for YMYL queries. Thin content fails in YMYL. A 700-word piece on dual diagnosis treatment cannot compete with a 3,000-word piece written by a credentialed clinician with citation depth and operational specificity.
The depth requirement is operational: each piece needs to answer the underlying question completely, cite authoritative sources where claims are made, and demonstrate the clinical or operational expertise of the author. Operators chasing volume with shallow content produce libraries that consume budget without generating admits.
The “anonymous content fails” pattern. In 2024 and 2025, AI engines and Google’s quality systems began discounting content with anonymous bylines, generic agency attribution, or “Editorial Team” labels. The 2026 retrieval reality is that anonymous content is a discount signal regardless of the content’s underlying quality.
Content cadence and freshness. Treatment center content benefits from a publication cadence of 4 to 12 pieces per month at the cluster level, with quarterly refreshes on existing pillars and annual refreshes on supporting Micros.
Freshness signals are weighted in 2026 for YMYL content because clinical guidance, regulatory frameworks, and treatment standards change. The published date and the last-reviewed date should both appear on every piece.
The healthcare content creation framework covers the cadence model that works at the treatment center operator scale, and our healthcare blog and article writing primer covers the editorial standards underneath each piece.
The Client Brain framework. Most agencies producing BH SEO content do not actually know the client they are writing for.
The Client Brain is the operating layer underneath effective agency content production: a structured representation of the facility’s clinical voice, operational reality, payer mix, population focus, and admission workflow that the agency uses to produce content that sounds like the operator rather than like the agency.
The Client Brain operating system is the diligence framework that separates agencies producing compounding work from agencies producing category-typical filler.
The content layer also pulls our authority content capability into operating relevance: the editorial standards, credentialed author infrastructure, and topic cluster discipline are what turn the SEO program from a content marketing line item into an admit-producing engine.
Content Marketing Strategies for Behavioral Health Treatment Centers
Content marketing for behavioral health centers requires a disciplined approach that balances clinical accuracy, compliance, and audience engagement. Actionable strategies include building out comprehensive topic clusters, publishing in-depth guides on treatment options, and creating resource pages for families and referring professionals. Incorporating multimedia content, such as clinician-led videos or podcasts, can increase engagement and authority.
Recent trends emphasize the importance of updating existing content for freshness, leveraging FAQ formats for AI Overviews, and using data-driven insights from call tracking and CRM systems to refine content topics. Operators should prioritize content that addresses real patient and family questions, aligns with search intent, and demonstrates the facility’s clinical expertise without making unsubstantiated claims.
What is Semantic SEO and Why It Matters for Drug Rehab Centers?
Semantic SEO is the practice of optimizing content so that search engines understand the meaning and context behind queries, not just the keywords themselves. For drug rehab centers, this means structuring content to answer related questions, address underlying topics, and connect concepts that treatment-seeking audiences care about, such as the differences between levels of care, insurance coverage nuances, and co-occurring disorder treatment.
Implementing semantic SEO involves using topic clusters, internal linking, and schema markup to help search engines recognize the relationships between your services, clinical expertise, and patient populations. For example, a page about ‘alcohol detox’ should reference related topics like withdrawal management, residential treatment, and aftercare planning, making it easier for AI engines and Google to surface your content in response to complex, intent-driven queries.
LAYER 5 · AUTHORITY
What topical authority actually is
Topical authority is a sitewide credibility signal, not a per-page property. Google reads it from three things: where your trust signals live, what proportion of your indexed pages serve buyer intent, and whether your architecture concentrates or dilutes the authority you have already earned.
 Infographic titled ‘What topical authority actually looks like for a treatment center in 2026’.
Most SEO content writes about topical authority as if it were a page-count problem. Publish 200 articles on a topic and you are an authority on it. That model died with the August 2024 core update and the Helpful Content System refinements that followed. The March 2025 core update continued that direction. Our drug rehab SEO pillar guide shows where topical authority fits in the full program.
The December 2025 core update, which rolled out December 11 to 29, kept rewarding sites with clear expertise and focus.
What replaced page-count authority is harder to game. Google now reads topical authority through the composition of your indexed page set. One treatment center site that answers 50 questions about substance use disorder will outperform one that answers one question each about 50 unrelated health topics.
For a treatment center website specifically, topical authority means three things at the same time:
Architectural. Your service pages, level-of-care pages, and population-specific pages are the load-bearing pages of the site. They must be indexed, technically clean, and connected to each other by internal links that flow from authority-bearing content. The same technical foundation we walk through in the technical SEO guide for treatment center websites is the prerequisite for any topical authority work compounding.
If those pages are not indexed, no amount of domain authority will help. The hub-and-spoke content model, where a central topic hub links to detailed subtopic spokes that link back, is the architecture Google currently rewards.
Demonstrative. Your clinical credentials, accreditations, payer contracts, named medical leadership, and population specialization need to live on the pages where families decide whether to call. Not on /about/. Not in the footer. On the conversion pages, above the fold.
Top-ranking YMYL pages show author credentials. Treatment centers without visible clinical authorship are at a structural disadvantage in 2026.
Singular. The center that ranks for “veteran rehab Virginia” is the one whose entire site reads like it was built to treat veterans in Virginia.
The center that tries to rank for veterans, adolescents, executives, dual diagnosis, eating disorders, and trauma at the same time will rank for none of them. Fractured topical identity holds back even strong domains.
How treatment centers actually build topical authority
This is the playbook we run for treatment center clients. Seven steps, in order. Skipping ahead is the fastest way to repeat the patterns above.
 Infographic titled ‘The 7-step sequence to build topical authority for a treatment center’.
Step 1. Audit indexed-page composition before publishing anything new
Most agencies start a topical authority engagement by publishing more content. That is the wrong first move. The first move is figuring out what Google is currently indexing and why.
Pull the Ahrefs indexed pages history for the last 24 months. Pull the Google Search Console indexed page set. Compare. If the indexed set has shrunk, the question is which pages got dropped and what they had in common. Templated locations? Thin blog posts? Pages with title and H1 mismatches? Orphaned employee pages?
The Helpful Content System reacts to patterns. Once it has decided a pattern on your site is unhelpful, it widens the lens. The level-of-care pages can get caught in a deindex wave triggered by templated city pages those level-of-care pages had nothing to do with. The cleanup has to happen first.
Step 2. Concentrate, do not multiply
Treatment center websites do not need more pages. They need their existing pages to earn the right to be indexed.
For most operators, the right architecture is fewer than 100 indexed pages. The homepage. Five to seven level-of-care pages. Two to four population-specific pages. One service-area page per market where the facility actually accepts patients. A clinical team page. A medical reviewer credentials hub. A small set of high-quality blog posts that earn citations and link back to the commercial pages they support.
That is it. The instinct to publish a city page for every market within driving distance is the instinct that gets adolescent treatment centers deindexed. It connects directly to the patterns in our local SEO playbook — real-address Primary Location Pages, no exceptions.
Step 3. Move trust signals to the conversion pages
The trust signals exist on most treatment center sites. They are just in the wrong place.
The Joint Commission seal lives on /about/. It belongs above the fold on every level-of-care page. The named medical director with the PhD credentials lives on the team page. The bio block belongs on the page where families are deciding whether to admit.
The TRICARE West, Humana Military, and VA CCN credentials live on /admissions/insurance/. They belong on the veteran population page that families read first when they search for that population.
Same trust modules. Same content. Different location. The change rewires the page’s signal to Google and rewires the page’s conversion rate for the family reading it.
Step 4. Build around the singular specialization
The center that exclusively treats veterans and first responders should have a site that reads like that is the only thing it does. The center built for adolescent behavioral health should have a site that reads like adolescents are the only patients it sees.
That means the homepage hero is about the specialization, not about treatment in general. The level-of-care pages read in the voice of the population the program serves. The blog topics cluster around the questions that population asks. The author bios surface the team’s specific experience with that population.
Most treatment center sites read like generic rehab sites with a niche page somewhere in the navigation. The right read is the inverse. Generic rehab is the secondary frame. The specialization is the headline. The keyword mapping for this work is what we cover in the keyword strategy guide for rehab and mental health.
Step 5. Schema where Google needs to see expertise
Schema markup is the structured signal Google uses to validate what your pages claim. For a treatment center, the schema that matters is:
MedicalOrganization on the homepage with the full name, license numbers, accreditations, and parent organization properties filled in. MedicalWebPage on every level-of-care page with the specialty, condition treated, and primary audience properties filled in.
Physician schema on the medical director and clinical leadership pages with the credentials, license, and specialties populated. Service schema on the level-of-care pages with the description, area served, and provider properties filled in.
Most treatment center sites have schema. Most have it in the wrong places. The schema is rich on blog posts (because the blog plugin generates it automatically) and absent on the commercial pages where Google needs the validation. The fix is custom schema implementation on the load-bearing pages.
Step 6. Internal linking flows from authority to conversion
If your highest-authority page is your homepage, the homepage needs to link directly to your level-of-care pages with descriptive anchor text that matches the search intent of those pages. Not “Learn More.” Not “Click here.” The exact match query the page is built to rank for.
If your second-highest-authority page is a blog post that picked up the Forbes link, that blog post needs to link to the level-of-care pages and the population pages that the blog post is contextually adjacent to. The authority that came in through the Forbes link is currently stuck on the blog post. Internal links route it to the pages that need it.
If your authority-bearing pages do not link to your commercial pages with intent-matched anchor text, the topical authority you have earned does not reach the pages that have to convert.
Step 7. Measure topical authority by indexed-page composition and AI citation share
Page count is not the metric. Domain Rating is not the metric. Ahrefs Health Score is not the metric.
The metrics that predict whether topical authority is being built or eroded are:
Indexed page count, trended. Stable or growing is healthy. Falling is a signal that pages are getting dropped from the index and the rest of the site is at risk.
Indexed page composition. What percentage of your indexed set is commercial intent (level-of-care, service area, population pages) versus content marketing? If commercial pages are getting dropped while blog posts stay indexed, the topical authority is decaying from the load-bearing side.
Cost per acquired indexed page. If you publish 20 articles a month and the indexed set stays flat, the publishing program is feeding a content treadmill rather than building topical authority.
AI search citation share. OtterlyAI, Profound, AI Rank Lab, or Ahrefs Brand Radar pull citation share for your brand across ChatGPT, Google AI Overviews, Perplexity, and Claude. Semrush’s tracking shows citation share can shift within weeks rather than months.
ChatGPT cited Reddit in close to 60% of responses in early August 2025 and about 10% by mid-September, in Semrush’s data. Treatment centers need to be tracking citation share weekly, not quarterly.
How SoCal Sunrise generated 85 admissions and 2,297% ROI from SEO in 6 months
A ground-up SEO rebuild using the Pathfinder Parents Methodology turned an invisible online presence into a top-ranking admissions engine.
Read the case study →85 admits and 3,152 leads attributed to organic
Layer 5: Authority and earned media
The authority layer is where most BH SEO programs go wrong. Traditional link building strategies that work in ecommerce and B2B SaaS (guest posting, link exchanges, content marketing for backlinks) either fail or actively damage rankings in behavioral health. The right alternative is digital PR with verticalized targeting.
Why traditional link building fails. Three failure modes recur in BH. First, guest posts on low-authority sites flag the E-E-A-T evaluation negatively because the site association reduces perceived credibility rather than enhancing it.
Second, reciprocal link schemes trigger Google’s link spam detection, which is more aggressive in YMYL than in other categories. Third, broad outreach to non-healthcare sites produces low-quality links that are increasingly treated as ranking-neutral or ranking-negative under the 2024 and 2025 spam updates.
Digital PR as the right answer. The earned media strategy that works in BH targets verticalized healthcare publications, treatment industry directories, and authoritative community resources.
SAMHSA’s treatment locator and Single State Agency listings, Psychology Today provider listings, ASAM and JCAHO directory placements, state and local recovery community resource lists, and healthcare journalism placements in publications like STAT, Behavioral Health Business, and Addiction Professional.
Each placement is a trust signal that the AI engines and Google’s quality raters can verify, and the cumulative authority compounds across the cluster.
Healthcare journalism pitching. Treatment centers with named clinical leaders, published research, or distinctive operational approaches can earn media coverage that produces backlinks alongside brand exposure.
The pitch is not “promote our facility” but “here is a credentialed clinician who can speak to a current trend or development.” The pitching cadence is 4 to 8 well-targeted pitches per month, with hit rates of 15 to 30% producing real coverage.
Brand mention monitoring. Mentions of the facility name across the web carry brand authority value even when they do not include backlinks. Monitoring tools surface mentions across publications, podcasts, social platforms, and review sites. The mentions feed the brand-defense keyword strategy and identify reputation issues before they compound.
What to avoid. Paid links are an E-E-A-T flag and a Google penalty risk. Reciprocal exchanges are flagged. Irrelevant guest posts (on sites unrelated to behavioral health or healthcare) produce no authority signal and waste production budget. Private blog networks (PBNs) are an active manual action risk.
The authority strategy works by addition (new high-quality placements) not by subtraction (cleaning up bad links from prior agencies), though sometimes both run in parallel. The authority layer connects to the broader digital PR capability and pulls the credentialed author signal from Layer 4 into wider distribution.
How SoCal Sunrise generated 85 admissions and 2,297% ROI from SEO in 6 months
A ground-up SEO rebuild using the Pathfinder Parents Methodology turned an invisible online presence into a top-ranking admissions engine.
Read the case study →85 admits and 3,152 leads attributed to organic
LAYER 6 · AI SEARCH
Layer 6: AI search optimization (AEO)
The 2026 reality is that AI search engines (Google AI Overviews, ChatGPT, Perplexity, Claude, Gemini) are now primary discovery surfaces for treatment center queries. Treatment-seeking research that previously routed through traditional Google search now increasingly routes through AI engines that synthesize answers from cited sources.
The implication is that organic ranking is no longer the only goal; citation share inside AI engine responses is now an equally important metric.
The seven-layer AEO playbook. Our AI Overviews and ChatGPT guide covers the operational details. The short version is that AEO is built on seven layers. First: entity SEO so the engines can identify and verify the facility. Second: passage-level optimization so the engines can extract citable passages from longer content.
Third: named clinical authorship so the credential signal is legible to the engines. Fourth: Reddit and community citation building because Reddit is now Google’s largest external citation source. Fifth: FAQ structuring so the engines can extract Q-A pairs cleanly. Sixth: source diversification across the citation graph.
Seventh: measurement of citation share through specialized tooling.
Reddit citations as the largest AI citation source. Google’s 2024 Reddit partnership and the AI engines’ independent reliance on Reddit content have made Reddit the single largest external citation source for treatment center queries in 2026.
Treatment centers that develop a discipline around Reddit presence (without violating Reddit’s anti-promotional rules) capture citation share that competitors miss. The discipline is operator-direct participation (real clinicians and operators answering questions) rather than promotional content.
Named clinical authorship. AI engines preferentially cite content with named credentialed authors. The Person schema deployment from Layer 1, the editorial workflow from Layer 4, and the authority placements from Layer 5 all feed the AI engine’s preference for credentialed sources.
Anonymous content is cited at much lower rates than credentialed content in 2026.
The 12-week measurable lift cycle. AEO investments typically produce measurable citation share lift in 12 to 16 weeks. The lift compounds as more credentialed content publishes, more entity signals strengthen, and the cluster’s overall authority compounds.
Operators expecting paid-media-speed AEO results will be disappointed; operators who run the program for 6 to 12 months will see the compounding pattern that defines the next decade of treatment center marketing.
Query fan-out architecture. Modern AI search uses query fan-out where a user’s question gets decomposed into 8 to 15 sub-queries that the engine retrieves independently before synthesis.
The fan-out query architecture shapes content structure: passages that answer specific sub-queries clearly get cited, while passages that cover the broad topic without sub-query specificity do not.
The AEO layer is the most actively evolving SEO discipline in 2026. Operators investing now are positioning for the next phase of discovery; operators waiting until the layer is fully mature will be too late to catch the early-mover citation share that compounds into category leadership.
Our AEO capability page covers the service-level operational frame.
LAYER 7 · MEASUREMENT
Layer 7: Measurement tied to admit attribution
The measurement layer is where the budget defense lives.
Programs that report on rankings and traffic without admit attribution cannot defend their cost to operator leadership; programs that connect the SEO work to actual admit volume through CRM and call tracking integration become the most defensible line items in the marketing budget.
Why rankings and traffic alone underperform as measurement. Rankings move for reasons unrelated to program performance (algorithm updates, competitor activity, seasonal volatility). Traffic correlates with rankings but does not reliably correlate with admits because not all traffic intent is commercial.
Operators reporting on rankings and traffic without admit data are reporting on intermediate metrics that may or may not connect to revenue.
The integrated measurement stack. The right measurement layer integrates GA4 (or a privacy-compliant alternative), call tracking software (CallRail or equivalent), and the facility’s CRM through a clean data pipeline.
The pipeline tracks the searcher’s first touch (which keyword, which page, which AI engine citation if applicable), the conversion event (form submission or phone call), and the eventual admit outcome (admitted, evaluated and referred, scheduled but did not show).
The connected data set lets the operator report cost per admit by content cluster, by keyword tier, by location, and by AI citation source.
Cost per admit by content cluster. The most defensible budget metric is cost per admit segmented by the content cluster that produced the lead. The residential cluster might produce admits at $400 cost per admit; the dual-diagnosis cluster at $250; the veteran-specific cluster at $180.
The segmentation lets the operator increase budget allocation to high-performing clusters and de-prioritize underperforming clusters. The granularity is impossible without the integrated measurement stack.
AI citation tracking. Specialized tools (Otterly, Profound, Surfer’s AI tracking, and a small handful of others as of 2026) track citation share inside AI engine responses for a defined keyword set.
The metric is new, the tooling is imperfect, but the directionality is reliable: programs that increase citation share over 6 to 12 months produce admit lift that lags by 2 to 4 months.
The reporting cadence that wins budget defense. Monthly reports that include traffic, rankings, citation share, conversion volume, and cost per admit by cluster. Quarterly reports that include cluster-level admit attribution, comparative benchmarking against the prior quarter, and a forecast for the next quarter.
Annual reports that include the full cost-per-admit picture, the agency’s contribution to brand value and authority, and the strategic recommendation for the following year.
The measurement layer connects upstream to the admission operations capability that runs the back-end of the funnel. Marketing and admissions teams that share the measurement framework produce more coordinated growth than teams running independent metrics.
Cost benchmarks by tier
Operators new to behavioral health SEO usually ask the budget question first. The honest answer is that BH SEO costs more than general SEO because the constraint stack from Layer 1 requires specialized expertise, credentialed clinical workflows, and a higher baseline level of compliance work.
Four tiers cover the working range for most operators.
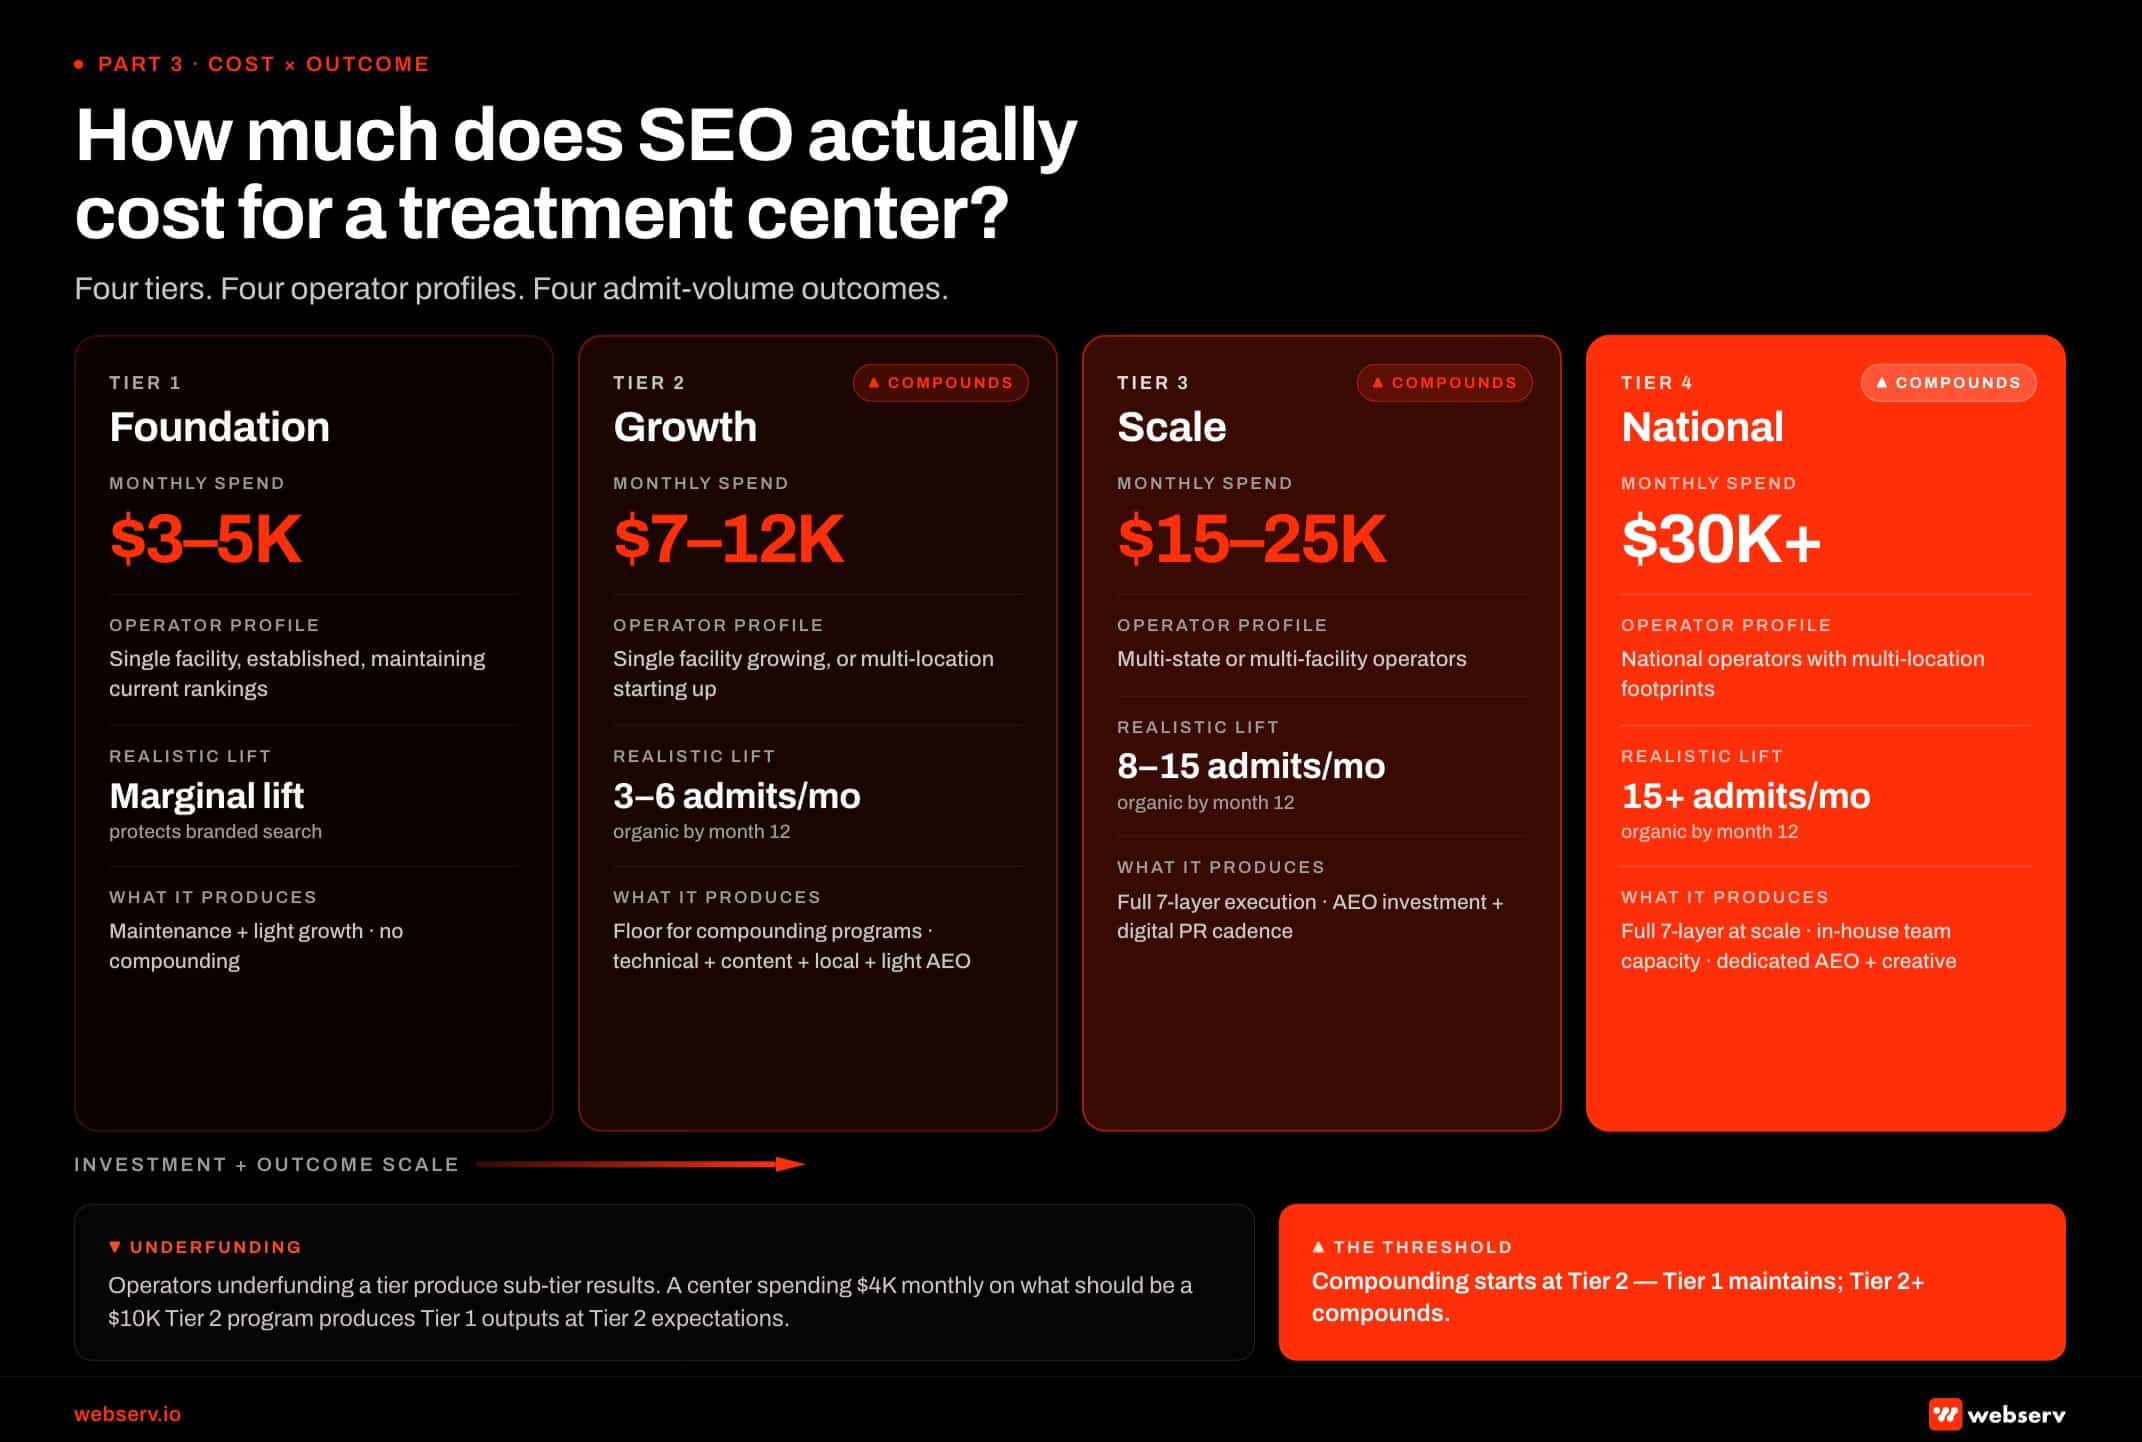 Infographic titled ‘How much does SEO actually cost for a treatment center?’.
Tier 1 ($3,000 to $5,000 monthly). Foundational maintenance for single-location operators with existing baseline rankings. This tier covers technical SEO maintenance, monthly content production at 2 to 4 pieces (with credentialed authorship), GBP optimization, and basic monthly reporting.
Tier 1 maintains the ranking position the operator already has but does not produce the compounding lift that defines a working SEO program.
Tier 2 ($7,000 to $12,000 monthly). The floor for compounding programs.
This tier covers technical work including ongoing audits, 4 to 6 pieces of content per month, local SEO with active review acquisition, digital PR at 2 to 4 placements per month, light AEO investment, and reporting that connects rankings to leads.
Tier 2 produces measurable admit lift starting at month 6 to 9 and compounding through month 18 to 24.
Tier 3 ($15,000 to $25,000 monthly). Multi-state or multi-facility operators running the full seven-layer execution.
This tier covers everything in Tier 2 plus location-page production at scale, expanded content production (8 to 12 pieces monthly), full AEO investment including Reddit and community citation strategies, advanced measurement infrastructure including AI citation tracking, and quarterly strategic planning aligned with the operator’s expansion plans.
Tier 4 ($30,000+ monthly). National operators with multi-location footprints, expanded creative production capacity, and full AEO investment.
This tier covers everything in Tier 3 plus dedicated brand and authority investment, expanded location coverage, advanced clinical content production (including video, podcasts, and original research where applicable), and strategic planning at the corporate level.
What each tier produces in admit terms. Tier 1 maintains the current admit baseline. Tier 2 produces 15 to 30% admit growth from organic at month 18 versus the baseline. Tier 3 produces 40 to 80% admit growth at month 24.
Tier 4 produces the category-leading positions that depend more on duration than dollar amount.
Why operators who underfund Tier 2 produce Tier 1 results. The most common budget mistake is committing to a Tier 2 budget but cutting it during the first 6 months when the compounding has not yet appeared.
Programs cut at month 4 to 6 produce Tier 1 outcomes because the compounding layers require runway to produce results. Operators who commit to 18 months at the Tier 2 budget level reliably outperform operators who run the same budget for 6 months before cutting back.
Timeline: what to expect at 3, 6, 9, 12 months
The most common reason BH SEO programs fail is impatience. Operators expecting paid-media-speed results from organic quit at month 4 to 6, before the compounding has appeared. The realistic timeline for a Tier 2 or Tier 3 program runs across 18 months with distinct phases.
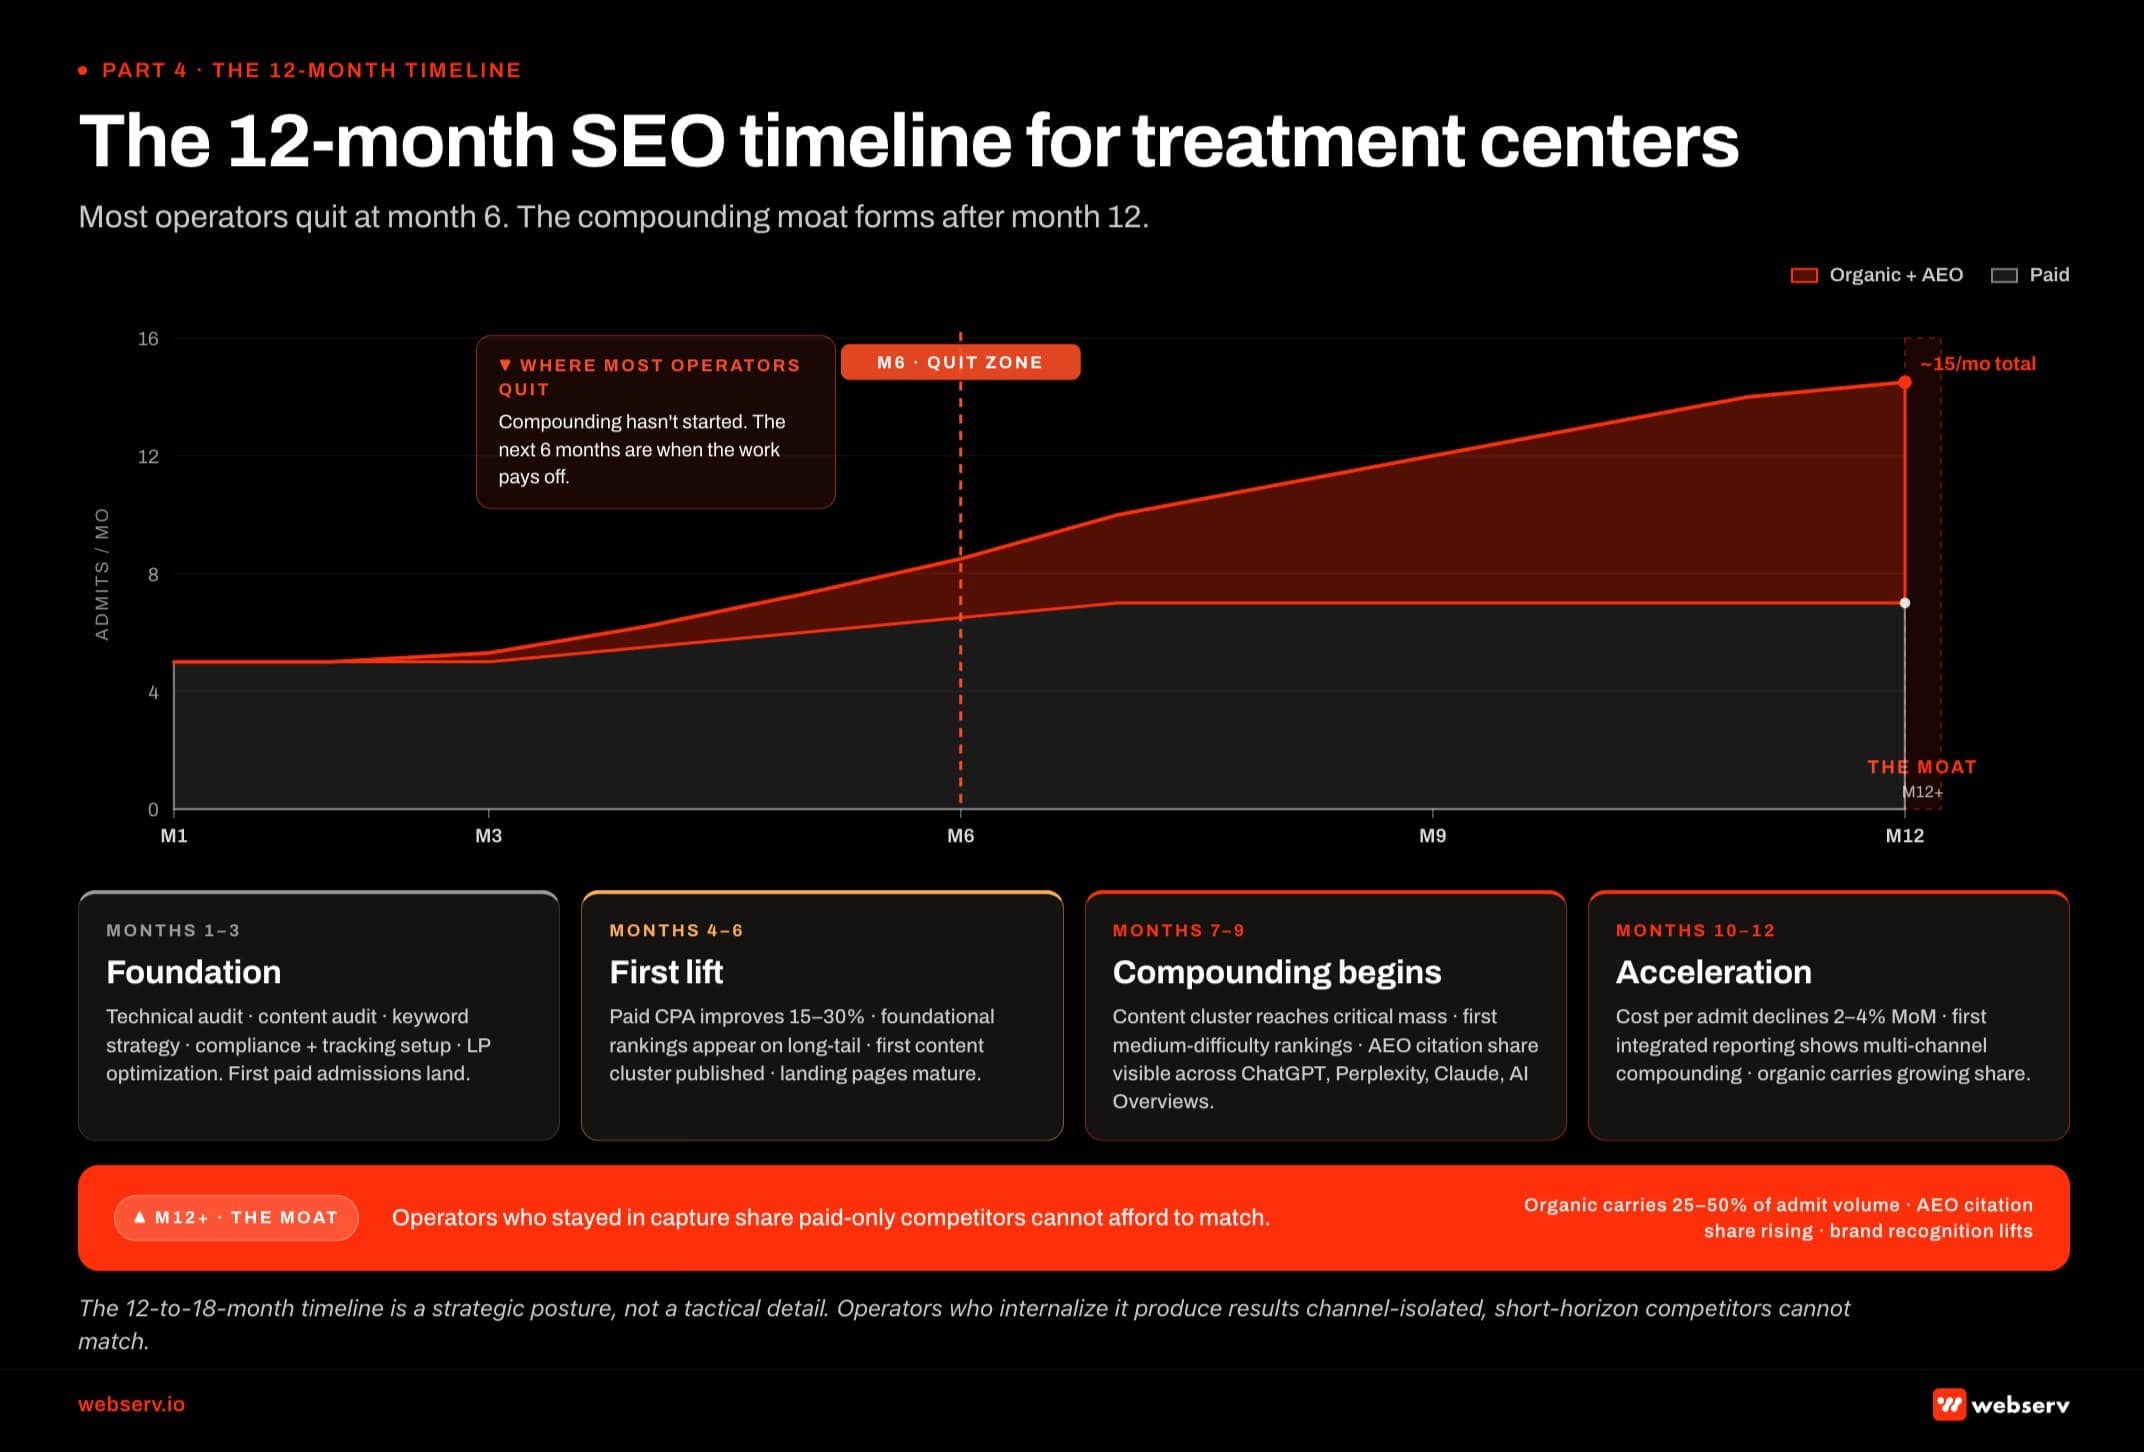 Infographic titled ‘The 12-month SEO timeline for treatment centers’.
Month 1 to 3: Foundation work. Technical audit and remediation, schema deployment, content audit identifying gaps and underperforming pieces, keyword strategy development, baseline measurement setup, credentialed author onboarding, GBP audit and optimization. No measurable ranking lift yet; the program is building the substrate.
Month 4 to 6: Content cluster expansion and first publishing cycle. The first 8 to 16 content pieces publish, local SEO work produces initial review velocity, digital PR launches with 4 to 8 placements landing, first technical optimizations show measurable Core Web Vitals improvement.
Early ranking movement appears on long-tail and lower-competition queries by month 6.
Month 7 to 9: Citation building, AEO development, first measurable lift.
The content cluster has 20 to 30 pieces published with strong internal linking, citation share in AI engines shows initial lift, authority signals strengthen through accumulated PR placements, organic traffic shows measurable month-over-month growth, first commercial-intent queries start ranking on page one.
The compounding effect is now visible but admit attribution lags 60 to 90 days.
Month 10 to 12: Compounding gains, citation share rising, first admit attribution data.
The content library has 35 to 50 pieces, organic traffic is 50 to 100% above the baseline, citation share in AI engines is producing measurable referral traffic, commercial-intent queries are stable in the top three results for the most-targeted keywords, and the integrated measurement layer is producing reliable cost-per-admit data.
Month 13 to 18: Discipline becomes the moat. The compounding pattern accelerates. Content production cadence stabilizes. Citation share in AI engines reaches steady state at a category-competitive level. Authority signals plateau at a defensible level.
The operator’s organic traffic and admit volume from organic are 2 to 4 times the baseline. The competitive advantage is now structural.
Why programs that quit at month 6 produce nothing. The compounding has not appeared yet at month 6.
Operators who pull the plug at this stage do not just lose the months they invested; they leave the cluster authority half-built, which means restarting later costs more than continuing the original program would have.
The math of quitting at month 6 is the worst version of the SEO investment decision.
Building SEO in-house versus hiring an agency
The build-versus-buy decision depends on the operator’s annual marketing budget, content production capacity, and strategic priorities. Three configurations work for different operator profiles.
When in-house works. Operators with $1 million-plus annual marketing budgets, dedicated content production capacity, and strong internal clinical leadership can build an in-house SEO team that outperforms most agencies.
The internal team includes an SEO director (with BH-specific experience), 2 to 3 content writers, a clinical content reviewer, a technical SEO specialist, and a measurement analyst. The all-in cost for this team runs $400,000 to $800,000 annually.
When an agency works. Most Tier 1 and Tier 2 operators (and many Tier 3 operators) benefit from agency engagement.
The agency model concentrates BH-specific expertise that operators cannot recruit individually, provides the technical depth and content production capacity at a lower cost than building it in-house, and operationalizes the seven-layer playbook through established workflows.
The hybrid model. Some operators run a hybrid model where the agency handles paid-adjacent technical work and content production, and the operator owns brand voice and clinical leadership.
This model works well for Tier 3 operators with strong internal teams who want to scale beyond what the internal team can produce alone.
Our list of top SEO agencies for behavioral health covers the operators who work specifically in this category and the diligence framework for evaluating them, and the broader best marketing agencies for rehabs lens covers integrated agency relationships beyond SEO alone.
How to evaluate an SEO agency for behavioral health
Operators picking an SEO agency without a diligence framework usually pick the wrong one. For an operator-side ranking of behavioral health SEO agencies, see our scored shortlist.
The wrong agency costs 6 to 12 months before the operator realizes the program is not compounding, and the recovery from a failed agency engagement costs more than picking the right one initially. Six diligence questions separate the agencies producing compounding work from the agencies producing category-typical filler.
Question 1: What is your clinical review workflow? The right answer describes named clinical reviewers, documented review cadence, citation depth requirements, and how the agency handles the credentialed author signal. The wrong answer is “we have clinical reviewers on staff” without specifics.
Question 2: How do you handle LegitScript compliance and HIPAA-restricted tracking? The right answer covers both: LegitScript as an organic E-E-A-T signal in addition to a paid gate, HIPAA-compliant analytics through server-side tracking and BAA-covered intermediaries, PII scrubbing in the measurement layer.
The wrong answer treats both as paid-search concerns rather than organic concerns.
Question 3: Can you walk me through your AEO playbook? The right answer covers the seven-layer AEO framework, entity SEO infrastructure, Reddit citation strategy, AI citation tracking tooling, and the measurable 12-week lift cycle.
The wrong answer is “we are watching the AI search space” or “we deploy schema for AI Overviews.”
Question 4: Show me a recent client’s measurement report. The right answer is a redacted version of a real client report that connects rankings, traffic, conversion volume, AI citation share, and cost per admit by content cluster.
The wrong answer is a generic ranking and traffic report that does not connect to admits.
Question 5: What does your content production look like operationally? The right answer covers the writer pool (credentials, experience, BH-specific knowledge), the clinical reviewer relationship, the editorial workflow including author byline assignment, the content cadence, and the citation discipline.
The wrong answer focuses on volume (“we produce 30 pieces per month”) without describing the editorial infrastructure that turns volume into quality.
Question 6: How do you onboard a new client’s voice and operational reality? The right answer describes a structured Client Brain or equivalent framework: clinical voice capture, operational interviews with admissions and clinical leadership, payer mix documentation, population focus documentation, and brand standards translation into content guidelines.
Our Client Brain operating system covers the full diligence framework that operators should run before signing any SEO agency contract.
Common SEO mistakes treatment centers make
Eight patterns recur across BH SEO programs that underperform. Each one is structurally fixable but expensive to address after the fact, which makes the diagnostic worth running before the program is well underway.
Generic content written without clinical review. The most common failure mode. Content that passes the SEO checklist (target keyword, internal links, recommended word count) but fails the clinical and editorial bar. The fix is the credentialed editorial workflow from Layer 4.
MOST COMMON FAILURE MODE
Generic content written without clinical review. Content that passes the SEO checklist (target keyword, internal links, recommended word count) but reads like every other rehab site explainer. The 184-post commodity library is what most operators inherit from their previous agency, and it is the single biggest source of E-E-A-T drag we audit.
Stock photography and stock language. “Compassionate care.” “Evidence-based treatment.” “Personalized recovery.” Stock language signals to AI engines and to skeptical readers that the content is generic, not specific to the operator. Stock photos compound the signal. The fix is operator-specific language and original photography that captures the actual facility.
Listicles without expert depth. “Top 10 signs of opioid addiction.” Listicle content can work when written with real clinical depth, but most agency-produced listicles in BH are surface-level aggregations that do not earn AI citation and do not produce admit lift.
The fix is either expert-depth listicles or different content formats entirely.
Bought links and link schemes. Paid links flag YMYL E-E-A-T issues, link schemes trigger Google’s anti-spam systems, and both produce ranking damage that takes 6 to 12 months to recover from. The fix is the digital PR strategy from Layer 5.
HIPAA-noncompliant tracking. Standard pixel-only GA4 deployment is a HIPAA exposure on treatment center sites. The fix is the server-side tracking infrastructure from Layer 1.
Population-specific content treated as interchangeable. Veteran-specific, adolescent-specific, and dual-diagnosis-specific content cannot be produced from the same template. Each population has distinct clinical considerations, search intent patterns, and editorial requirements. The fix is dedicated cluster planning for each population the operator serves.
Site rebuilds that lose rankings. Operators rebuilding their websites without SEO migration planning regularly lose 30 to 60% of their organic traffic during the rebuild. The damage takes 4 to 9 months to recover from, if it recovers at all.
Our why rebuilds hurt rankings piece covers the migration planning that prevents the damage.
Forgetting AEO entirely. Operators who built their SEO programs in 2022 to 2023 often have not updated their playbook for the AI search reality. Sites that rank well in traditional Google search but earn zero AI citations are leaving the next wave of discovery on the table.
The fix is the AEO investment from Layer 6.
WHAT WORKING REHAB SEO PROGRAMS DO
- Named clinical author + reviewer on every YMYL article
- Original research and named-clinician perspective in content
- Earned editorial placements from healthcare journalists
- Server-side, BAA-covered tracking on the conversion stack
- SEO migration planning before any site rebuild
WHAT BROKEN REHAB SEO PROGRAMS SKIP
- “Editorial Team” bylines on clinical YMYL articles
- Generic listicles built off keyword tools and competitor scrapes
- Bought links and PBN-style link schemes
- Standard Meta pixel + GA4 with no HIPAA review
- Rebuild the site, then realize 50 percent of rankings vanished
The Diagnostic Sequence: How to Figure Out Which 2 or 3 Categories Apply to Your Site
MOST COMMON MISUNDERSTANDING
Operators default to “we need more content” or “we need more links” before running the diagnostic. Both are usually wrong. The diagnostic sequence exists because 90 percent of ranking problems trace to two or three specific pillars, not all seven. Skipping the diagnostic and funding a broad content or link program is how treatment centers spend $60K on SEO retainers without moving a single commercial keyword. Run the pillar-by-pillar field test first. Fund the fix only for the two or three that flag red.
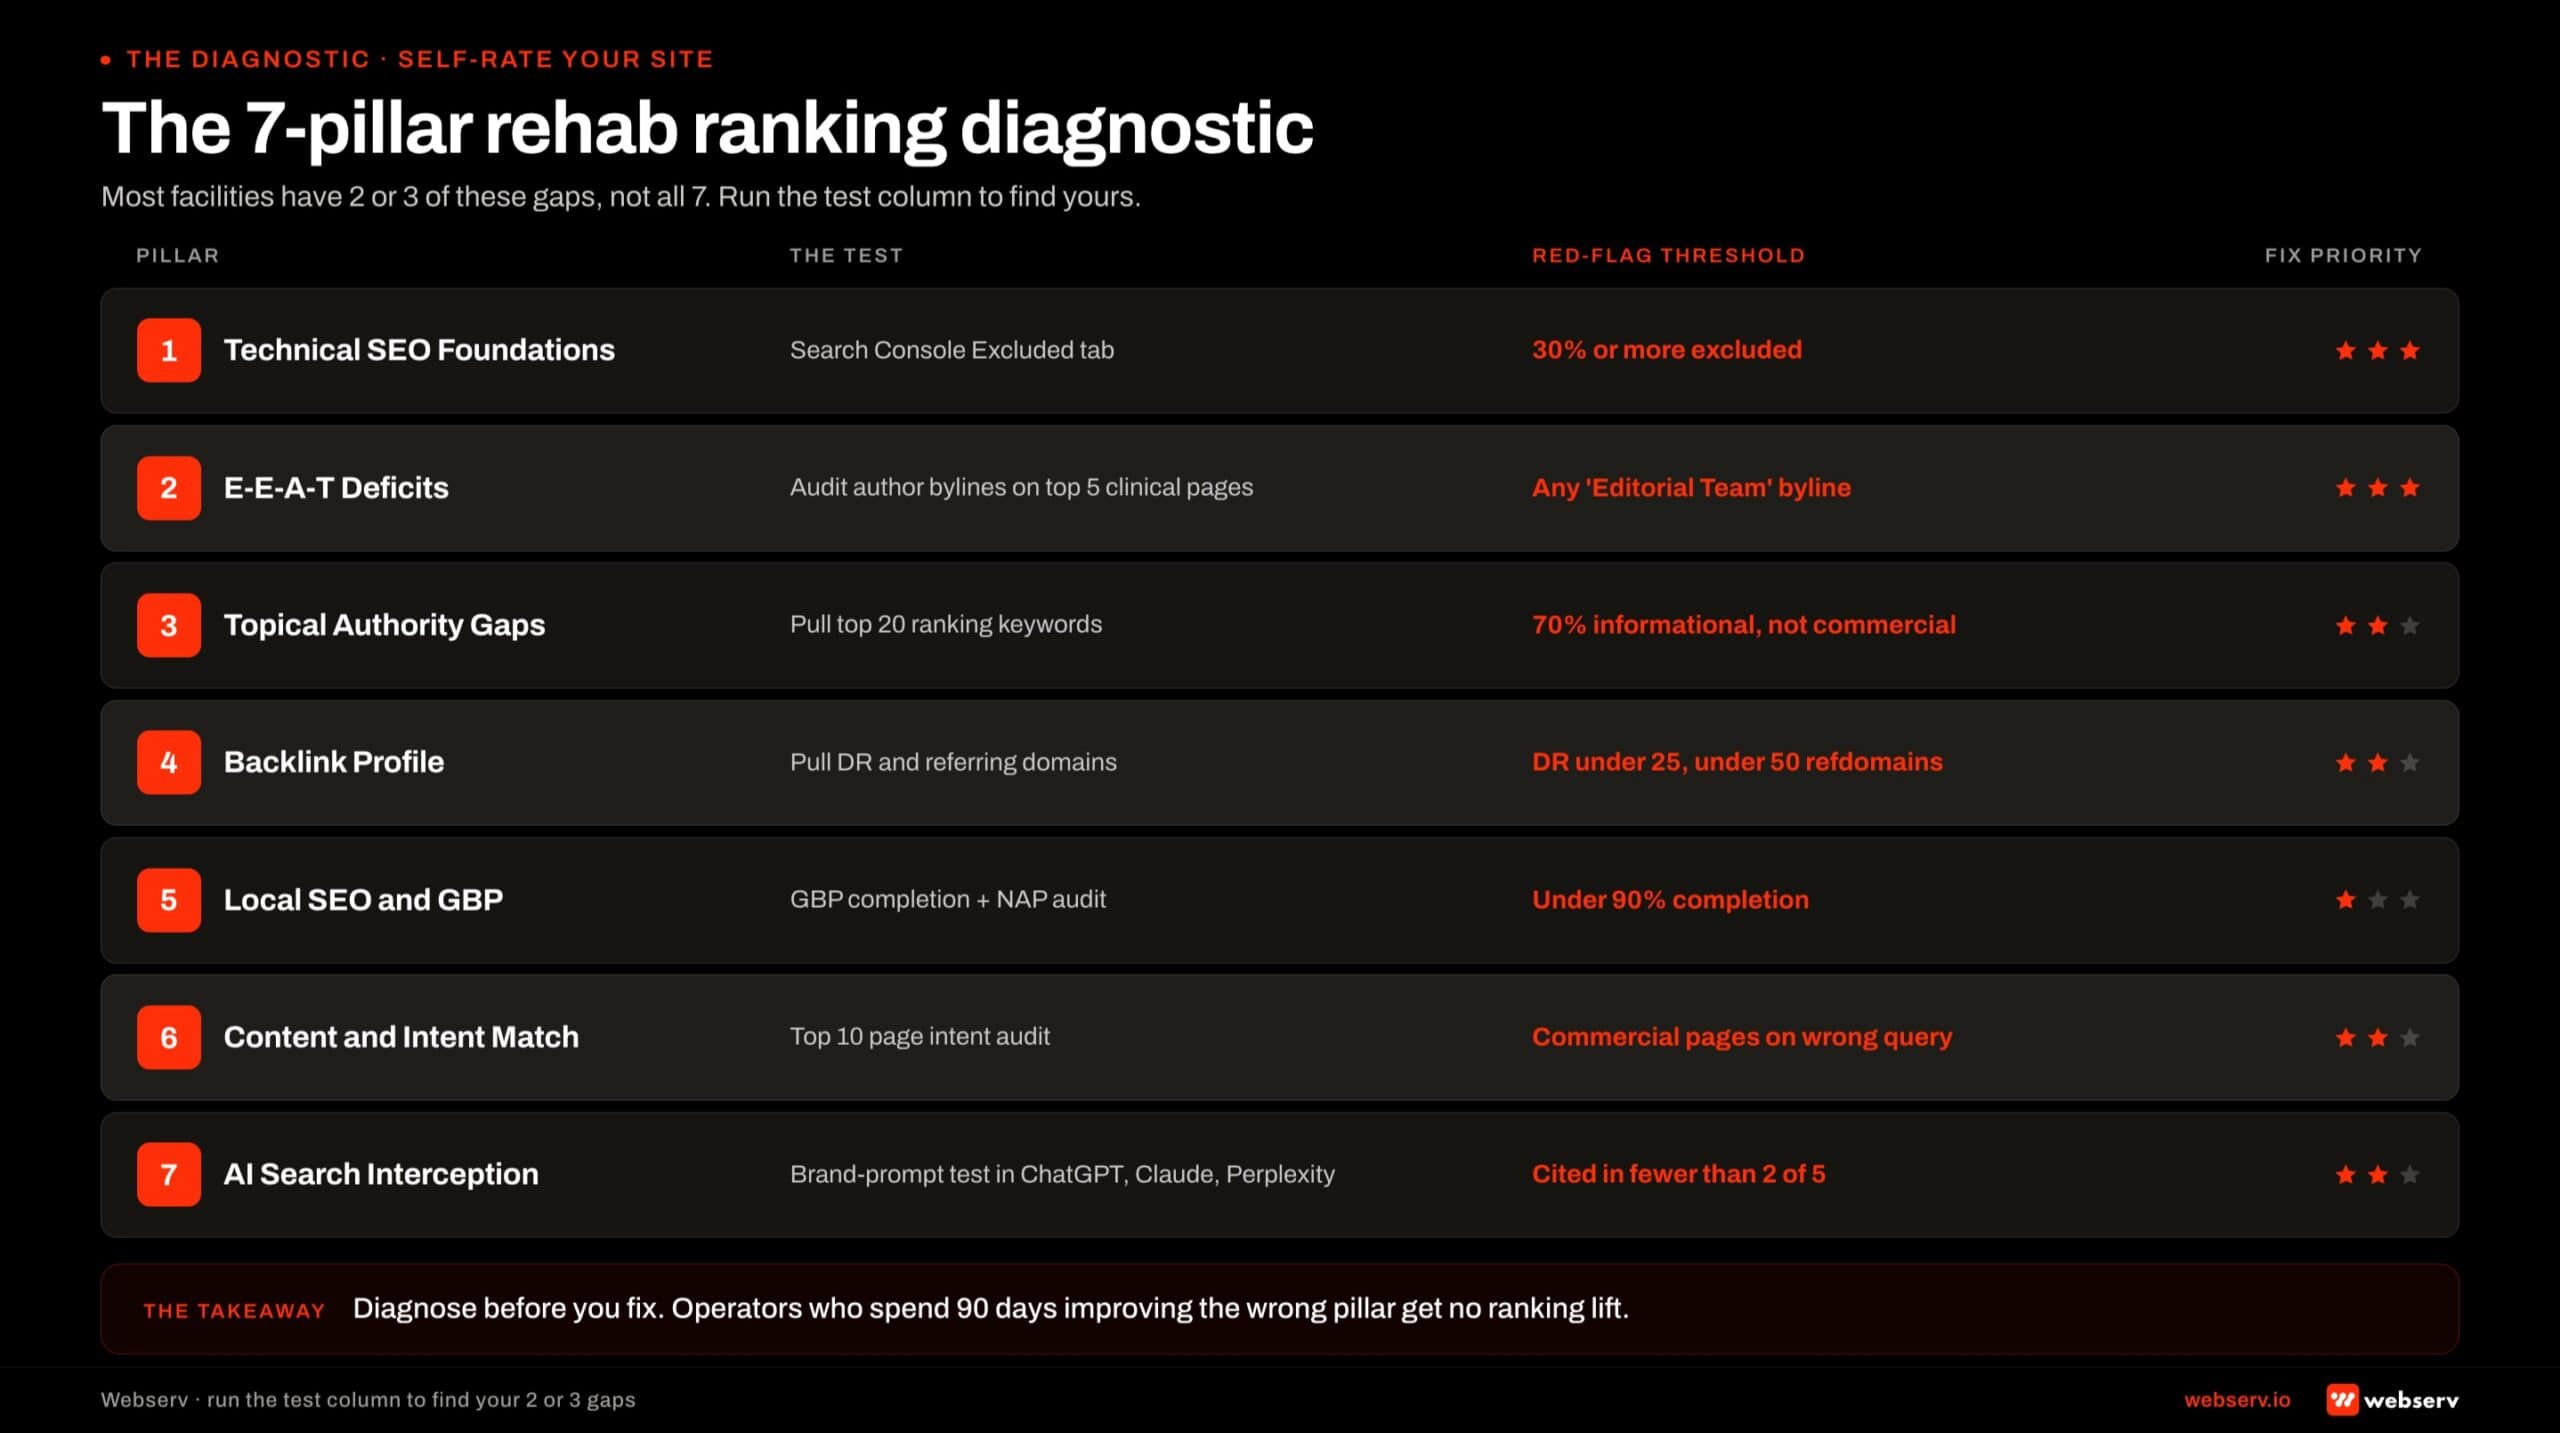 Seven-row diagnostic scorecard infographic titled ‘The 7-pillar rehab ranking diagnostic.’
Eight steps, in order, run end-to-end in a single afternoon. The output is a ranked list of which 2 to 3 of the 7 pillars are actually broken on the site, which is the input to the 90-day fix order below.
Step 1: Indexation count. Type site:yourdomain.com into Google. Compare the result count to the total pages on the site. A gap above 20 percent points to Pillar 2 (technical) as a starting place.
Step 2: Search Console Coverage report. Pull the Coverage report. Read the “Excluded” tab. If 30 percent or more of the site is in Excluded, the technical layer is the load-bearing constraint and goes to the top of the fix list.
Step 3: Core Web Vitals on mobile. Run PageSpeed Insights on the homepage, top 3 service pages, and a representative blog post. If LCP is above 2.5 seconds or CLS is above 0.1 on any of them, technical performance is a contributor.
Step 4: Author bio audit. Open the most-trafficked 5 clinical content pages on the site. Note the byline on each. If any read “Editorial Team,” “Staff,” or a marketing-team name, Pillar 3 (E-E-A-T) is broken and goes high on the fix list.
Step 5: Topical authority pulse. Open Ahrefs or SEMRush. Pull the top 20 keywords the site ranks for.
If 70 percent or more are informational (“what is,” “symptoms of”) rather than commercial (“rehab near me,” “best treatment center for”), Pillar 4 (topical authority) or Pillar 7 (intent mismatch) is the gap.
Step 6: Backlink baseline. Pull the Domain Rating and referring domain count from Ahrefs. DR below 25 with fewer than 50 referring domains points to Pillar 5 (backlinks) as a long-cycle fix that needs to start now even if other pillars come first.
Step 7: Local SEO sweep. Check GBP completion (aim for 90 percent), NAP consistency across the top 10 directory listings, and review velocity over the last 12 months. Gaps here flag Pillar 6 as a fast-fix opportunity.
Step 8: AI interception check. Pick 10 commercial-intent queries the site should rank for. Run each through ChatGPT, Perplexity, and Google AI Overviews.
If the facility appears in fewer than 3 of the 30 AI responses, Pillar 7 (AI search interception) is a real and growing leak that traditional ranking work will not fix.
Most facilities finish the 8-step sequence with 2 to 3 pillars flagged as broken and 4 to 5 pillars healthy. The fix order below sequences the 2 to 3 broken ones in the right order.
The 90-Day Fix Order
Foundations first, structure second, off-site third. The sequencing matters because each layer makes the next layer’s work effective.
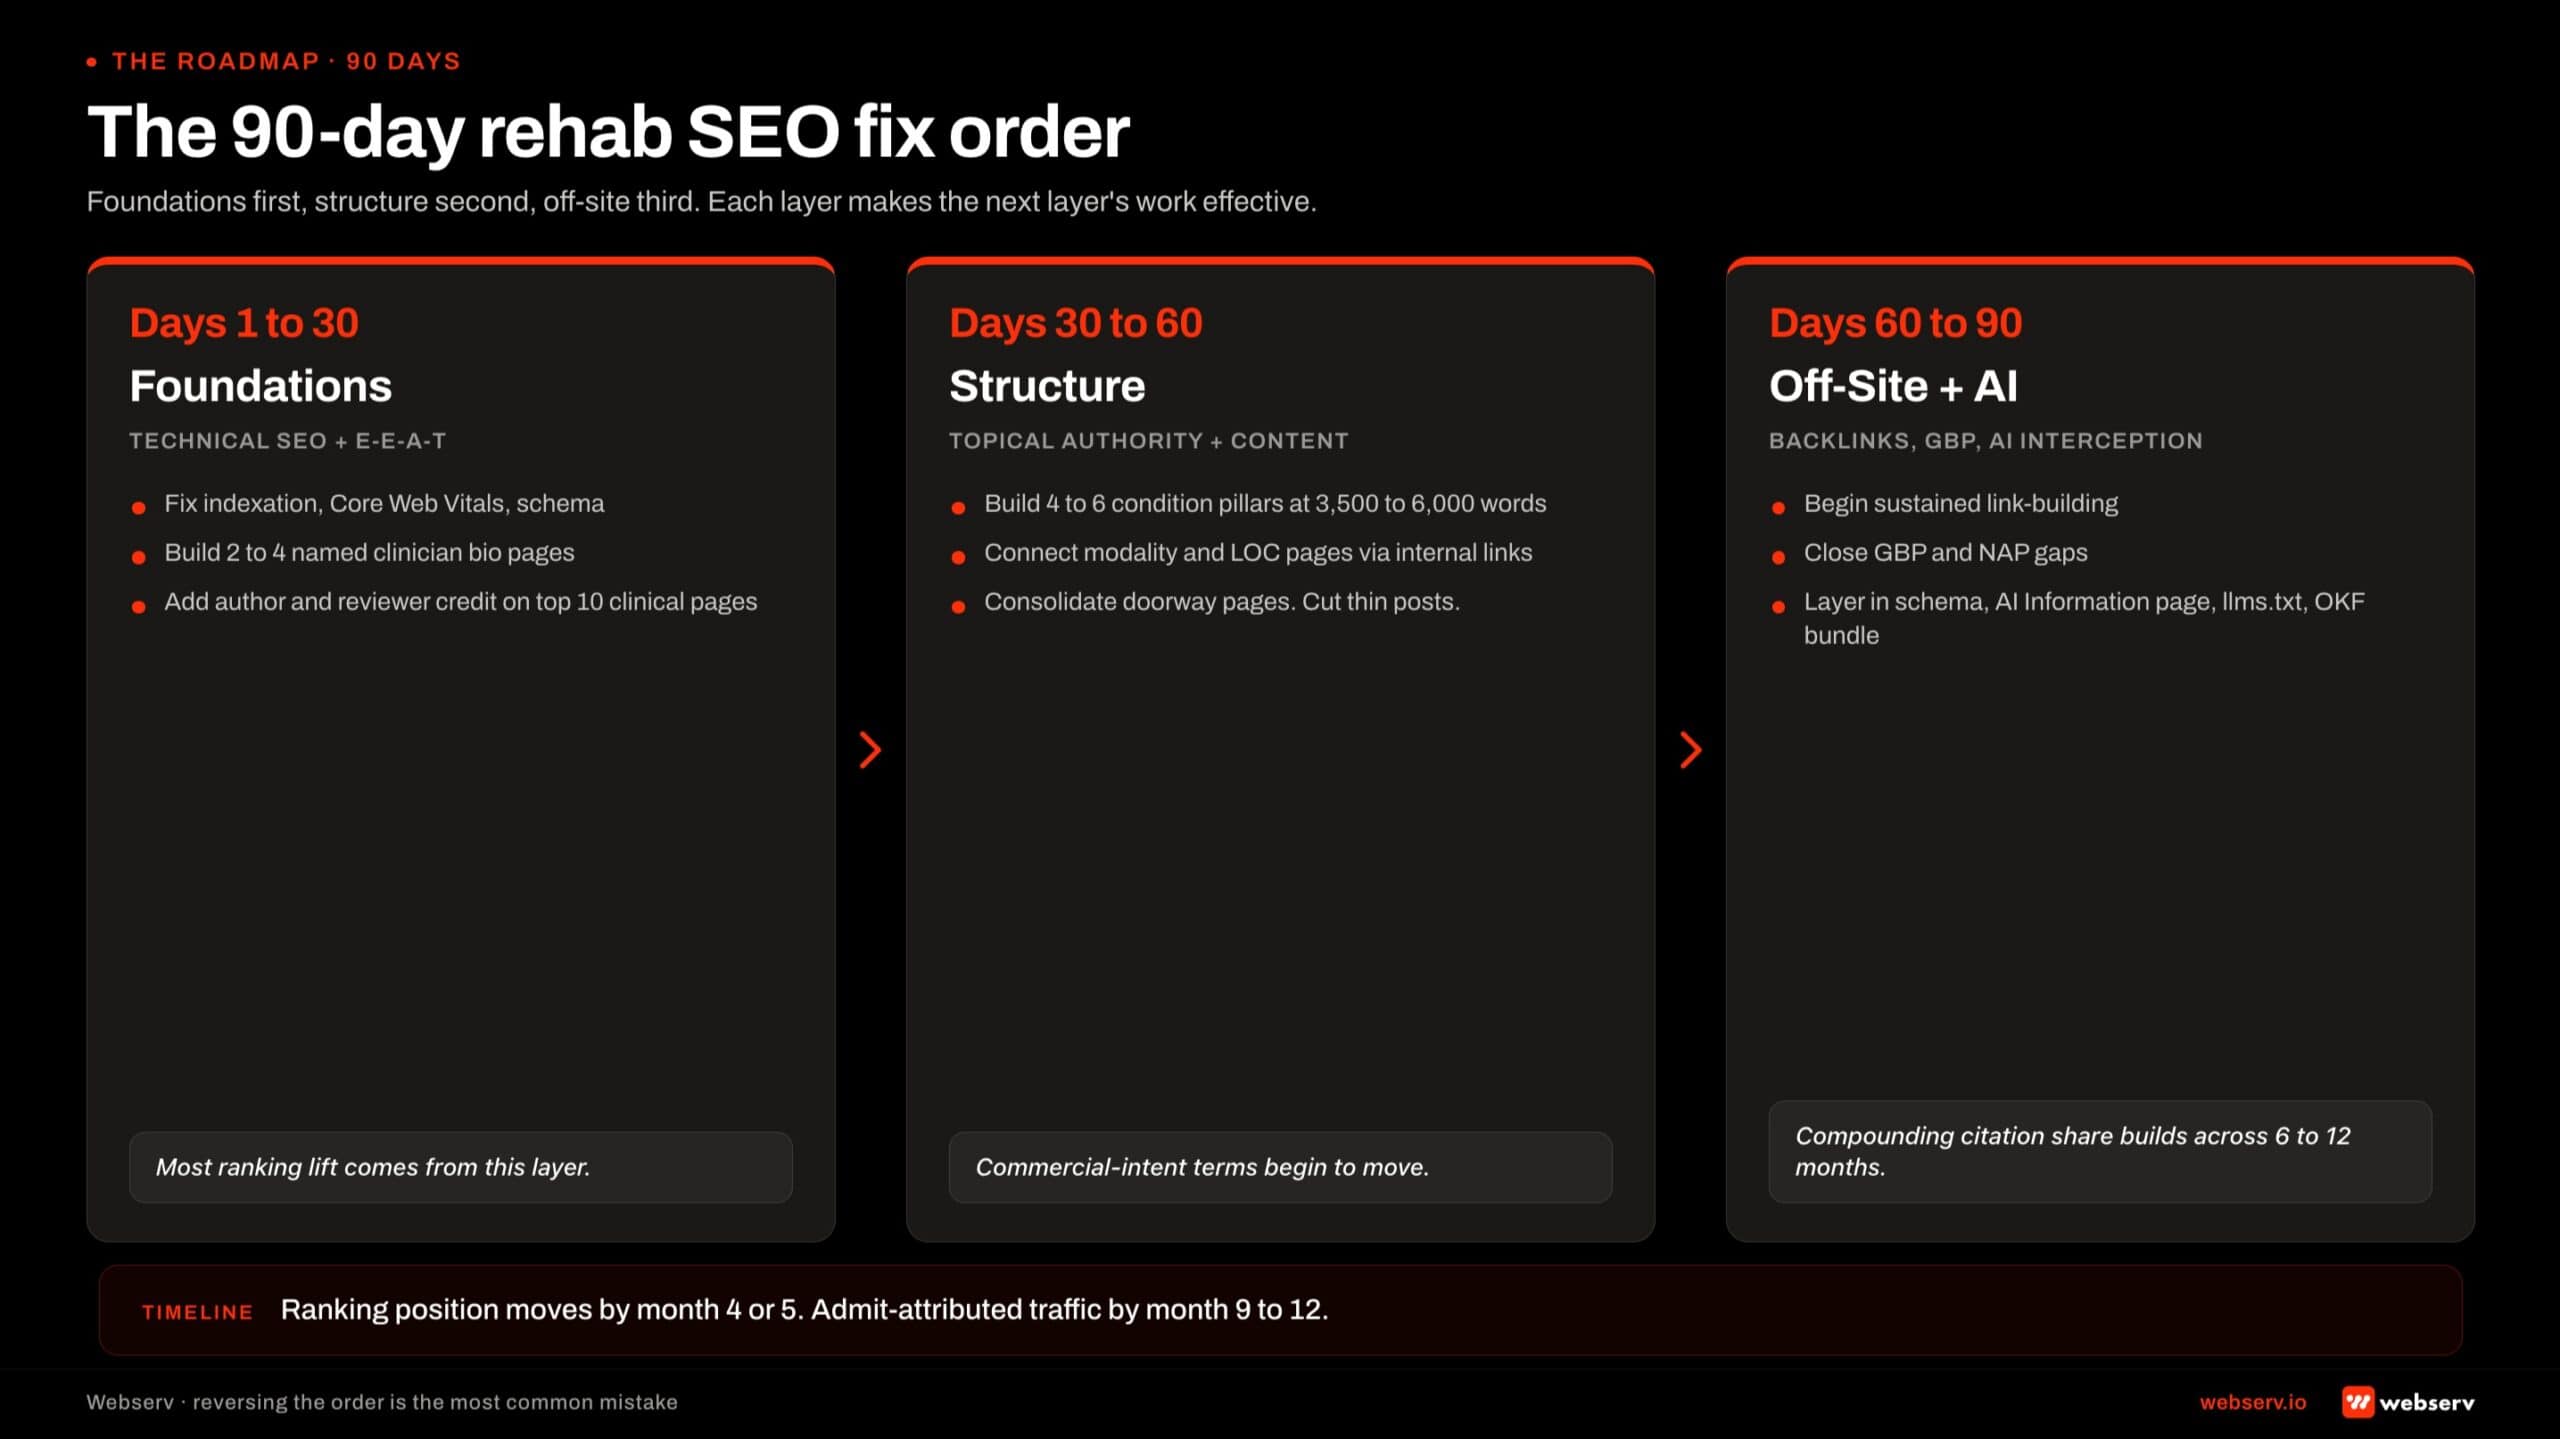 Horizontal three-phase timeline ribbon infographic titled ‘The 90-day rehab SEO fix order.’
Days 1-30: Foundations. Technical SEO and E-E-A-T. Fix the technical issues (indexation, Core Web Vitals, schema) and stand up the named-author and reviewer-credit system on the top 10 to 20 clinical pages. Build out 2 to 4 structured clinician bio pages with credentials, sameAs links, and headshots.
Most ranking lift in the first 90 days comes from this layer. Skipping it to chase content or backlinks is the most common mistake in rehab SEO.
Days 30-60: Structure. Topical authority and content. Build out the missing condition pillar pages (3,500 to 6,000 words each, named clinician author, full citation discipline). Connect the existing modality and level-of-care pages back to the pillars with strong internal linking.
Consolidate any doorway pages flagged in the audit. Cut the thin informational posts that are not earning admit-attributed conversion. Re-target the remaining content for both clinical and patient-vocabulary queries.
Days 60-90: Off-site and AI interception. Backlinks, local SEO, and the AI search interception layer. Begin the sustained link-building program (digital PR, data-driven campaigns, named-clinician thought leadership). Close GBP and NAP gaps.
Layer in the AEO infrastructure: schema deepening, AI Information page, llms.txt, and an OKF bundle. These produce no immediate ranking lift but begin the citation share compounding that pays back over 6 to 12 months.
The 90-day window does not finish the work. It produces the first measurable ranking signal, validates the diagnosis, and sets up the 12-to-18-month compounding that turns SEO into a primary admit channel.
Operators who run the sequence cleanly see ranking position moving by month 4 or 5 and admit-attributed traffic by month 9 to 12.
What changed in 2025 and 2026
The behavioral health SEO landscape shifted sharply across 2025 and into 2026. Five changes matter operationally for any treatment center running an SEO program now.
DEFINITION
Helpful Content Update (HCU)
Google’s algorithmic system, rolled out across 2024 and 2025, that demotes content created primarily for search engines rather than for human readers. For treatment center sites, HCU specifically punishes commodity-keyword listicles, AI-generated explainer content without clinical review, and scaled-content patterns.
The Helpful Content Update for treatment center content. Google’s Helpful Content Update (HCU) implementation across 2024 and 2025 raised the bar for content quality across all YMYL categories.
Treatment center sites that had been ranking on thin or generic content lost positions, and the recovery for affected sites requires substantive content rewrites rather than minor optimizations.
The AI Overviews rollout and citation pattern shifts. Google AI Overviews rolled out widely across 2024 and 2025, and the citation patterns shifted across 2026 as the engine matured.
The early citation patterns favored Reddit and authoritative third-party sources; the 2026 patterns increasingly include treatment center sites that hold strong entity signals and named clinical authorship.
LegitScript as an ongoing obligation. LegitScript certification renews annually with per-facility fees and ongoing monitoring. The implication for organic SEO is that LegitScript-related trust signals need maintenance; operators must maintain certification continuously rather than treating it as a one-time gate.
Google’s increasing reliance on Reddit and community signals. Google’s 2024 Reddit partnership and the broader AI engine reliance on community sources made Reddit the single largest external citation source for treatment center queries by 2026.
The operational implication is that operators who engage authentically with Reddit communities (real clinicians and operators answering real questions in r/addiction, r/recovery, r/AlAnon, and similar) capture citation share that competitors miss.
Federal scrutiny of treatment marketing claims. The FTC enforces the Opioid Addiction Recovery Fraud Prevention Act against deceptive treatment marketing, starting with its case against R360, and unsubstantiated outcome claims (success rates, completion rates, treatment efficacy comparisons) are the obvious exposure.
The FTC Health Products Compliance Guidance provides the framework operators should use to vet their content claims before publication.
The cumulative effect of these five shifts is that the 2024 BH SEO playbook does not work in 2026.
The operators winning their markets are operators who updated their playbook continuously, treated AEO as a primary discipline rather than an experimental sideline, and ran their content production through editorial infrastructure that meets the 2026 bar.
Does healthcare SEO still matter when AI answers the question?
This is the version people actually ask in 2026. Google now resolves many healthcare queries inside AI Overviews and AI Mode before anyone clicks a link. The answer is yes, but the shape of the win changed.
Google Search Central’s own guidance on AI features and your website is blunt: a page has to be indexed and eligible to appear with a snippet, and there are no additional technical requirements. No AI-specific file. No special schema. The same documentation describes a query fan-out technique, where AI Mode issues multiple related searches across subtopics and assembles an answer from the pages it finds.
One healthcare page targeting one keyword is a weak citation candidate. A site that covers a condition or treatment properly, across multiple linked pages with real clinical depth, gets pulled into far more of those sub-searches.
The AI-search-era reframe of healthcare SEO
The eight pillars above did not become obsolete. They became the entry ticket to a second surface. We break the full picture down in the AI search stack guide for treatment centers.
What this means for treatment center operators
The pattern across this guide repeats: BH SEO is structurally different, the seven operational layers compound on each other, the timeline rewards patience over urgency, and the agency selection decision is upstream of everything.
The skip-a-layer pattern is what produces most BH SEO failures. Programs that cover the technical foundation but skip credentialed content production underperform. Programs that produce content but skip the authority and earned media layer underperform. Programs that build authority but skip AEO underperform against operators investing in AI search.
Programs that run all six operational layers but skip the integrated measurement layer cannot defend their budget and get cut before the compounding appears.
The competitive reality in 2026 is that the operators winning their markets started 18 months ago and have continued executing through the timeline. The operators starting now can still catch up, because the discipline is more important than the head start, but the runway compresses every quarter.
Operators waiting another 12 months to commit will find themselves competing against established positions that paid-only strategies cannot dislodge.
The next step for operators evaluating SEO investment is to read the deeper cluster pieces this guide links to: the technical SEO playbook, the keyword strategy framework, the local SEO playbook, the AEO operational guide, and the addiction treatment SEO agency rankings.
Operators whose billing operations are not yet producing predictable cash flow should also read the shortlist of BH-specialized RCM vendors before scaling SEO investment, because marketing spend compounds only when billing operations are reliable.
Operators ready to evaluate Webserv’s SEO program directly can reach out for a strategy session to walk through their specific operator situation and the right tier of investment for their stage.
Most in-house teams hit a wall not because they lack knowledge, but because they lack bandwidth.
When you are ready to hand it off, Webserv has spent 9 years executing exactly this for treatment centers nationwide.
Questions From Hospitals and Clinics
What is healthcare SEO and how is it different from regular SEO?
Healthcare SEO is the practice of ranking a medical or behavioral-health website for the queries patients actually use, under the constraints that apply to health information online. The mechanics look like general SEO. The rules around what a page is allowed to say do not.
Google classifies healthcare pages as Your-Money-or-Your-Life (YMYL) content and evaluates them against a stricter E-E-A-T standard. The public Search Quality Rater Guidelines call out medical topics as a category where named authors, verifiable credentials, and cited clinical sources materially move rankings.
Practical translation: a general-SEO checklist gets a healthcare site partway. The rest is EEAT signal work, medical review, and primary-source citation.
How long does healthcare SEO take to show results?
Six to twelve months for meaningful ranking movement on commercial queries, with first signals (indexing, shifts on lower-competition long-tail queries) usually appearing in the 60-to-90-day window. Google Search Central’s ranking-systems guide makes the point directly: the algorithm rewards accumulated signal, not one-shot changes.
Variance depends on domain age, existing authority, and technical debt at the outset. A behavioral-health facility competing in a saturated state will move slower than a private-practice clinic in a mid-size market.
Anyone promising top-three rankings on high-volume commercial queries inside 30 days is misrepresenting what they can deliver.
Does healthcare SEO still matter now that AI answers most patient questions?
Yes. Google’s own guidance on AI features confirms that AI Overviews and AI Mode pull from indexed pages. There are no additional technical requirements beyond standard indexing and snippet eligibility.
What changed is the shape of the win. AI Mode uses a query fan-out technique, issuing multiple related sub-searches and assembling an answer from the pages it finds. A single page targeting a single keyword is a weak citation candidate. A site that covers a topic properly, across multiple linked pages, gets pulled into far more of that fan-out.
The fundamentals did not become obsolete. They became the entry ticket to a second surface.
How important is Google Business Profile for a medical practice or treatment center?
For any facility with a physical location, GBP is the single highest-impact local channel. Google’s documentation confirms a complete, verified profile is what makes a business eligible for the local pack, Maps, and the knowledge panel on branded searches.
What matters beyond claiming and verifying: accurate NAP (name, address, phone), correct primary and secondary categories, service list matching your site, review response, and regular posts. For behavioral health specifically, the review signal is heavier than in most verticals.
Facilities that run GBP deliberately capture the highest-intent local traffic before an organic result even loads.
Should I hire a healthcare SEO agency or run it in-house?
In-house works when someone on staff can dedicate 10 to 20 hours a week, has a working knowledge of technical SEO, and can coordinate with a medical reviewer for the EEAT layer.
An agency makes sense when you need content production, technical audits, GBP management, link acquisition, and reporting running in parallel, and the internal team is closer to zero SEO hours than 20. Healthcare SEO is a full-time job that also changes constantly.
If you go the agency route, ask for last-three case studies with actual patient inquiry data (not ranking screenshots), verify their reviewers understand medical content standards, and confirm the reporting model ties activity to admissions or bookings. Our Content and SEO services page describes how we scope that work.
Frequently asked questions about SEO for drug rehab centers
How is SEO for drug rehab centers different from general SEO?
Drug rehab SEO sits at the intersection of YMYL ranking standards, HIPAA-restricted tracking, LegitScript certification gates, FTC enforcement on outcome claims, and Google’s Healthcare and Medicines policy. The constraint stack means general SEO playbooks built for ecommerce or local services miss most of what matters in this vertical.u003cbru003eu003cbru003eThe right playbook is built around the constraints rather than despite them. Credentialed clinical authorship is required where general SEO treats authorship as optional. Server-side HIPAA-compliant analytics is required where general SEO uses standard pixel tracking. Outcome claims require FTC-grade substantiation where general SEO operates with marketing-grade claims.u003cbru003eu003cbru003eOperators who treat the constraints as a forcing function win the category, because the operators who write the new playbook lap the operators trying to retrofit the old one. The seven operational layers above describe the working version.
How long does SEO take to work for a treatment center?
Realistic timeline is 3 months for first measurable lift, 9 to 12 months for compounding admit volume, and 12 to 18 months for category-leading positions. The compounding pattern is the most important variable: operators who quit at month 4 to 6 see no admit lift because the compounding has not appeared yet, while operators who commit to 18 months reliably outperform paid-only competitors.u003cbru003eu003cbru003eThe phases are predictable. Month 1 to 3 builds the foundation. Month 4 to 6 sees first content cluster expansion and early ranking movement on long-tail queries. Month 7 to 9 produces measurable AI citation share lift and the first commercial-intent queries reaching page one. Month 10 to 12 produces the first admit attribution data and the compounding effect becomes visible.u003cbru003eu003cbru003eOperators who expect paid-media-speed organic results will be disappointed. The math of quitting at month 6 is the worst possible outcome because it loses the months invested without producing the compounding the investment was designed to capture.
How much should a treatment center budget for SEO?
Four tiers cover the working range. Tier 1 at $3,000 to $5,000 monthly is foundational maintenance for single-location operators with existing rankings. Tier 2 at $7,000 to $12,000 monthly is the floor for compounding programs and the appropriate tier for most single-location operators. Tier 3 at $15,000 to $25,000 monthly is multi-state or multi-facility operator territory with full seven-layer execution. Tier 4 at $30,000+ monthly is national operators with multi-location footprints.u003cbru003eu003cbru003eThe most common budget mistake is committing to a Tier 2 budget but cutting it during the first 6 months when the compounding has not yet appeared. Programs cut at month 4 to 6 produce Tier 1 outcomes because the compounding layers require runway.u003cbru003eu003cbru003eThe right framing is that SEO budget is a strategic investment with an 18-month payback window. Operators thinking about it as a month-to-month marketing line item produce mismatched expectations against the timeline reality, and the mismatched expectations are what cause programs to fail.
Can I do SEO for my rehab in-house, or do I need an agency?
Most operators benefit from agency engagement. The agency model concentrates BH-specific expertise that operators cannot recruit individually, provides technical depth and content production capacity at lower cost than in-house team building, and operationalizes the seven-layer playbook through established workflows.u003cbru003eu003cbru003eIn-house teams work for operators with $1 million-plus annual marketing budgets, dedicated content production capacity, and strong internal clinical leadership. The all-in cost for a competent in-house SEO team runs $400,000 to $800,000 annually, which only makes sense for operators with the budget to support it.u003cbru003eu003cbru003eThe hybrid model splits the work: agency handles technical and production capacity, operator owns brand voice and clinical leadership. This model works well for Tier 3 operators with strong internal teams who want to scale beyond what the internal team can produce alone.
Does LegitScript certification affect organic SEO rankings?
Yes, more than most operators realize. LegitScript was originally designed as a paid advertising gate, but the certification now functions as an organic E-E-A-T signal that Google’s quality raters and AI engines treat as a verifiable third-party endorsement. Sites that hold valid LegitScript certification accumulate trust signals that flow into organic ranking and AI citation eligibility.u003cbru003eu003cbru003eThe implication is that LegitScript maintenance is now part of the organic SEO playbook, not just the paid playbook. The cross-channel effect also tightened across 2025: a LegitScript audit that surfaces operational issues affects both paid eligibility and organic ranking authority.u003cbru003eu003cbru003eThe 2026 best practice is continuous LegitScript maintenance with internal audit cadence aligned to the external re-certification reviews, and explicit documentation of the certification status in schema markup and on-page trust signals. The full operational picture lives in our u003ca href=u0022https://webserv.io/resources/blog/paid-search-compliance-rehab-centers-legitscript/u0022u003eLegitScript compliance guideu003c/au003e.
Should treatment centers invest in AI search optimization (AEO)?
Yes, urgently. AI search engines are now primary discovery surfaces for treatment center queries. Treatment-seeking research that previously routed through traditional Google search now increasingly routes through AI engines that synthesize answers from cited sources. Operators not investing in AEO are losing share on a metric most marketing teams are not measuring.u003cbru003eu003cbru003eAEO is structured around seven operational layers: entity SEO, passage-level optimization, named clinical authorship, Reddit and community citation building, FAQ structuring, source diversification, and citation share measurement. The investments compound in the same pattern as traditional SEO but with a faster lead time (typically 12 to 16 weeks for measurable citation share lift versus 6 to 12 months for measurable organic ranking lift).u003cbru003eu003cbru003eThe bigger picture is that 2026 is the year AEO becomes a primary discovery layer. Operators investing now position for the next phase; operators waiting until the layer is fully mature will be too late to catch the early-mover citation share that compounds into category leadership.
What are the most common SEO mistakes treatment centers make?
The eight recurring patterns include generic content without clinical review, stock photography and stock language, listicles without expert depth, bought links and link schemes, HIPAA-noncompliant tracking, population-specific content treated as interchangeable, site rebuilds that lose rankings, and forgetting AEO entirely. Each pattern is individually fixable but cumulatively expensive when allowed to compound.u003cbru003eu003cbru003eThe mistakes share a common root: the operator (or the agency) is running general SEO with healthcare modifications instead of running BH-specific SEO. The constraint stack and the operational reality of the category require a different playbook.u003cbru003eu003cbru003eThe diagnostic worth running is the annual SEO audit. Operators running annual audits identify the patterns before they compound; operators who run their programs without audit cadence accumulate damage that surfaces only when the program is failing. The audit should cover all seven operational layers, with explicit checks for the eight failure patterns above. If you want a second opinion on your current SEO program, u003ca href=u0022https://webserv.io/intro-meeting/u0022u003ereach out for a strategy sessionu003c/au003e and we can walk through where your site sits in the seven-layer build.
The perspective in this article comes from 9 years working exclusively inside behavioral health.
We are a team built by people in recovery who understand that behind every admission is someone asking for help. If that resonates, get to know us.
Trevor Gage is the Director of Earned & Owned Media at Webserv, a digital marketing agency for treatment centers.